
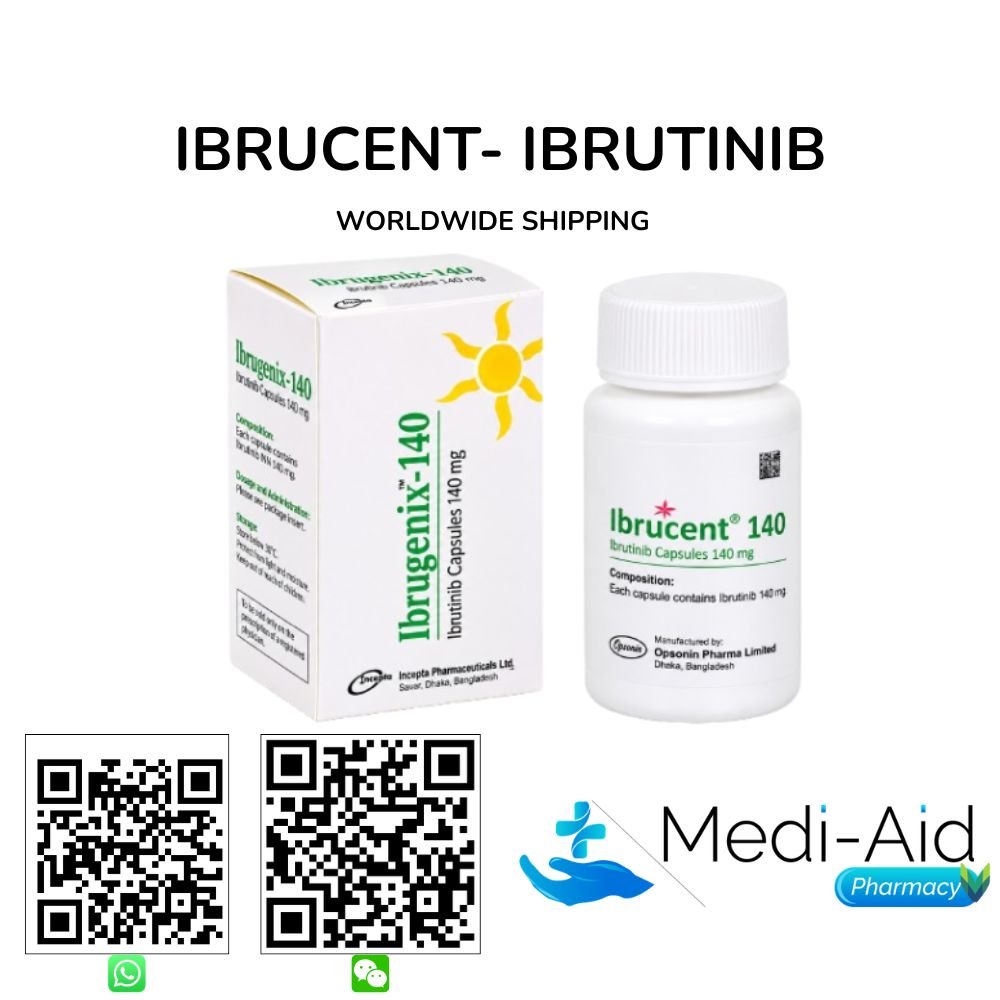
Description
Ibrucent 140 MG (Ibrutinib) is an oral, hard capsule formulation of ibrutinib available in a 140 mg strength, supplied in a pack of 90 capsules per pot, manufactured by Incepta Pharmaceuticals Ltd. of Bangladesh. The active ingredient, ibrutinib, is a first-in-class, orally bioavailable, covalent Bruton’s tyrosine kinase (BTK) inhibitor that irreversibly binds to the cysteine-481 (Cys481) residue in the ATP-binding domain of BTK, thereby permanently blocking BTK-mediated B-cell receptor (BCR) signalling, downstream PI3K/AKT/NF-κB pro-survival pathways, and CXCR4/CXCL12-mediated tumour microenvironment adhesion in B-cell malignancies including chronic lymphocytic leukaemia (CLL), small lymphocytic lymphoma (SLL), mantle cell lymphoma (MCL), Waldenström’s macroglobulinaemia (WM), and marginal zone lymphoma (MZL).
The reference-label dose of ibrutinib is 420 mg once daily (QD) for CLL, SLL, WM, and chronic graft-versus-host disease (cGVHD), achieved by taking 3 × Ibrucent 140 MG capsules together once daily; for MCL and MZL the reference-label dose is 560 mg once daily (QD), achieved by taking 4 × Ibrucent 140 MG capsules once daily, all doses taken with or without food. In the pivotal Phase III RESONATE trial, ibrutinib delivered a significantly superior progression-free survival (PFS) compared to ofatumumab in patients with relapsed or refractory CLL/SLL with a 78% reduction in risk of progression or death (HR 0.22; 95% CI 0.15–0.32; P<0.0001) establishing ibrutinib as a cornerstone of BTK-targeted therapy in B-cell malignancies.
The overall response rate (ORR) in the RESONATE trial was 62.9% with ibrutinib versus 4.4% with ofatumumab in relapsed or refractory CLL/SLL, with the 24-month overall survival (OS) rate reaching 79% with ibrutinib versus 68% with ofatumumab. Searching for Ibrucent 140 MG Ibrutinib? Mediaid Pharmacy stocks this product within its comprehensive oncology medicines portfolio and ships worldwide.
Basic Product Information of Ibrucent 140 MG (Ibrutinib)
| Brand Name | Ibrucent 140 MG (Ibrutinib) |
| Product Name | Ibrucent |
| Generic Name | Ibrutinib |
| Drug Class | Bruton’s Tyrosine Kinase (BTK) Inhibitor; Irreversible Covalent BTK Inhibitor (iCBTKi); Targeted Oncology Agent for B-Cell Malignancies (CLL, SLL, MCL, WM, MZL, cGVHD) |
| Formulation | Hard Capsule |
| Available Strength | 140 mg per capsule |
| Available Pack Size | 90 Capsules per pot (30-day supply at the reference-label CLL/SLL/WM/cGVHD dose of 3 capsules/day [420 mg QD]) |
| Primary Indications | Chronic Lymphocytic Leukaemia (CLL) / Small Lymphocytic Lymphoma (SLL); Mantle Cell Lymphoma (MCL); Waldenström’s Macroglobulinaemia (WM); Marginal Zone Lymphoma (MZL); Chronic Graft-versus-Host Disease (cGVHD) in Adult Patients |
| Reference-Label Starting Dose | CLL/SLL/WM/cGVHD: 420 mg QD = 3 × Ibrucent 140 MG capsules once daily | MCL/MZL: 560 mg QD = 4 × Ibrucent 140 MG capsules once daily | Taken with or without food; swallowed whole with water |
| Manufacturer / Brand | Incepta Pharmaceuticals Ltd., Bangladesh |
| Country of Origin | Bangladesh |
| Categories | Incepta Pharmaceuticals Medicines, Leukemia Medicines, Lymphoma Medicines, Oncology Medicines |
| Storage Conditions | Store below 25°C in a dry place, protected from light and moisture. Keep out of the reach of children. |
| Global Supplier | Mediaid Pharmacy Worldwide Shipping Available |
How Ibrucent 140 MG (Ibrutinib) Works: Irreversible BTK Inhibition and B-Cell Receptor Signalling Blockade in B-Cell Malignancies
Ibrutinib, the active ingredient in Ibrucent 140 MG, is an orally bioavailable, first-in-class, irreversible covalent Bruton’s tyrosine kinase (BTK) inhibitor that selectively and permanently suppresses BTK the master kinase governing B-cell receptor (BCR) signal transduction and the central survival and proliferation driver in a broad spectrum of B-cell malignancies including CLL, SLL, MCL, WM, MZL, and cGVHD. Ibrutinib achieves its antitumour effect by forming a covalent bond with the cysteine-481 (Cys481) residue in the ATP-binding pocket of BTK, irreversibly inactivating BTK kinase activity and completely blocking downstream propagation of the NF-κB, PI3K/AKT, and MAPK/ERK pro-survival and pro-proliferative signalling cascades that sustain malignant B-cell expansion, survival, and lymph node and bone marrow microenvironment adhesion.
An irreversible covalent BTK inhibitor (iCBTKi) refers to a small molecule that forms a permanent covalent bond with BTK at Cys481, inactivating the kinase for the remainder of its cellular lifetime requiring new BTK protein synthesis for pathway re-activation a mechanistic distinction from reversible kinase inhibitors that dissociate from their target over time. Ibrutinib’s IC₅₀ for BTK is approximately 0.5 nM, confirming subnanomolar BTK inhibitory potency that sustains deep and durable target suppression at the 420 mg QD reference dose used for CLL, SLL, WM, and cGVHD. Each Ibrucent 140 MG hard capsule contains ibrutinib equivalent to 140 mg, with the standard CLL/SLL/WM/cGVHD reference-label dose of 420 mg QD delivered by taking 3 capsules once daily, with or without food.
BCR signalling pathway dependence is the central oncogenic vulnerability ibrutinib exploits in B-cell malignancies. In CLL, MCL, WM, and MZL, constitutive or ligand-driven activation of the B-cell receptor complex on malignant B cells initiates a cascade: receptor-associated LYN and SYK kinases phosphorylate and activate BTK, which in turn activates PLCγ2, triggering NF-κB nuclear translocation and transcription of anti-apoptotic genes (BCL-2, BCL-XL, MCL-1) alongside cell-cycle progression genes. Ibrutinib’s irreversible BTK inactivation permanently severs this cascade, triggering B-cell apoptosis, reducing tumour microenvironment retention (via CXCR4/CXCL12 and VLA-4/VCAM-1 disruption), and mobilising malignant B cells from lymph nodes and bone marrow into the peripheral circulation producing the characteristic, clinically benign initial lymphocytosis observed in CLL patients initiating ibrutinib therapy.
MYD88-independent BTK pathway activity in Waldenström’s macroglobulinaemia (WM) represents a secondary oncogenic axis that ibrutinib suppresses: even in CXCR4-mutated WM patients where ibrutinib demonstrates reduced depth of response, BTK inhibition disrupts the MYD88-driven IRAK signalling axis and mast cell-mediated IgM production, explaining ibrutinib’s broad clinical activity across both MYD88-mutated (MYD88 L265P) and wild-type WM genotypes. In the pivotal Phase III RESONATE trial 391 patients with relapsed or refractory CLL/SLL ibrutinib 420 mg QD (achievable as 3 × Ibrucent 140 MG capsules once daily) delivered a PFS hazard ratio of 0.22 (95% CI 0.15–0.32; P<0.0001) and ORR of 62.9% versus 4.4% with ofatumumab. Oncologists managing patients with BTK-dependent B-cell malignancies can review the full range of leukemia medicines at Mediaid Pharmacy, including Ibrucent 140 MG Ibrutinib, for comprehensive CLL and lymphoma treatment programme planning.
In the RESONATE Phase III trial which stratified patients by ECOG performance status and del(17p) mutation status ibrutinib demonstrated consistent PFS benefit across all pre-specified subgroups including patients with del(17p) or TP53 mutation (the highest-risk CLL subgroup for whom chemoimmunotherapy routinely fails), 17p-deleted patients historically resistant to alkylating agents and anti-CD20 therapies. The 24-month OS rate was 79% with ibrutinib versus 68% with ofatumumab (HR 0.43; 95% CI 0.24–0.79; P=0.0049). The ibrutinib dose for each patient must be determined and adjusted by the treating haematologist or oncologist; Ibrucent 140 MG capsules must be prescribed and taken under the supervision of a qualified haematology-oncology specialist.
Approved Indications of Ibrutinib Ibrucent 140 MG Reference Label
Ibrutinib is approved in numerous countries for multiple B-cell malignancy indications covering both treatment-naïve and relapsed or refractory settings. The 140 mg hard capsule formulation of Ibrucent, with its 90-capsule pack size, supports the reference-label 420 mg QD dose (3 capsules/day) for CLL/SLL/WM/cGVHD and the 560 mg QD dose (4 capsules/day) for MCL/MZL. Prescribers must confirm the exact locally approved indication on the ibrutinib product label before initiating therapy, as specific label language varies by regulatory jurisdiction. Diagnostic confirmation of the relevant B-cell malignancy subtype and mutation status (del(17p), TP53, MYD88 for WM) must be established before initiating ibrutinib therapy.
|
CLL and SLL Treatment-Naïve and Relapsed/Refractory Adult Patients Ibrutinib is indicated as monotherapy or in combination with bendamustine plus rituximab (BR), obinutuzumab, or venetoclax for the treatment of adult patients with CLL and SLL, including treatment-naïve patients and those with relapsed or refractory disease. High-risk patients with del(17p) or TP53 mutation historically resistant to chemoimmunotherapy benefit significantly from ibrutinib’s BTK-targeted, chemotherapy-independent mechanism. Reference-label dose: 420 mg once daily (QD) = 3 × Ibrucent 140 MG capsules per day. Oncologists can review the full range of leukaemia targeted therapy medicines at Mediaid Pharmacy alongside Ibrucent for comprehensive CLL programme planning. |
MCL Previously Treated Adult Patients Ibrutinib is indicated for adult patients with mantle cell lymphoma (MCL) who have received at least one prior line of therapy. MCL is an aggressive B-cell non-Hodgkin lymphoma with constitutively active BCR signalling driven by CCND1 overexpression and BTK pathway dependence. In the registrational PCYC-1104 study (n=111 relapsed/refractory MCL patients), ibrutinib 560 mg QD achieved an ORR of 68% (CR 21%, PR 47%) with a median duration of response of 17.5 months. Reference-label dose: 560 mg once daily (QD) = 4 × Ibrucent 140 MG capsules per day. Oncologists managing MCL can review lymphoma medicines at Mediaid Pharmacy for comprehensive programme support. |
|
Waldenström’s Macroglobulinaemia (WM) Treatment-Naïve and Relapsed/Refractory Adult Patients Ibrutinib is indicated for adult patients with Waldenström’s macroglobulinaemia (WM), a rare indolent B-cell lymphoplasmacytic lymphoma characterised by IgM paraprotein production and MYD88 L265P mutation in approximately 90% of cases. In the pivotal iNNOVATE Phase III trial (ibrutinib + rituximab versus placebo + rituximab), the ibrutinib-containing arm achieved a PFS benefit (HR 0.20; P<0.0001) across MYD88-mutated and CXCR4-mutated subgroups. Reference-label dose: 420 mg once daily (QD) = 3 × Ibrucent 140 MG capsules per day. |
MZL and cGVHD Indication-Specific Dosing with Ibrucent 140 MG Ibrutinib is indicated for adult patients with marginal zone lymphoma (MZL) who require systemic therapy after at least one prior anti-CD20-based therapy (reference-label dose: 560 mg QD = 4 × Ibrucent 140 MG capsules/day), and for adult patients with moderate-to-severe chronic graft-versus-host disease (cGVHD) who have failed one or more lines of systemic therapy (reference-label dose: 420 mg QD = 3 × Ibrucent 140 MG capsules/day). The 90-capsule pot of Ibrucent 140 MG delivers a full 30-day CLL/SLL/WM/cGVHD treatment cycle at 3 capsules/day, covering the complete reference-label dose modification pathway. Oncologists can review lymphoma and B-cell malignancy medicines at Mediaid Pharmacy for comprehensive sourcing support. |
Ibrutinib Reference-Label Dosing Guide Ibrucent 140 MG Capsule Counts by Indication and Dose Level
The following dosing table outlines the reference-label doses for ibrutinib across all approved indications and dose modification levels, expressed in both total milligrams and Ibrucent 140 MG capsule counts. All dosing decisions, dose modifications, and dose interruptions must be made exclusively by the treating haematologist or oncologist based on the patient’s individual clinical assessment, tolerability, and locally approved label. This table is provided for informational and procurement reference only.
| Indication | Reference-Label Dose | Ibrucent 140 MG Capsules Per Day | Administration |
| CLL / SLL (all patients, including treatment-naïve and del(17p)) | 420 mg QD | 3 capsules once daily | Orally, with or without food; swallowed whole with water; at approximately the same time each day |
| MCL (previously treated) | 560 mg QD | 4 capsules once daily | Orally, with or without food; swallowed whole with water; at approximately the same time each day |
| Waldenström’s Macroglobulinaemia (WM) | 420 mg QD | 3 capsules once daily | Orally, with or without food; swallowed whole with water; at approximately the same time each day |
| Marginal Zone Lymphoma (MZL) | 560 mg QD | 4 capsules once daily | Orally, with or without food; swallowed whole with water; at approximately the same time each day |
| Chronic Graft-versus-Host Disease (cGVHD) | 420 mg QD | 3 capsules once daily | Orally, with or without food; swallowed whole with water; discontinue if cGVHD no longer requires treatment |
| First dose reduction (all indications) | 280 mg QD | 2 capsules once daily | Dose reduction initiated by treating oncologist for Grade 3 or higher non-haematologic toxicity or Grade 3 neutropenia with infection or fever |
| Second dose reduction (all indications) | 140 mg QD | 1 capsule once daily | If toxicity recurs at 280 mg QD or tolerability requires further reduction; permanent discontinuation required if toxicity recurs at 140 mg QD |
Baseline Assessment and Monitoring Requirements for Ibrucent 140 MG (Ibrutinib) Therapy
Before initiating Ibrucent 140 MG therapy, the treating haematologist or oncologist must complete a comprehensive baseline assessment. Cardiac evaluation is mandatory: a baseline electrocardiogram (ECG) is required to assess for pre-existing arrhythmias or QTc prolongation; atrial fibrillation (AF) is both a pre-existing risk factor and a treatment-emergent adverse event in ibrutinib-treated patients with an incidence of approximately 6–9% across the clinical programme requiring baseline cardiac history and rhythm assessment. Patients with pre-existing AF, risk factors for AF, or prior cardiac conditions require cardiology consultation before initiating ibrutinib.
Bleeding risk assessment is a critical pre-treatment safety evaluation: ibrutinib inhibits BTK-mediated platelet collagen receptor signalling (GPVI pathway), impairing platelet activation and increasing bleeding risk. Baseline platelet count, coagulation parameters (PT/INR, aPTT), and a detailed medication history to identify concurrent anticoagulants (warfarin, direct oral anticoagulants), antiplatelet agents (aspirin, clopidogrel), and NSAIDs are mandatory before initiating ibrutinib. The benefit-risk of anticoagulation therapy concurrent with ibrutinib requires individualised clinical assessment by the treating haematologist-oncologist. Blood pressure monitoring is required: treatment-emergent hypertension occurs in approximately 17% of ibrutinib-treated patients, with Grade 3 or higher hypertension in approximately 8%; baseline blood pressure measurement and regular monitoring during therapy are required, with antihypertensive therapy initiated as clinically indicated.
Hepatic impairment assessment: ibrutinib is extensively metabolised by CYP3A4; hepatic impairment significantly increases ibrutinib systemic exposure. No dose adjustment is required for mild hepatic impairment (Child-Pugh Class A); dose reductions to 280 mg QD (Child-Pugh Class B) and 140 mg QD (Child-Pugh Class C) are recommended based on PK modelling data, with enhanced toxicity monitoring in these patients. Ibrutinib is not recommended in patients with severe hepatic impairment unless the treating oncologist determines that the clinical benefit outweighs the risk. Infection history assessment is required: ibrutinib increases susceptibility to bacterial, fungal, and viral infections, including serious pneumocystis jiroveci pneumonia (PJP), aspergillosis, and hepatitis B reactivation; patients should be assessed for prior HBV exposure (HBsAg, anti-HBc) before initiating ibrutinib, with antiviral prophylaxis as indicated. Oncologists managing comprehensive haematological malignancy programmes can review the full oncology medicines catalogue at Mediaid Pharmacy for supportive agent sourcing alongside Ibrucent 140 MG.
Drug Interactions and Important Safety Information for Ibrucent 140 MG (Ibrutinib)
The most clinically significant pharmacokinetic drug interaction risk for ibrutinib involves CYP3A4 modulators. Ibrutinib is primarily metabolised by CYP3A4 to its principal active metabolite PCI-45227 (dihydrodiol ibrutinib), which retains approximately 15% of BTK inhibitory potency relative to the parent compound. Strong CYP3A4 inducers including rifampicin, carbamazepine, phenytoin, phenobarbital, and St. John’s Wort (Hypericum perforatum) significantly increase ibrutinib metabolism and reduce systemic exposure, potentially compromising antitumour efficacy; in PK studies, rifampicin reduced ibrutinib AUC by approximately 10-fold. Avoidance of strong CYP3A4 inducers is preferred; if unavoidable, the treating oncologist should consider alternative agents or close clinical monitoring for loss of ibrutinib efficacy.
Strong CYP3A4 inhibitors including ketoconazole, itraconazole, voriconazole, posaconazole, clarithromycin, and ritonavir-boosted HIV medications may substantially increase ibrutinib systemic exposure (up to 24-fold with posaconazole) and amplify haemorrhagic, cardiac, and hepatic toxicity risk. Azole antifungals (voriconazole, posaconazole, fluconazole) are routinely used for PJP and aspergillosis prophylaxis in CLL and MCL patients and represent the most clinically common strong CYP3A4 inhibitor interaction in ibrutinib-treated patients. When strong CYP3A4 inhibitors cannot be avoided, reducing ibrutinib to 140 mg QD (1 × Ibrucent 140 MG capsule) with close clinical monitoring is recommended during the period of CYP3A4 inhibitor co-administration; moderate CYP3A4 inhibitors (erythromycin, diltiazem, verapamil, fluconazole) may require ibrutinib dose reduction to 280 mg QD.
Anticoagulants and antiplatelet agents: the combination of ibrutinib with anticoagulants (warfarin, direct oral anticoagulants including apixaban, rivaroxaban, dabigatran) and antiplatelet agents (aspirin, clopidogrel, ticagrelor) substantially amplifies the bleeding risk associated with ibrutinib’s GPVI-mediated platelet dysfunction. Warfarin concurrent with ibrutinib was excluded from key ibrutinib clinical trials and is generally not recommended. When anticoagulation is clinically necessary, the treating haematologist-oncologist must balance thromboembolic risk against ibrutinib-associated haemorrhagic risk on an individualised basis with regular monitoring. P-glycoprotein (P-gp) inhibitors including certain antifungals and HIV antiretrovirals may further increase ibrutinib plasma concentrations and require clinical monitoring and potential dose adjustment.
Cardiac risk agents: ibrutinib’s association with atrial fibrillation and ventricular arrhythmias requires careful evaluation of concurrent medications that increase cardiac risk, including antiarrhythmics (amiodarone, sotalol, digoxin), QTc-prolonging agents (fluoroquinolones, macrolide antibiotics, antipsychotics), and stimulants. Patients initiating ibrutinib with pre-existing cardiac disease or concurrent cardiotoxic agents require cardiology co-management and regular ECG and blood pressure monitoring. All concomitant medications including over-the-counter supplements, antifungals, antiretrovirals, anticoagulants, and herbal preparations must be disclosed to the treating haematologist-oncologist before and during Ibrucent 140 MG therapy. Oncology teams requiring concurrent agents alongside ibrutinib-based leukaemia and lymphoma regimens at Mediaid Pharmacy can contact the team for multi-medicine sourcing support.
Side Effects and Precautions of Ibrucent 140 MG (Ibrutinib)
|
Common Side Effects Diarrhoea (approximately 47%; the most frequently reported gastrointestinal adverse event; typically mild to moderate and manageable with antidiarrhoeal agents, hydration, and dietary modification; Grade 3–4 in approximately 5% of patients) Fatigue and asthenia (approximately 28–41%); often multifactorial, contributed to by disease burden, concurrent cytopenias, infections, and direct drug-related effects; typically Grade 1–2 Musculoskeletal pain including myalgia and arthralgia (approximately 28–37%); a distinctive ibrutinib-associated adverse event; typically managed with analgesics and dose interruption when Grade 3 or higher Nausea (approximately 26–29%); bruising and petechiae (approximately 19–30%) reflecting ibrutinib’s GPVI-mediated platelet dysfunction; peripheral oedema (approximately 17–22%) Rash (approximately 25%); upper respiratory tract infections (approximately 24%); constipation (approximately 15–23%); decreased appetite (approximately 15–20%) Hypertension (approximately 17%); Grade 3–4 hypertension in approximately 8% of patients; requires baseline blood pressure assessment and regular monitoring with antihypertensive therapy as clinically indicated Neutropenia (approximately 19%); anaemia (approximately 17%); thrombocytopenia (approximately 15%); haematological monitoring with complete blood count (CBC) at baseline and throughout therapy is required |
Serious Warnings and Precautions Serious haemorrhage: fatal and life-threatening bleeding events have been reported in ibrutinib-treated patients, including subdural haematoma, gastrointestinal haemorrhage, and haematuria. Ibrutinib impairs GPVI-mediated platelet activation without significantly prolonging the bleeding time in most patients; however, the combination with anticoagulants or antiplatelet agents substantially elevates major bleeding risk. Any new or worsening bleeding symptoms require urgent clinical evaluation and ibrutinib interruption. Atrial fibrillation and cardiac arrhythmias: treatment-emergent atrial fibrillation occurs in approximately 6–9% of ibrutinib-treated patients and ventricular arrhythmias have been reported. Patients developing new cardiac symptoms including palpitations, dyspnoea, pre-syncope, or syncope require urgent ECG assessment and cardiology evaluation. Ibrutinib dose interruption is required for symptomatic AF; the benefit-risk of ibrutinib resumption must be re-evaluated by the treating haematologist-oncologist and cardiologist. Serious infections: ibrutinib-treated patients are at increased risk for serious bacterial, fungal, and viral infections, including PJP, aspergillosis, and hepatitis B reactivation. HBV reactivation, including fatal cases, has been reported; all patients must be screened for HBV serology (HBsAg, anti-HBc) before initiating ibrutinib. Prophylactic antiviral therapy and PJP prophylaxis should be considered as clinically appropriate. Tumour lysis syndrome (TLS): patients with high CLL tumour burden or rapidly progressive MCL are at risk for TLS at ibrutinib initiation; appropriate hydration, uric acid monitoring, and prophylactic allopurinol or rasburicase are required as clinically indicated in high-risk patients. Second primary malignancies: non-melanoma skin cancers and other second primary malignancies have been reported in ibrutinib-treated patients; regular dermatological assessment is recommended during long-term ibrutinib therapy. Embryo-fetal toxicity: ibrutinib can cause fetal harm based on its mechanism of action and animal reproductive toxicology data. Females of reproductive potential must use effective contraception during treatment and for 1 month after the final dose. Males with female partners of reproductive potential must also use effective contraception during treatment and for 1 month after the last dose. Breastfeeding is not recommended during ibrutinib treatment. |
Who Should Use Ibrucent 140 MG (Ibrutinib)?
Ibrucent 140 MG (Ibrutinib) is indicated for adult patients with the following B-cell malignancies: chronic lymphocytic leukaemia (CLL) or small lymphocytic lymphoma (SLL) including treatment-naïve patients and those with high-risk genomic features (del(17p), TP53 mutation) for whom chemoimmunotherapy yields inadequate outcomes; relapsed or refractory mantle cell lymphoma (MCL) after at least one prior line of therapy; Waldenström’s macroglobulinaemia (WM) in treatment-naïve and relapsed/refractory settings; marginal zone lymphoma (MZL) requiring systemic therapy after prior anti-CD20-based treatment; and moderate-to-severe chronic graft-versus-host disease (cGVHD) failing one or more prior systemic therapies. The 140 mg hard capsule formulation with a 90-capsule pot is clinically appropriate for any adult patient requiring the reference-label 420 mg QD dose (CLL/SLL/WM/cGVHD), the 560 mg QD dose (MCL/MZL), or any stepwise dose reduction across the reference-label modification pathway the dosing table above specifies the precise Ibrucent 140 MG capsule counts for each dose level.
Haematologists and oncologists must assess baseline cardiac function (ECG, blood pressure, arrhythmia history), haematological parameters (CBC with differential), hepatic function (ALT, AST, bilirubin), renal function, coagulation status, HBV serology, and all concomitant medications particularly anticoagulants, antiplatelet agents, azole antifungals, antiretrovirals, and CYP3A4 modulators before prescribing any ibrutinib dose. Patients who are pregnant, planning a pregnancy, or of reproductive potential without adequate contraception require mandatory pre-therapy counselling. Oncologists seeking comprehensive targeted agent support across leukaemia and lymphoma treatment programmes can review the full range of leukaemia medicines at Mediaid Pharmacy, including Ibrucent 140 MG Ibrutinib for BTK-dependent B-cell malignancies after prior therapy or as first-line treatment.
Global Supplier: Mediaid Pharmacy Worldwide Shipping for Ibrucent 140 MG (Ibrutinib)
Mediaid Pharmacy is a Dhaka-based supplier of oncology and specialty medicines with worldwide shipping capacity. Ibrucent 140 MG (Ibrutinib) manufactured by Incepta Pharmaceuticals Ltd. of Bangladesh, formulated as hard capsules in 90-capsule pots, is stocked and available for international supply. All orders are supported by pricing quotations, stock confirmation, and end-to-end delivery tracking. Hospitals, specialist haematology and oncology clinics, cancer centres, CLL and lymphoma treatment programmes, distributors, and patients in countries where ibrutinib is approved can contact the Mediaid Pharmacy team through WhatsApp, phone, or WeChat for all enquiries about oral ibrutinib capsules for CLL, MCL, WM, MZL, and cGVHD including current stock availability, pricing, and international delivery timelines. Institutions and distributors sourcing multiple oncology medicines in a single consolidated shipment can request a combined quotation from the Mediaid Pharmacy team after browsing the full catalogue.
Why Choose Ibrucent 140 MG (Ibrutinib) from Mediaid Pharmacy?
Ibrucent 140 MG is manufactured by Incepta Pharmaceuticals Ltd. of Bangladesh and delivers ibrutinib the first-in-class irreversible BTK inhibitor whose clinical trial programme includes the RESONATE Phase III trial (78% reduction in PFS risk; ORR 62.9% vs 4.4%; HR 0.22; P<0.0001; 24-month OS 79% vs 68% vs ofatumumab in relapsed or refractory CLL/SLL), the HELIOS Phase III trial (ibrutinib + BR: PFS HR 0.20; P<0.0001 versus placebo + BR in relapsed/refractory CLL), and the iNNOVATE Phase III trial (ibrutinib + rituximab: PFS HR 0.20; P<0.0001 in WM). The defining procurement advantage of sourcing Ibrucent 140 MG from Mediaid Pharmacy is complete reference-label dosing coverage from a single generic ibrutinib supplier: the 140 mg capsule enables the full 420 mg QD CLL/SLL/WM/cGVHD starting dose (3 capsules once daily), the 560 mg QD MCL/MZL starting dose (4 capsules once daily), the first dose reduction to 280 mg QD (2 capsules once daily), and the second dose reduction to 140 mg QD (1 capsule once daily) covering the complete reference-label dose modification pathway without the need for supplementary capsule strengths.
Mediaid Pharmacy supplies Ibrucent 140 MG in its 90-capsule pot format with worldwide shipping, specialist supply support, and documentation for customs clearance as required. Every order is initiated with a prescription-based enquiry to maintain supply aligned with the treating oncologist’s clinical plan. For oncology programmes requiring a broader panel of targeted and supportive agents for B-cell malignancy treatment including anti-CD20 monoclonal antibodies, venetoclax, anti-CD38 agents, and growth factors the full Mediaid Pharmacy oncology medicines catalogue is available to browse, and the team can be contacted directly for consolidated multi-medicine quotations.
Frequently Asked Questions About Ibrucent 140 MG (Ibrutinib)
What is Ibrucent 140 MG and what is its generic name?
Ibrucent 140 MG is a branded generic ibrutinib hard capsule manufactured by Incepta Pharmaceuticals Ltd. of Bangladesh. The generic name of Ibrucent 140 MG is ibrutinib the same active ingredient as the originator medicine Imbruvica (ibrutinib), originally developed by Pharmacyclics and Janssen (Johnson & Johnson) and first approved by the FDA in November 2013 for MCL, with subsequent approvals for CLL/SLL, WM, MZL, and cGVHD. Each Ibrucent 140 MG hard capsule contains ibrutinib equivalent to 140 mg. The 90-capsule pot of Ibrucent 140 MG provides a complete 30-day supply at the reference-label CLL/SLL/WM/cGVHD starting dose of 420 mg QD (3 capsules per day), making Ibrucent 140 MG a clinically aligned, cost-accessible generic ibrutinib option for haematology-oncology programmes treating B-cell malignancy patients worldwide. Oncology teams can source Ibrucent 140 MG Ibrutinib and other lymphoma medicines at Mediaid Pharmacy with worldwide shipping.
How should Ibrucent 140 MG (Ibrutinib) capsules be taken?
Ibrucent 140 MG (Ibrutinib) capsules are taken orally at the dose and schedule prescribed by the treating haematologist or oncologist. The reference-label starting doses are: 420 mg QD (3 × Ibrucent 140 MG capsules taken together once daily) for CLL, SLL, WM, and cGVHD; and 560 mg QD (4 × Ibrucent 140 MG capsules taken together once daily) for MCL and MZL. Unlike many oral targeted agents with strict food-effect requirements, ibrutinib can be taken with or without food; however, patients must avoid consuming grapefruit, grapefruit juice, Seville oranges, or Seville orange products during ibrutinib therapy, as these contain natural CYP3A4 inhibitors (furanocoumarins) that can substantially increase ibrutinib systemic exposure. Capsules should be swallowed whole with a glass of water and must not be opened, broken, or chewed, as altering the capsule would change the ibrutinib release and absorption profile. If a dose is missed and it is still on the same day, the missed dose should be taken as soon as remembered on that day. If the missed dose is not remembered until the next day, that missed dose should be skipped and the regular dosing schedule resumed patients must not take two doses on the same day to compensate for a missed dose. Ibrutinib must be interrupted at least 3–7 days before and after any surgical procedure to minimise perioperative bleeding risk. Any concerns about administration should be reported to the treating oncologist immediately.
What are the most common side effects of Ibrucent 140 MG (Ibrutinib)?
The most common side effects of ibrutinib across the clinical programme include diarrhoea (approximately 47%), fatigue and asthenia (approximately 28–41%), musculoskeletal pain including myalgia and arthralgia (approximately 28–37%), nausea (approximately 26–29%), bruising and petechiae (approximately 19–30%), peripheral oedema (approximately 17–22%), rash (approximately 25%), upper respiratory tract infections (approximately 24%), hypertension (approximately 17%), neutropenia (approximately 19%), anaemia (approximately 17%), thrombocytopenia (approximately 15%), constipation (approximately 15–23%), and decreased appetite (approximately 15–20%). Atrial fibrillation a potentially life-threatening cardiac arrhythmia occurs in approximately 6–9% of ibrutinib-treated patients and is a distinctive and clinically critical safety concern requiring regular cardiac monitoring, particularly in patients with pre-existing cardiac risk factors. Serious bleeding events, serious infections (including PJP and aspergillosis), and second primary malignancies including non-melanoma skin cancers are important but less common adverse events requiring clinical surveillance. The reference-label dose modification algorithm permits stepwise reductions from 420 mg QD to 280 mg QD (2 capsules) and then to 140 mg QD (1 capsule) using Ibrucent 140 MG capsules. Consult your prescribing haematologist-oncologist regarding your individual risk profile before and during treatment.
What is the evidence base for ibrutinib in CLL and other B-cell malignancies?
The clinical evidence base for ibrutinib spans multiple Phase III trials across B-cell malignancy indications. In relapsed or refractory CLL/SLL, the pivotal RESONATE Phase III trial (NCT01578707; n=391; ibrutinib 420 mg QD versus ofatumumab) demonstrated a PFS hazard ratio of 0.22 (95% CI 0.15–0.32; P<0.0001), ORR of 62.9% versus 4.4%, and 24-month OS rate of 79% versus 68% (HR 0.43; P=0.0049). In treatment-naïve CLL, the RESONATE-2 Phase III trial (ibrutinib versus chlorambucil; n=269) demonstrated PFS HR 0.16 (95% CI 0.09–0.28; P<0.001) with ORR 86% versus 35%. The HELIOS Phase III trial (ibrutinib + bendamustine-rituximab versus placebo + BR in relapsed/refractory CLL; n=578) demonstrated PFS HR 0.20 (95% CI 0.14–0.28; P<0.001). In WM, the iNNOVATE Phase III trial (ibrutinib + rituximab versus placebo + rituximab; n=150) demonstrated PFS HR 0.20 (95% CI 0.11–0.38; P<0.001). In previously treated MCL, the PCYC-1104 registrational study (n=111) demonstrated ORR of 68% (CR 21%) with ibrutinib 560 mg QD. Ibrucent 140 MG delivers ibrutinib at all reference-label doses from 140 mg to 560 mg QD using 1–4 capsules once daily from a 90-capsule pot.
Is Ibrucent 140 MG (Ibrutinib) safe during pregnancy or while breastfeeding?
No. Ibrutinib including in the Ibrucent 140 MG hard capsule formulation can cause fetal harm based on its mechanism of action (BTK inhibition disrupts signalling pathways essential for normal B-cell lymphopoiesis and fetal development) and confirmed animal reproductive toxicology data, which demonstrated embryotoxicity and fetotoxicity at exposures within the human therapeutic range. Females of reproductive potential must use effective contraception during treatment with Ibrucent 140 MG and for at least 1 month after the final dose. Males with female partners of reproductive potential must also use effective contraception during treatment and for at least 1 month after the last dose. Breastfeeding is not recommended during ibrutinib treatment, as it has not been established whether ibrutinib or its metabolites are excreted in human breast milk. Patients who are pregnant, planning a pregnancy, or breastfeeding must discuss their individual circumstances with their treating haematologist-oncologist before initiating ibrutinib therapy.
What makes ibrutinib different from second-generation BTK inhibitors like acalabrutinib or zanubrutinib?
Ibrutinib is the first-in-class, pioneer irreversible covalent BTK inhibitor (iCBTKi) with the broadest approved indication portfolio in B-cell malignancies, covering CLL/SLL, MCL, WM, MZL, and cGVHD with long-term OS data from multiple Phase III trials establishing its clinical legacy. Second-generation BTK inhibitors including acalabrutinib (Calquence) and zanubrutinib (Brukinsa) were designed to offer improved BTK selectivity and reduced off-target kinase activity (ITK, TEC, EGFR, HER2/4) relative to ibrutinib, with the aim of reducing ibrutinib’s distinctive toxicity profile particularly atrial fibrillation, bleeding, and musculoskeletal pain. The ELEVATE-RR Phase III trial (acalabrutinib versus ibrutinib in high-risk relapsed/refractory CLL; n=533) demonstrated non-inferior PFS for acalabrutinib with significantly lower AF incidence (9.4% versus 16.0%) and significantly lower Grade 3–5 hypertension (9% versus 23%). However, ibrutinib retains a substantial global evidence base, the longest long-term follow-up data, the broadest label, and significant procurement cost advantages over second-generation agents in many markets making ibrutinib-based therapy with Ibrucent 140 MG a clinically and economically important option for B-cell malignancy treatment programmes globally.
Can I order Ibrucent 140 MG (Ibrutinib) online with worldwide shipping?
Yes. Mediaid Pharmacy supplies Ibrucent 140 MG (Ibrutinib) manufactured by Incepta Pharmaceuticals Ltd. of Bangladesh hard capsules, 90 capsules per pot to oncology centres, hospitals, distributors, and patients globally. Contact Mediaid Pharmacy via WhatsApp, phone, or WeChat at +8801773428128, or email info@mediaidpharmacy.com, for pricing on Ibrucent 140 MG Ibrutinib, current stock availability, and international delivery details for your country. Oncology teams sourcing Ibrucent 140 MG Ibrutinib alongside other targeted agents can browse the complete range of oncology medicines at Mediaid Pharmacy and request a consolidated multi-medicine quotation. All orders are supported by prescription verification, pricing documentation, and customs clearance support as required for international shipments.
Order Ibrucent 140 MG (Ibrutinib) with Worldwide Shipping
Phone / WhatsApp / WeChat: +8801773428128 | Email: info@mediaidpharmacy.com


Reviews
There are no reviews yet.