
Description
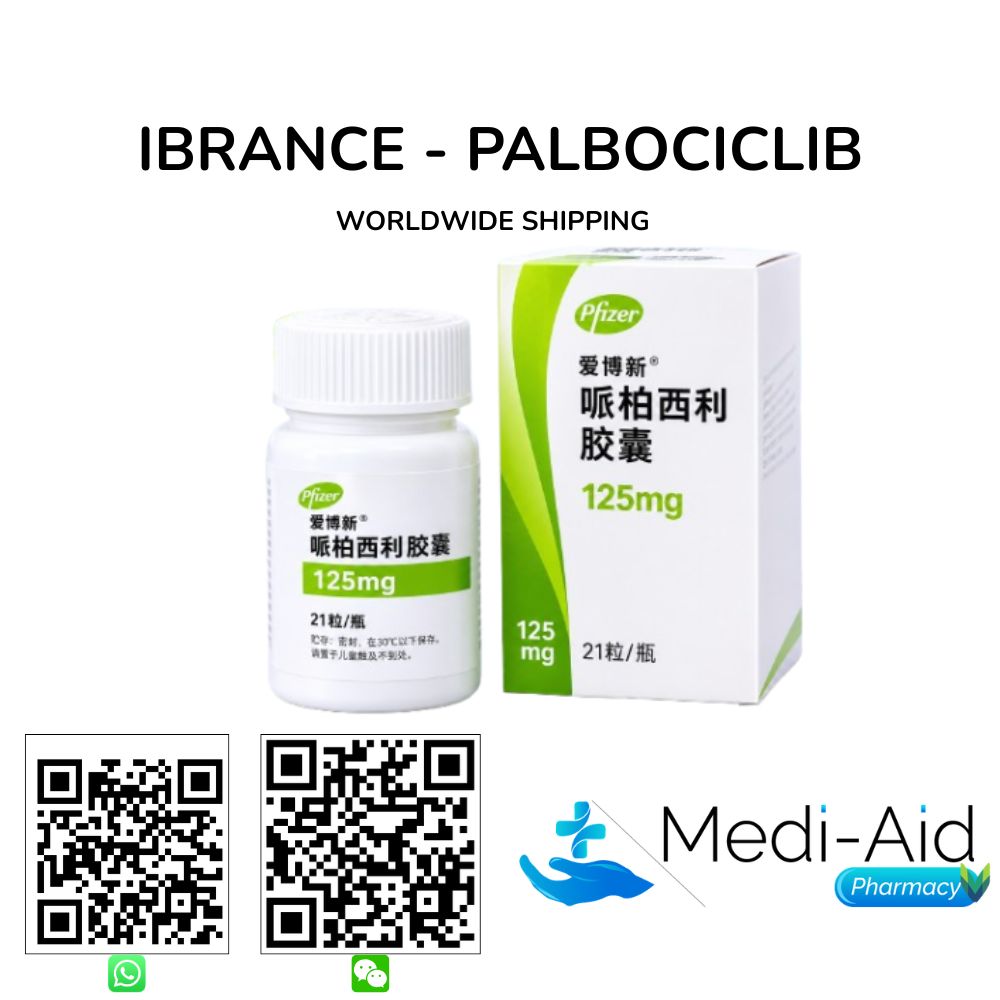
Ibrance 125 MG (Palbociclib) is an orally administered first-in-class selective cyclin-dependent kinase 4 and 6 (CDK4/6) inhibitor and targeted oncology agent a small-molecule inhibitor that arrests tumour cell cycle progression at the G1-to-S phase transition by blocking CDK4/6-mediated phosphorylation of the retinoblastoma protein (Rb), thereby suppressing the proliferative drive in hormone receptor-positive (HR+) malignancies dependent on cyclin D1–CDK4/6–Rb signalling, and restoring G1 cell cycle checkpoint control in HR-positive, HER2-negative advanced and metastatic breast cancer cells supplied as hard capsules in 125 mg strength in a 21-capsule blister pack and manufactured by Pfizer Inc. in China market packaging (Chinese brand name: 爱博新).
Its active pharmaceutical ingredient, palbociclib INN, is indicated in combination with an aromatase inhibitor or fulvestrant for HR+/HER2- advanced or metastatic breast cancer in pre/perimenopausal and postmenopausal women and in men. Ibrance 125 MG capsules are administered at the standard palbociclib dose of 125 mg once daily for 21 consecutive days followed by 7 days off (3 weeks on / 1 week off), with each 21-capsule pack supplying one complete 28-day treatment cycle. The FDA approval of palbociclib in combination with letrozole for postmenopausal women with ER+/HER2- advanced breast cancer (February 2015, accelerated; regular approval March 2016) was supported by the Phase 2 PALOMA-1 trial and confirmed by the Phase 3 PALOMA-2 trial (n=666), in which palbociclib plus letrozole achieved a median progression-free survival (PFS) of 24.8 months versus 14.5 months with letrozole alone (HR 0.58; p<0.001).
In the second-line setting, the Phase 3 PALOMA-3 trial (palbociclib plus fulvestrant versus fulvestrant alone; n=521) demonstrated a median PFS of 9.5 months versus 4.6 months (HR 0.46; p<0.0001) in pre/perimenopausal and postmenopausal women with HR+/HER2- advanced breast cancer that had progressed on prior endocrine therapy. Important: Palbociclib carries a risk of severe neutropenia Grade 3 or 4 neutropenia occurred in approximately 66% of patients receiving palbociclib plus letrozole in PALOMA-2 requiring complete blood count (CBC) monitoring before starting Ibrance, at the beginning of each cycle, on Day 15 of the first two cycles, and as clinically indicated; dose interruption, reduction, or discontinuation may be required.
Interstitial lung disease (ILD) and pneumonitis, including fatal cases, have been reported with palbociclib therapy. Searching for Ibrance 125 MG Palbociclib? Mediaid Pharmacy lists this product across its oncology medicines, breast cancer medicines, and Pfizer medicines portfolios and ships it worldwide.
Basic Product Information of Ibrance 125 MG (Palbociclib)
| Brand Name | Ibrance 125 MG (Palbociclib) |
| Product Name | Ibrance |
| Chinese Package Name | 爱博新 (Àibóxīn) |
| Generic Name | Palbociclib INN |
| Drug Class | Targeted Oncology Agent; First-in-Class Selective Cyclin-Dependent Kinase 4 and 6 (CDK4/6) Inhibitor; Retinoblastoma Protein (Rb) Phosphorylation Inhibitor; Cell Cycle Arrest Agent (G1 Phase); Small-Molecule Kinase Inhibitor; Antineoplastic Agent |
| Formulation | Hard Capsule (Oral) |
| Available Strengths | 125 mg per hard capsule (also available as 75 mg and 100 mg; 125 mg is the recommended starting dose) |
| Available Pack Size | 21 capsules per blister pack (1 complete 28-day treatment cycle at the standard 125 mg dose on a 21-day on / 7-day off schedule) |
| Dosing Schedule | All HR+/HER2- Advanced or Metastatic Breast Cancer Indications (first-line combination with aromatase inhibitor; second-line combination with fulvestrant): Palbociclib 125 mg orally once daily for 21 consecutive days followed by 7 days off (3 weeks on / 1 week off; 28-day cycle). Administer with food at the same time each day. Swallow capsules whole do not crush, chew, or open. Avoid concurrent use with strong CYP3A4 inhibitors or inducers. Continue Ibrance until disease progression or unacceptable toxicity. Consult the treating oncologist for dose modification guidance in the event of neutropenia, adverse reactions, or drug interactions. |
| Primary Indications | (1) HR+/HER2- Advanced or Metastatic Breast Cancer First-Line (Combination with Aromatase Inhibitor): Palbociclib in combination with an aromatase inhibitor (letrozole or anastrozole) as initial endocrine-based therapy in postmenopausal women and in men with hormone receptor-positive, human epidermal growth factor receptor 2-negative (HR+/HER2-) advanced or metastatic breast cancer.
(2) HR+/HER2- Advanced or Metastatic Breast Cancer Second-Line or Later (Combination with Fulvestrant): Palbociclib in combination with fulvestrant for the treatment of pre/perimenopausal or postmenopausal women and men with HR+/HER2- advanced or metastatic breast cancer whose disease has progressed following prior endocrine therapy. Pre/perimenopausal women must also receive a gonadotropin-releasing hormone (GnRH) agonist. |
| Market Packaging | China (Chinese package name: 爱博新) |
| Manufacturer / Brand | Pfizer Inc. (originator and sole manufacturer of Ibrance / palbociclib; first FDA approval February 3, 2015 [accelerated]; confirmed regular FDA approval March 31, 2016 for the letrozole combination; subsequent approvals for the fulvestrant combination in February 2016 and expanded to include men and pre/perimenopausal women in April 2019) |
| Global Supplier | Mediaid Pharmacy, Worldwide Shipping Available |
| Storage Conditions | Store at room temperature 20°C to 25°C (68°F to 77°F); excursions permitted between 15°C and 30°C (59°F to 86°F). Store in the original container. Keep out of the reach of children. |
How Ibrance (Palbociclib) Works: CDK4/6 Inhibition, Rb Dephosphorylation, and G1 Cell Cycle Arrest in HR+/HER2- Breast Cancer
Palbociclib INN is an orally administered targeted oncology agent whose mechanism of action is mechanistically distinct from cytotoxic chemotherapy, HER2-targeted biologics, VEGF pathway inhibitors, PI3K/mTOR inhibitors, and all other antineoplastic drug classes currently in clinical use: palbociclib is a selective, first-in-class, small-molecule inhibitor of cyclin-dependent kinase 4 (CDK4) and cyclin-dependent kinase 6 (CDK6) two serine/threonine protein kinases that are critically activated by cyclin D1 during the G1 phase of the mammalian cell cycle and are pathologically overactivated in hormone receptor-positive (HR+) breast cancers driven by oestrogen receptor (ER) signalling.
CDK4 and CDK6, when activated by binding to their regulatory partner cyclin D1, phosphorylate the retinoblastoma tumour suppressor protein (Rb) at multiple serine and threonine residues. Sequential phosphorylation of Rb inactivates its transcriptional repressor function, releasing the E2F family of transcription factors to drive expression of genes required for S-phase entry and DNA replication, committing the cell to mitosis. In ER+ breast cancer cells, oestrogen receptor signalling promotes cyclin D1 transcription, generating supraphysiological cyclin D1–CDK4/6 activity that chronically hyperphosphorylates Rb, abrogates G1 checkpoint control, and drives unconstrained proliferative cycling a core oncogenic mechanism in the HR+/HER2- breast cancer subtype that accounts for approximately 70% of all breast cancer diagnoses globally.
Palbociclib inhibits CDK4 and CDK6 by competitively binding within the ATP-binding pocket of each kinase, blocking ATP binding and preventing the phosphorylation of Rb. By maintaining Rb in its hypophosphorylated active state, palbociclib restores E2F transcriptional repression, arrests cell cycle progression at the G1-to-S phase checkpoint, and halts DNA replication in tumour cells dependent on CDK4/6–Rb signalling for proliferative drive. This G1 cell cycle arrest is cytostatic not directly cytotoxic and is mechanistically complementary to endocrine therapy (aromatase inhibitors such as letrozole and anastrozole, or the oestrogen receptor degrader fulvestrant), which reduces the upstream oestrogen-driven cyclin D1 signal that activates CDK4/6.
The combination of palbociclib with endocrine therapy thus delivers dual convergent suppression of the cyclin D1–CDK4/6–Rb axis: endocrine therapy reduces cyclin D1 transcription, while palbociclib blocks the residual CDK4/6 kinase activity. This synergistic mechanism is the pharmacological rationale for the combination regimens evaluated in the PALOMA-1, PALOMA-2, and PALOMA-3 clinical trials that formed the basis of palbociclib’s FDA approvals.
Palbociclib’s selectivity for CDK4 (inhibitory constant Ki ~0.011 nM) and CDK6 (Ki ~0.016 nM) is high relative to other CDK family members; palbociclib does not substantially inhibit CDK1 or CDK2 at therapeutic concentrations, which is pharmacologically significant because CDK1 and CDK2 mediate cell cycle checkpoints in normal haematopoietic progenitor cells. The absence of CDK1/2 inhibition in haematopoietic progenitors does not prevent bone marrow toxicity from CDK4/6 inhibition, however: the G1 cell cycle arrest induced by palbociclib in rapidly cycling haematopoietic progenitors is reversible and underlies the clinically predominant dose-limiting toxicity of Ibrance therapy neutropenia.
Neutrophil counts decline within the first cycle of palbociclib treatment, reflecting CDK4/6-mediated arrest of myeloid precursor proliferation; neutropenia is typically reversible during the 7-day off-treatment period in each 28-day cycle and is the primary basis for the 21-day-on / 7-day-off dosing schedule that distinguishes palbociclib from continuous-dosing CDK4/6 inhibitors (ribociclib, abemaciclib). The 7-day recovery period allows haematopoietic progenitor proliferation to resume, restoring neutrophil counts before the next cycle begins.
Clinical Safety Profile of Ibrance 125 MG (Palbociclib)
| Serious Warnings and Precautions | Severe Neutropenia: Neutropenia is the most frequent dose-limiting adverse reaction of palbociclib. Grade 3 or 4 neutropenia occurred in 66% of patients in PALOMA-2 (palbociclib plus letrozole). Monitor CBC before starting Ibrance, at the beginning of each cycle, on Day 15 of the first 2 cycles, and as clinically indicated. Dose interruption, reduction, or discontinuation may be required.
Interstitial Lung Disease (ILD) / Pneumonitis: Severe, life-threatening, or fatal ILD and pneumonitis have been reported. Monitor for pulmonary symptoms. Permanently discontinue Ibrance for severe ILD or pneumonitis. Embryo-Foetal Toxicity: Palbociclib can cause foetal harm when administered to a pregnant woman. Advise females of reproductive potential to use effective contraception during treatment and for at least 3 weeks after the last dose. |
| Common Adverse Reactions | In patients with HR+/HER2- advanced breast cancer (PALOMA-2, palbociclib plus letrozole): neutropenia, leukopenia, infections, fatigue, nausea, alopecia, anaemia, diarrhoea, thrombocytopenia, decreased appetite, vomiting, asthenia, and peripheral neuropathy. In PALOMA-3 (palbociclib plus fulvestrant): neutropenia, leukopenia, fatigue, nausea, anaemia, stomatitis, headache, diarrhoea, thrombocytopenia, constipation, alopecia, vomiting, hot flush, decreased appetite, and epistaxis. Grade 3/4 haematological adverse reactions particularly neutropenia (Grade 3: 55%; Grade 4: 11% in PALOMA-2) are clinically dominant; neutropenia-related febrile episodes occurred in approximately 1.8% of palbociclib-treated patients. Non-haematological Grade 3/4 adverse events include fatigue, infections, and elevated liver function tests (ALT/AST elevation). |
| Drug Interactions | Palbociclib is primarily metabolised by CYP3A and sulfotransferase (SULT) enzyme SULT2A1. Strong CYP3A inhibitors (clarithromycin, itraconazole, ketoconazole, voriconazole, grapefruit products): substantially increase palbociclib plasma AUC avoid concurrent use; if unavoidable, reduce Ibrance dose to 75 mg once daily. Strong CYP3A inducers (rifampicin, rifabutin, phenytoin, carbamazepine, phenobarbital, St John’s Wort): significantly reduce palbociclib exposure avoid concurrent use; consider alternative agents with no or minimal CYP3A induction potential. Moderate CYP3A inducers (bosentan, efavirenz, modafinil): may reduce palbociclib exposure avoid if possible. CYP3A-sensitive substrates with narrow therapeutic indices (certain immunosuppressants, antiepileptics): palbociclib may inhibit CYP3A at therapeutic concentrations exercise clinical caution. Proton pump inhibitors (PPIs), H2 blockers, and antacids do not alter palbociclib pharmacokinetics significantly; palbociclib’s oral absorption is food-dependent and not pH-sensitive at therapeutic doses. Disclose all concomitant medications to the treating oncologist before initiating Ibrance. |
| Pregnancy & Lactation | Based on findings in animals and the mechanism of action of palbociclib, Ibrance can cause embryo-foetal harm when administered to a pregnant woman. No adequate and well-controlled studies of palbociclib use in pregnant women are available. Females of reproductive potential must use effective contraception during Ibrance therapy and for at least 3 weeks after the last dose. Male patients with female partners of reproductive potential should use effective contraception during treatment and for at least 3 months after the final dose. Verify pregnancy status with a serum or urine pregnancy test before initiating Ibrance in females of reproductive potential. It is not known whether palbociclib or its metabolites are present in human breast milk; breastfeeding is not recommended during Ibrance treatment and for 3 weeks after the last dose due to potential for serious adverse reactions in the nursing infant. Discuss pregnancy planning, contraceptive requirements, and reproductive intentions with the treating oncologist before and throughout Ibrance therapy. |
Who Should Use Ibrance 125 MG (Palbociclib)?
Ibrance (Palbociclib) is indicated across two clinically distinct settings of HR+/HER2- advanced or metastatic breast cancer, both defined by confirmed hormone receptor positivity (ER+ and/or PR+) and confirmed HER2-negativity as mandatory eligibility criteria, collectively representing the largest molecular subtype of metastatic breast cancer approximately 70% of all breast cancer cases for whom palbociclib’s selective CDK4/6 inhibition delivers a pharmacologically rational enhancement of endocrine-based therapy by blocking the core proliferative signalling pathway that sustains HR+ tumour growth.
First, postmenopausal women and men with HR+/HER2- advanced or metastatic breast cancer receiving initial endocrine-based therapy are the primary first-line indication for Ibrance: in the Phase 3 PALOMA-2 trial (n=666), palbociclib combined with letrozole extended median PFS to 24.8 months versus 14.5 months with letrozole alone (HR 0.58; p<0.001), representing a 10.3-month improvement in median PFS the largest absolute PFS improvement demonstrated in a first-line HR+/HER2- metastatic breast cancer trial at the time of PALOMA-2 publication. The investigator-assessed overall response rate (ORR) in patients with measurable disease was 55.3% in the palbociclib arm versus 44.4% in the letrozole-alone arm.
Second, pre/perimenopausal and postmenopausal women and men with HR+/HER2- advanced or metastatic breast cancer whose disease has progressed following endocrine therapy represent the second-line and later indication: the Phase 3 PALOMA-3 trial (n=521; palbociclib plus fulvestrant versus placebo plus fulvestrant) demonstrated a median PFS of 9.5 months versus 4.6 months (HR 0.46; p<0.0001) with a clinical benefit rate (CBR) of 34.0% versus 19.0% in palbociclib-treated patients, establishing palbociclib-fulvestrant as a standard-of-care second-line option. Pre/perimenopausal women enrolled in PALOMA-3 also received the GnRH agonist goserelin, a requirement that applies to clinical practice.
Ibrance is not appropriate in HER2-positive breast cancer; in patients with triple-negative breast cancer (ER-/PR-/HER2-); in patients with Grade 4 neutropenia who have not yet recovered to Grade ≤1 before initiation; or without confirmation of HR+ and HER2- status by validated immunohistochemistry (IHC) or in situ hybridisation (ISH) testing. Breast cancer treatment centres, oncology departments, hospital formulary and procurement teams, and individual patients and families sourcing palbociclib in regions where Ibrance may be unavailable at accessible pricing can browse the Mediaid Pharmacy breast cancer medicines portfolio, the oncology medicines collection, and the Pfizer medicines range for the complete selection available with worldwide delivery.
Global Supplier: Mediaid Pharmacy Worldwide Shipping for Ibrance 125 MG (Palbociclib)
Mediaid Pharmacy is a Dhaka-based supplier of specialty targeted oncology, breast cancer, and rare disease medicines with worldwide shipping to patients, breast oncology departments, HR+/HER2- metastatic breast cancer treatment programmes, hospital pharmacies, and international distributors across all regions. Ibrance (Palbociclib), manufactured by Pfizer Inc. in China-market packaging (Chinese name: 爱博新), is supplied as 125 mg hard capsules in a 21-capsule blister pack with pricing quotations, stock confirmation, full product documentation, and end-to-end international delivery tracking for every order. The 21-capsule pack format provides a clinically practical single 28-day treatment cycle at the standard palbociclib dose of 125 mg/day for 21 days followed by 7 days off, allowing breast oncology pharmacy teams and procurement specialists to calculate supply quantities accurately across treatment cycles: a patient on continuous Ibrance therapy at 125 mg (21/7 schedule) requires one 21-capsule pack per 28-day cycle 13 packs per year of uninterrupted treatment.
Breast oncology centres and academic cancer programmes managing postmenopausal women with newly diagnosed HR+/HER2- advanced breast cancer receiving first-line palbociclib-letrozole or palbociclib-anastrozole therapy; breast oncology units treating patients with HR+/HER2- advanced breast cancer progression on prior endocrine therapy using palbociclib-fulvestrant combinations; international oncology patient access programmes; hospital oncology formulary and procurement teams; and individual patients and families accessing Ibrance palbociclib 125mg in regions where cost or availability presents a barrier can contact the Mediaid Pharmacy team through WhatsApp, phone, or WeChat for all enquiries regarding Ibrance Palbociclib stock availability, current pricing, and international delivery timelines. Procurement teams co-sourcing Ibrance with other targeted oncology or breast cancer medicines can browse the complete Mediaid Pharmacy oncology medicines collection and the Pfizer medicines portfolio before requesting a consolidated quotation.
Why Choose Ibrance 125 MG (Palbociclib) from Mediaid Pharmacy?
Ibrance (Palbociclib) provides breast oncologists and HR+/HER2- metastatic breast cancer treatment teams with a Phase 3-validated, first-in-class CDK4/6 inhibitor whose selective cyclin D1–CDK4/6–Rb pathway inhibition mechanism is pharmacologically distinct from every other breast cancer drug class in clinical use including aromatase inhibitors (letrozole, anastrozole, exemestane), oestrogen receptor degraders (fulvestrant), mTOR inhibitors (everolimus), PI3Kα inhibitors (alpelisib), HER2-targeted antibodies (trastuzumab, pertuzumab), antibody-drug conjugates (trastuzumab emtansine, trastuzumab deruxtecan), and cytotoxic chemotherapy regimens conferring a mechanistically complementary therapeutic strategy for HR+/HER2- tumours whose growth depends on aberrant CDK4/6 activation downstream of oestrogen receptor signalling.
The clinical evidence base supporting palbociclib’s therapeutic value is anchored in three major randomised trials. The PALOMA-1 Phase 2 trial (n=165) first demonstrated that palbociclib combined with letrozole extended median PFS to 20.2 months versus 10.2 months with letrozole alone (HR 0.488; p=0.0004) in first-line postmenopausal HR+/HER2- advanced breast cancer the result that earned palbociclib its first FDA accelerated approval in February 2015 as the first CDK4/6 inhibitor ever approved in oncology. The Phase 3 PALOMA-2 confirmatory trial (n=666) validated this benefit at scale, demonstrating a median PFS of 24.8 months with palbociclib plus letrozole versus 14.5 months with letrozole alone (HR 0.58; p<0.001) a 10.3-month absolute PFS gain supporting Ibrance’s regular FDA approval in March 2016 and establishing CDK4/6 inhibition plus endocrine therapy as the global standard of care for first-line HR+/HER2- metastatic breast cancer.
The PALOMA-3 Phase 3 trial (n=521) extended this benefit to the second-line setting and to pre/perimenopausal women: palbociclib combined with fulvestrant delivered a median PFS of 9.5 months versus 4.6 months with fulvestrant alone (HR 0.46; p<0.0001), demonstrating that CDK4/6 inhibition remains effective after prior endocrine therapy and across all menopausal statuses. The oral once-daily administration of palbociclib at 125 mg one Ibrance 125 MG capsule taken with food offers significant practical advantages over intravenous chemotherapy: patients maintain Ibrance therapy entirely as outpatient treatment, avoiding hospitalisation, infusion-related complications, and the quality-of-life burden of cytotoxic chemotherapy regimens, particularly relevant in the metastatic breast cancer population where sustained quality of life during long-term therapy is a primary treatment goal.
Ibrance is manufactured by Pfizer Inc. and is available through Mediaid Pharmacy as 125 mg hard capsules in a 21-capsule China-market pack (爱博新) with full product documentation, specialist supply coordination, and worldwide shipping from Dhaka. To source additional Pfizer oncology medicines, visit the Mediaid Pharmacy Pfizer medicines section and the breast cancer medicines portfolio, and contact the team for a personalised quotation.
Frequently Asked Questions About Ibrance 125 MG (Palbociclib)
What is Ibrance 125 MG (Palbociclib) used for?
Ibrance 125 MG (Palbociclib) is a first-in-class selective CDK4/6 inhibitor indicated for two settings of hormone receptor-positive, HER2-negative (HR+/HER2-) advanced or metastatic breast cancer: (1) in combination with an aromatase inhibitor (letrozole or anastrozole) as initial endocrine-based therapy in postmenopausal women and in men; and (2) in combination with fulvestrant in pre/perimenopausal and postmenopausal women and in men whose disease has progressed following prior endocrine therapy (pre/perimenopausal women also require a GnRH agonist). Palbociclib acts by selectively inhibiting CDK4 and CDK6, blocking CDK4/6-mediated phosphorylation of the retinoblastoma protein (Rb), arresting tumour cell cycle progression at the G1-to-S phase transition, and halting proliferation of HR+ breast cancer cells dependent on cyclin D1–CDK4/6–Rb signalling a mechanism that is synergistic with oestrogen-suppressing endocrine therapy. Ibrance is manufactured by Pfizer Inc. and available through Mediaid Pharmacy with worldwide shipping in China-market packaging (爱博新) as 125 mg hard capsules in 21-capsule packs.
What is the generic name of Ibrance?
The generic name of Ibrance is palbociclib INN. Ibrance is the originator brand name registered by Pfizer Inc. for palbociclib the first CDK4/6 inhibitor to receive regulatory approval anywhere in the world (FDA accelerated approval February 3, 2015 for HR+/HER2- advanced breast cancer in combination with letrozole). Ibrance is formulated as hard capsules in three strengths: 125 mg (recommended starting dose), 100 mg, and 75 mg, with each strength supplied in a 21-capsule blister pack equivalent to one complete 28-day treatment cycle on the 21-day on / 7-day off schedule. The China-market packaging of Ibrance 125 MG carries the Chinese brand name 爱博新 (Àibóxīn). Unlike the IDH1 inhibitor drug class (ivosidenib, enasidenib) and FLT3 inhibitors (midostaurin, gilteritinib) where alternative-manufacturer versions are available in certain markets palbociclib 125 mg remains exclusively available as the originator Pfizer Ibrance product; no generic palbociclib has received regulatory approval as of 2024. Mediaid Pharmacy distributes Ibrance (Palbociclib) 125 MG globally with worldwide shipping to patients, breast oncology clinics, hospital pharmacies, and HR+/HER2- breast cancer treatment programmes.
What is the difference between Ibrance (Palbociclib), Kisqali (Ribociclib), and Verzenio (Abemaciclib)?
Ibrance (palbociclib), Kisqali (ribociclib), and Verzenio (abemaciclib) are all CDK4/6 inhibitors approved for HR+/HER2- advanced or metastatic breast cancer and share the same core mechanism of CDK4/6 inhibition and Rb-mediated G1 cell cycle arrest. Key clinical distinctions include dosing schedule, CDK selectivity profile, adverse event profiles, and approved indications. Ibrance (palbociclib, Pfizer) is administered at 125 mg once daily for 21 days followed by 7 days off (21/7 schedule) in each 28-day cycle and is approved only in the advanced/metastatic setting; its dominant adverse effect is neutropenia, with QTc prolongation not required to be monitored (unlike ribociclib). Kisqali (ribociclib, Novartis) uses a similar 21/7 schedule but requires baseline and serial ECG monitoring for QTc prolongation and has demonstrated overall survival benefit across multiple Phase 3 trials (MONALEESA-2, -3, -7), including in premenopausal women. Verzenio (abemaciclib, Lilly) is the only CDK4/6 inhibitor approved for continuous daily dosing (without a 7-day off-treatment break), has a more prominent diarrhoea adverse effect profile relative to neutropenia, and holds an additional adjuvant breast cancer indication (MONARCH E trial) for high-risk early HR+/HER2- breast cancer with 4 or more positive lymph nodes or 1–3 positive lymph nodes with additional high-risk features. All three CDK4/6 inhibitors are available through Mediaid Pharmacy; visit the breast cancer medicines collection for the full range.
How is Ibrance 125 MG (Palbociclib) administered?
Ibrance is administered orally at 125 mg once daily for 21 consecutive days followed by 7 days off, constituting one complete 28-day cycle. Ibrance must be taken with food taking palbociclib without food significantly reduces its oral bioavailability; a standard meal (not high-fat) at the time of administration is sufficient and consistent food intake at each dose is recommended to maintain stable palbociclib plasma concentrations throughout the 21-day treatment period. Swallow Ibrance capsules whole do not open, crush, or chew them. Take Ibrance at approximately the same time each day. Ibrance is always administered in combination with letrozole, anastrozole, or fulvestrant depending on menopausal status and line of therapy; pre/perimenopausal women receiving Ibrance in combination with fulvestrant must concurrently receive a GnRH agonist. If a dose is missed and the next scheduled dose is more than 12 hours away, take the missed dose as soon as possible; if it is within 12 hours of the next scheduled dose, skip the missed dose and resume the normal dosing schedule. Do not take an additional capsule to replace a vomited dose. All dose modifications including reductions to 100 mg or 75 mg once daily for Grade 3 or 4 neutropenia or other adverse reactions must be directed by the treating oncologist. Do not initiate the next cycle of Ibrance until the absolute neutrophil count (ANC) has recovered to ≥1,000/mm³.
What are the side effects of Ibrance 125 MG (Palbociclib)?
The most clinically significant adverse effect of palbociclib (Ibrance) is neutropenia. In the PALOMA-2 trial (palbociclib plus letrozole), Grade 3 neutropenia occurred in 55% and Grade 4 in 11% of palbociclib-treated patients; the median time to onset of Grade 3 or greater neutropenia was 15 days (beginning of Cycle 1), and the median duration was 7 days. Febrile neutropenia occurred in approximately 1.8% of patients substantially lower than neutropenia rates might suggest, reflecting the predominantly uncomplicated and reversible nature of palbociclib-induced neutropenia during the 7-day off-treatment period. Other common adverse reactions in HR+/HER2- advanced breast cancer patients (PALOMA-2) include infections (primarily upper respiratory tract infections), fatigue, nausea, alopecia, anaemia, diarrhoea, thrombocytopenia, decreased appetite, vomiting, asthenia, and peripheral neuropathy. Interstitial lung disease (ILD) and pneumonitis, including fatal cases, have been reported during palbociclib therapy symptoms include new or worsening pulmonary symptoms such as dyspnoea, cough, and hypoxia, and warrant immediate clinical evaluation. Liver function test (ALT/AST) elevations occur in a minority of patients; monitor LFTs periodically. The 7-day off-treatment period in each cycle is specifically designed to allow haematopoietic recovery from palbociclib-induced myelosuppression; establish baseline CBC before each cycle and on Day 15 of the first two cycles to guide dose management. Always manage Ibrance therapy under the supervision of an experienced oncologist with structured neutrophil count monitoring throughout treatment.
How effective is Palbociclib (Ibrance) for HR+/HER2- metastatic breast cancer?
Palbociclib has demonstrated clinically meaningful and statistically significant efficacy across its approved settings in three major Phase 2 and Phase 3 randomised controlled trials. In the first-line setting, the Phase 3 PALOMA-2 trial (n=666; palbociclib plus letrozole versus letrozole alone; postmenopausal women with HR+/HER2- advanced breast cancer) achieved a median PFS of 24.8 months versus 14.5 months (HR 0.58; 95% CI 0.46–0.72; p<0.001) a 10.3-month absolute median PFS improvement, with an ORR of 55.3% versus 44.4% in patients with measurable disease. In the second-line and later setting, the Phase 3 PALOMA-3 trial (n=521; palbociclib plus fulvestrant versus fulvestrant alone; pre/perimenopausal and postmenopausal women with HR+/HER2- advanced breast cancer after prior endocrine therapy) demonstrated a median PFS of 9.5 months versus 4.6 months (HR 0.46; 95% CI 0.36–0.59; p<0.0001) a near-doubling of median PFS with a clinical benefit rate (CBR, defined as CR + PR + SD ≥24 weeks) of 34.0% versus 19.0% in the palbociclib arm. The Phase 2 PALOMA-1 trial (n=165; the trial that earned palbociclib’s accelerated approval) demonstrated a median PFS of 20.2 months versus 10.2 months in first-line HR+/HER2- advanced breast cancer. These findings established palbociclib-based CDK4/6 inhibitor combinations as the global standard of care in HR+/HER2- metastatic breast cancer and define the PALOMA clinical programme as one of the most impactful trial series in the history of breast cancer therapeutics. Ibrance delivers palbociclib INN at 125 mg in hard capsules, sourced through Mediaid Pharmacy with worldwide shipping. Visit the oncology medicines collection for the full targeted therapy range.
Is Ibrance 125 MG (Palbociclib) safe during pregnancy or while breastfeeding?
Based on findings in animals and palbociclib’s mechanism of action as a cell cycle inhibitor, Ibrance can cause embryo-foetal harm when administered during pregnancy; no adequate and well-controlled human pregnancy studies are available. Ibrance should not be used during pregnancy; if treatment is required, the potential benefit to the patient must clearly outweigh the risk to the foetus, with explicit documented specialist risk-benefit assessment. Females of reproductive potential must use effective contraception during Ibrance therapy and for at least 3 weeks after the last dose; palbociclib does not have a CYP3A4-inducing effect on hormonal contraceptives (unlike some other targeted agents), so hormonal contraception is not specifically contraindicated by a drug interaction mechanism, but the treating oncologist must guide contraceptive choices. Male patients with female partners of reproductive potential should use effective contraception during treatment and for at least 3 months after the final dose, given palbociclib’s potential for genotoxicity in spermatogonia. Verify pregnancy status with a serum or urine pregnancy test before initiating Ibrance in females of reproductive potential. It is not known whether palbociclib or its metabolites are excreted in human breast milk; breastfeeding is not recommended during Ibrance treatment and for 3 weeks after the last dose due to the potential for serious adverse effects in the nursing infant. Discuss pregnancy planning, fertility preservation, contraceptive requirements, and reproductive intentions explicitly with the treating oncologist before and throughout Ibrance therapy.
Can I order Ibrance 125 MG (Palbociclib) online with worldwide shipping?
Yes. Mediaid Pharmacy supplies Ibrance 125 MG (Palbociclib) 21 hard capsules per blister pack, China-market packaging (爱博新), manufactured by Pfizer Inc. to patients, breast oncology and medical oncology departments, HR+/HER2- metastatic breast cancer treatment centres, hospital pharmacies, oncology patient access programmes, and healthcare providers globally. Contact Mediaid Pharmacy via WhatsApp, phone, or WeChat at +8801773428128, or email info@mediaidpharmacy.com for pricing, current stock availability, and international delivery details for your country.
Order Ibrance 125 MG (Palbociclib) with Worldwide Shipping
Phone / WhatsApp / WeChat: +8801773428128 | Email: info@mediaidpharmacy.com



