
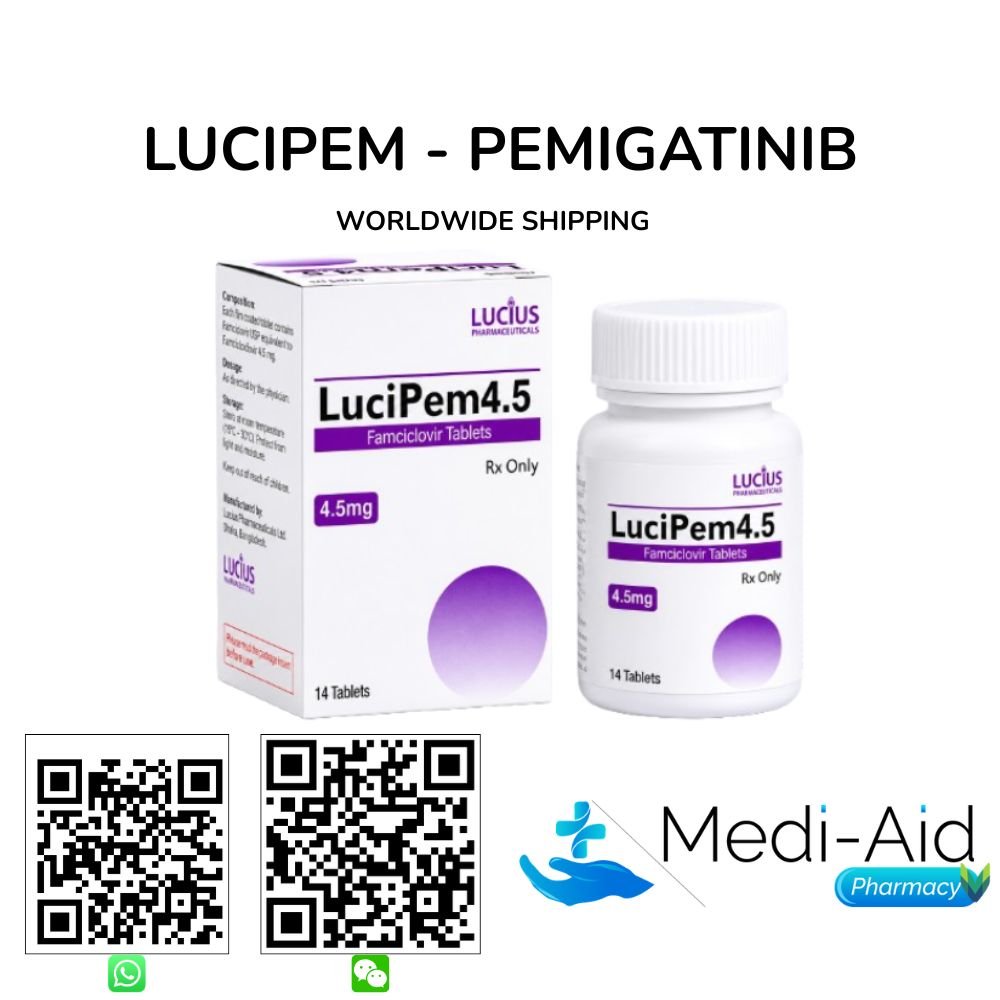
Description
LuciPem 4.5 MG (Pemigatinib) is a highly selective, potent, reversible ATP-competitive pan-FGFR1-3 inhibitor tablet manufactured by Lucius Pharmaceuticals (Lao) Co., Ltd. in Laos, supplied as 14 tablets per bottle or box. Pemigatinib is indicated for previously treated, unresectable, locally advanced or metastatic cholangiocarcinoma with FGFR2 gene fusions or rearrangements. The recommended dose is 13.5 mg orally once daily (3 × LuciPem 4.5 mg tablets) for 14 consecutive days of a 21-day cycle, taken with or without food. Available globally through Mediaid Pharmacy with worldwide shipping. Contact: +8801773428128 (WhatsApp/Phone/WeChat) | info@mediaidpharmacy.com.
| Brand Name | LuciPem 4.5 MG (Pemigatinib) |
| Product Name | LuciPem |
| Generic Name | Pemigatinib (International Nonproprietary Name, INN) |
| Drug Class | Highly Selective Reversible ATP-Competitive Pan-FGFR1-3 Inhibitor; Targeted Oral Oncology Agent; FGFR2 Fusion-Directed Biliary Tract Cancer Therapy; Kinase Inhibitor |
| Formulation | Tablet (Oral; may be taken with or without food; administered for 14 consecutive days of a 21-day treatment cycle, followed by a 7-day off period, until disease progression or unacceptable toxicity) |
| Available Strength | 4.5 mg Pemigatinib per tablet |
| Available Pack Size | 14 Tablets per Bottle or Box. At the standard 13.5 mg daily dose (3 × LuciPem 4.5 mg tablets per day for 14 consecutive days), one complete 21-day treatment cycle requires 42 tablets (3 × 14-tablet bottles). At the first dose reduction of 9 mg/day (2 tablets), 28 tablets (2 × 14-tablet bottles) are required per cycle. At the second dose reduction of 4.5 mg/day (1 tablet), 14 tablets (1 bottle) are required per cycle. |
| Therapeutic Category | Bile Duct Cancer Medicines; Oncology Medicines; FGFR Inhibitors; Targeted Biliary Tract Cancer Therapies; Lucius Pharmaceuticals Medicines |
| Approved Indication | Cholangiocarcinoma with FGFR2 Gene Fusions or Rearrangements: Treatment of adults with previously treated, unresectable, locally advanced or metastatic cholangiocarcinoma harboring FGFR2 gene fusions or other rearrangements, as detected by an approved companion diagnostic test. Pemigatinib is the most extensively studied reversible FGFR inhibitor in biliary tract cancer, validated in both second-line (FIGHT-202 Phase 2) and first-line (FIGHT-302 Phase 3) settings in FGFR2-altered cholangiocarcinoma. Pemigatinib requires prior FGFR2 biomarker testing before initiation. In FIGHT-302, pemigatinib significantly improved PFS (9.1 vs 5.4 months; HR 0.56) and ORR (34.9% vs 12.5%) versus gemcitabine plus cisplatin in first-line FGFR2-altered cholangiocarcinoma. |
| Recommended Dose | Standard Dose: 13.5 mg orally once daily (3 × LuciPem 4.5 mg tablets simultaneously), taken with or without food, for 14 consecutive days of a 21-day cycle, followed by a 7-day off period. First Dose Reduction: 9 mg once daily (2 × LuciPem 4.5 mg tablets). Second Dose Reduction: 4.5 mg once daily (1 × LuciPem 4.5 mg tablet). Permanently discontinue if 4.5 mg is not tolerated. |
| Manufacturer | Lucius Pharmaceuticals (Lao) Co., Ltd., Laos |
| Country of Origin | Laos (Lao People’s Democratic Republic) |
| Originator Reference Brand | Pemazyre (Pemigatinib tablets, Incyte Corporation), approved by the U.S. FDA on April 17, 2020, as the first selective FGFR inhibitor for previously treated FGFR2 fusion/rearrangement-positive cholangiocarcinoma. LuciPem contains Pemigatinib INN at the same clinically validated 4.5 mg oral tablet strength as the Pemazyre originator formulation, manufactured by Lucius Pharmaceuticals (Lao) Co., Ltd. in Laos and supplied through Mediaid Pharmacy for international procurement. |
| Global Supplier | Mediaid Pharmacy, Worldwide Shipping Available |
| Storage Conditions | Store at controlled room temperature (20°C to 25°C); excursions permitted between 15°C and 30°C. Keep in the original bottle or box with the closure tightly sealed. Protect from moisture and light. Keep out of the reach of children. |
What Is LuciPem 4.5 MG (Pemigatinib)?
LuciPem 4.5 MG (Pemigatinib) is a highly selective, potent, reversible ATP-competitive pan-FGFR1-3 (fibroblast growth factor receptor 1, 2, and 3) inhibitor tablet for the treatment of adults with previously treated, unresectable, locally advanced or metastatic cholangiocarcinoma harboring FGFR2 gene fusions or other rearrangements, manufactured by Lucius Pharmaceuticals (Lao) Co., Ltd. in Laos. Each LuciPem tablet contains 4.5 mg of Pemigatinib a potent, highly selective small-molecule kinase inhibitor that occupies the ATP-binding pocket of FGFR1, FGFR2, and FGFR3 kinase domains through reversible, non-covalent competitive inhibition with IC50 values of 0.4 nM (FGFR1), 0.5 nM (FGFR2), and 1.2 nM (FGFR3), achieving more than 70-fold selectivity for FGFR1-3 over FGFR4 (IC50 approximately 30 nM) at clinically relevant plasma concentrations. This exceptional FGFR1-3 potency and FGFR4 selectivity distinguish pemigatinib as the most potent and selective reversible FGFR1-3 inhibitor among approved FGFR-targeted agents, and are the molecular basis for its favorable pharmacological profile in FGFR2 gene fusion-positive biliary tract cancer.
LuciPem 4.5 MG tablets represent the Lucius Pharmaceuticals (Lao) formulation of pemigatinib the same active ingredient as the originator brand Pemazyre (Incyte Corporation, U.S. FDA approved April 17, 2020) at the same clinically validated 4.5 mg oral tablet strength. The recommended therapeutic dose is 13.5 mg orally once daily (3 × LuciPem 4.5 mg tablets, taken simultaneously) for 14 consecutive days of a 21-day treatment cycle, followed by a mandatory 7-day off period, at approximately the same time each day. Notably, LuciPem (Pemigatinib) may be taken with or without food a meaningful clinical advantage over FGFR inhibitors that require strict fasting administration, as it simplifies patient adherence and removes a pharmacokinetically critical compliance variable that can substantially affect therapeutic drug exposure with other agents.
In the pivotal Phase 2 FIGHT-202 trial (N=107), pemigatinib achieved a confirmed objective response rate (ORR) of 35.5% in previously treated FGFR2 fusion/rearrangement-positive cholangiocarcinoma patients the highest confirmed ORR reported in a pivotal Phase 2 trial among approved reversible FGFR inhibitors in this indication a disease control rate (DCR) of 82.2%, a median duration of response of 9.1 months, a median PFS of 6.9 months, and a median OS of 17.5 months. In the subsequent Phase 3 FIGHT-302 trial, pemigatinib became the first FGFR inhibitor to demonstrate superior progression-free survival over gemcitabine plus cisplatin in the first-line treatment of FGFR2-altered cholangiocarcinoma (median PFS 9.1 vs 5.4 months; HR 0.56; 95% CI: 0.41–0.77; ORR 34.9% vs 12.5%), establishing pemigatinib as the most extensively clinically validated reversible FGFR inhibitor in biliary tract cancer. LuciPem is available globally through Mediaid Pharmacy’s bile duct cancer medicines portfolio with worldwide shipping.
Mechanism of Action of LuciPem: Highly Selective Reversible ATP-Competitive Pan-FGFR1-3 Inhibition
LuciPem (Pemigatinib) exerts its antitumor activity through highly selective, reversible, competitive inhibition of FGFR1, FGFR2, and FGFR3 kinase isoforms with exceptional nanomolar potency (IC50: FGFR1 0.4 nM, FGFR2 0.5 nM, FGFR3 1.2 nM) and more than 70-fold selectivity for FGFR1-3 over FGFR4 with particular clinical relevance in cholangiocarcinoma driven by constitutively activating FGFR2 gene fusions or rearrangements. Pemigatinib’s combination of subnanomolar FGFR1-2 potency and high FGFR4 selectivity establishes it as the most potent and selective reversible FGFR1-3 inhibitor among approved agents, with direct implications for both clinical efficacy and hepatic safety in biliary tract cancer patients.
FGFR Signaling Biology The Oncogenic Pathway Targeted by Pemigatinib: The fibroblast growth factor receptors (FGFR1–4) are receptor tyrosine kinases (RTKs) that, upon ligand (FGF1–23) binding and receptor dimerization, activate intracellular kinase domains through trans-autophosphorylation and initiate downstream signal transduction through the RAS–MEK–ERK (MAPK) cascade, the PI3K–AKT–mTOR pathway, the JAK-STAT3 pathway, and the PLC-γ pathway collectively promoting tumor cell proliferation, survival, angiogenesis, invasion, and epithelial-to-mesenchymal transition.
In FGFR2 gene fusion-positive intrahepatic cholangiocarcinoma, chromosomal rearrangements fuse the FGFR2 kinase domain-encoding sequence to a partner gene (the most common partner is BICC1; more than 100 distinct fusion partners have been identified, including AHCYL1, CCDC6, PPHLN1, TACC3, and KIAA1217), producing a chimeric FGFR2 fusion oncoprotein that dimerizes constitutively through its partner domain activating FGFR2 kinase independently of FGF ligand binding and driving continuous, unrestrained RAS-MAPK and PI3K-AKT-mTOR oncogenic signaling in iCCA cells. FGFR2 fusions occur in approximately 10–16% of intrahepatic cholangiocarcinoma cases, establishing FGFR2 as the most actionable oncogenic driver in iCCA and the defining molecular target for pemigatinib therapy.
Pemigatinib’s Reversible ATP-Competitive Binding Mechanism and Exceptional FGFR1-3 Potency: Pemigatinib is a morpholino-substituted pyrimidine compound specifically engineered for high-affinity, selective binding to the ATP-binding cleft of FGFR1, FGFR2, and FGFR3 kinase domains through optimized non-covalent hydrogen bonding interactions with the kinase hinge region residues, hydrophobic packing interactions with the ATP-pocket hydrophobic spine, and additional binding contacts that account for the compound’s exceptional subnanomolar potency. Pemigatinib’s IC50 values of 0.4 nM (FGFR1), 0.5 nM (FGFR2), and 1.2 nM (FGFR3) reflect binding affinities more than an order of magnitude tighter than many other approved FGFR inhibitors, enabling near-complete saturation of FGFR kinase active sites at therapeutically achievable plasma concentrations.
By occupying the FGFR2 ATP pocket in FGFR2 gene fusion-positive cholangiocarcinoma cells, pemigatinib competitively displaces ATP from the catalytic site and blocks the phosphoryl transfer reaction that initiates downstream FGFR signaling, suppressing constitutive FGFR2 autophosphorylation, adapter protein recruitment (FRS2, Grb2, SOS), and downstream RAS-MEK-ERK and PI3K-AKT-mTOR pathway activation reducing cholangiocarcinoma cell proliferation, survival signaling, and tumor angiogenesis.
FGFR4 Selectivity Clinical Significance of Pemigatinib’s Hepatic Safety Profile: Pemigatinib’s IC50 of approximately 30 nM against FGFR4 more than 70-fold less potent than its FGFR1-3 activity is not a limitation but a deliberate pharmacological feature that confers important clinical advantages in cholangiocarcinoma, a biliary cancer in which patients frequently present with pre-existing hepatic dysfunction, biliary obstruction, and compromised hepatic reserve. FGFR4 is the primary hepatic FGFR isoform and governs bile acid synthesis through the FGF19-FGFR4-SHP2 pathway, which suppresses hepatic CYP7A1 expression and limits cholesterol-to-bile acid conversion; FGFR4 inhibition disrupts this hepatic bile acid homeostasis, causes FGFR4-mediated hepatocellular injury, steatohepatitis, cholestasis, and hepatotoxicity signals observed with broad-spectrum pan-FGFR1-4 inhibitors in clinical and preclinical studies.
At clinically relevant pemigatinib plasma concentrations (approximately 1–10 nM), FGFR4 (IC50 ~30 nM) is minimally inhibited, preserving hepatic FGF19-FGFR4 bile acid homeostasis and minimizing the FGFR4-mediated hepatic injury risk translating to a favorable hepatic safety profile that is critically important in cholangiocarcinoma patients with compromised baseline hepatic function. This high FGFR4 selectivity, combined with the absence of a fasting requirement, makes LuciPem (Pemigatinib) particularly well-suited for FGFR2 fusion-positive cholangiocarcinoma patients with concurrent hepatic dysfunction or biliary obstruction.
The 14-Day On/7-Day Off Intermittent Dosing Cycle Pharmacodynamic Rationale: The standard pemigatinib dosing schedule of 14 consecutive days on followed by 7 days off in each 21-day cycle was designed to manage the on-target pharmacodynamic consequence of FGFR1 inhibition on renal phosphate homeostasis. FGFR1 signaling in the renal proximal tubule mediates FGF23-dependent suppression of sodium-phosphate cotransporter (NaPi-IIa/NaPi-IIc) expression, enabling urinary phosphate excretion; FGFR1-3 inhibition by pemigatinib blocks this FGF23-FGFR1 axis, reducing renal phosphate clearance and producing pharmacodynamically predictable hyperphosphatemia proportional to FGFR inhibitory drug exposure.
The 7-day off period within each 21-day cycle allows reversible pemigatinib dissociation from FGFR kinase domains, FGFR kinase activity recovery, FGF23-FGFR1-mediated phosphate excretion restoration, and serum phosphate normalization before the next 14-day active treatment period creating a pharmacodynamically self-correcting cycle that limits cumulative Grade 3+ hyperphosphatemia burden and enables sustained multi-cycle FGFR-targeted treatment with manageable class-effect toxicity.
LuciPem 4.5 MG (Pemigatinib): Dosing by Patient Setting and Clinical Situation
| Clinical Setting / Parameter | Recommended Pemigatinib (LuciPem) Dosing |
|---|---|
| Standard Recommended Dose | 13.5 mg orally once daily for 14 consecutive days of a 21-day treatment cycle (3 × LuciPem 4.5 mg tablets taken simultaneously), taken with or without food at approximately the same time each day, followed by a 7-day off period. Continue until disease progression or unacceptable toxicity. At the standard dose, each 21-day cycle requires 42 tablets (3 × 14-tablet bottles of LuciPem 4.5 MG). |
| First Dose Reduction | 9 mg orally once daily for 14 days of a 21-day cycle (2 × LuciPem 4.5 mg tablets), taken with or without food, followed by 7-day off. Required 28 tablets (2 × 14-tablet bottles) per cycle. Applied for Grade 3 or intolerable Grade 2 adverse reactions that do not resolve to ≤Grade 1 with supportive care at the standard dose. |
| Second Dose Reduction | 4.5 mg orally once daily for 14 days of a 21-day cycle (1 × LuciPem 4.5 mg tablet), taken with or without food, followed by 7-day off. Requires 14 tablets (1 × 14-tablet bottle) per cycle. Applied for recurrent Grade 3 or Grade 4 adverse reactions at the 9 mg dose level. |
| Permanent Discontinuation | Permanently discontinue LuciPem if 4.5 mg is not tolerated, or for: Grade 4 RPED, Grade 4 non-hematologic toxicity, Grade 4 hyperphosphatemia unresponsive to maximal management, recurrent Grade 3+ toxicity after maximum dose reductions, or severe drug-induced liver injury meeting Hy’s Law criteria. |
| Food Effect | LuciPem (Pemigatinib) may be taken with or without food. Food does not significantly alter pemigatinib systemic bioavailability at clinically relevant doses, eliminating the fasting compliance requirement associated with other FGFR inhibitors and simplifying daily administration for patients. |
| Missed Dose | If a dose is missed or vomited, take the next dose at the regularly scheduled time. Do not take two doses on the same day to make up for a missed dose. Resume the regular dosing schedule the following day. |
| Renal Impairment | No dose adjustment required for mild to moderate renal impairment (eGFR ≥30 mL/min/1.73 m²). Pemigatinib pharmacokinetics in severe renal impairment (eGFR <30 mL/min/1.73 m²) are not fully established; monitor renal function and serum phosphate throughout LuciPem treatment in patients with pre-existing renal disease, as reduced renal phosphate clearance at baseline compounds FGFR inhibitor-mediated hyperphosphatemia risk. |
| Hepatic Impairment | No dose adjustment required for mild hepatic impairment (Child-Pugh A). For moderate hepatic impairment (Child-Pugh B): reduce the starting dose of LuciPem to 9 mg (2 × 4.5 mg tablets) once daily for 14 days of a 21-day cycle. Severe hepatic impairment (Child-Pugh C): not recommended; pemigatinib pharmacokinetics are substantially altered and safety data are insufficient. Consult the treating hepatobiliary oncologist before initiating LuciPem in any patient with hepatic impairment. |
LuciPem (Pemigatinib): Safety Profile, Adverse Reactions, and Clinical Management
| Adverse Reaction / Safety Concern | Clinical Frequency, Mechanism, and Management |
|---|---|
| Hyperphosphatemia | Hyperphosphatemia is the most frequent adverse reaction with LuciPem (Pemigatinib), occurring in approximately 67–70% of patients (Grade 3 in approximately 30%), and is a direct on-target consequence of pemigatinib’s potent FGFR1 inhibition disrupting FGF23-mediated renal tubular phosphate excretion via sodium-phosphate cotransporter (NaPi-IIa/NaPi-IIc) suppression. The 7-day off period built into each 21-day LuciPem cycle is specifically designed to allow serum phosphate to normalize between 14-day treatment periods by restoring FGF23-FGFR1 renal phosphate excretion during the drug-free interval. Management during the 14-day on period: implement low-phosphate diet (target dietary phosphate intake <800 mg/day, emphasizing restriction of dairy products, processed foods, and phosphate food additives), administer oral phosphate binders (sevelamer carbonate, lanthanum carbonate, or calcium carbonate) with each phosphate-containing meal and snack, monitor serum phosphate at baseline, weekly during Cycle 1, and at the start of each subsequent cycle, and withhold LuciPem for Grade 3+ hyperphosphatemia unresponsive to maximal dietary restriction and phosphate binder optimization until resolution to ≤Grade 1 before resuming at a reduced dose level. The 7-day off period serves as a built-in pharmacodynamic phosphate reset, distinguishing the LuciPem 14/7-day schedule from continuous daily dosing approaches. |
| Diarrhea | Diarrhea is the second most frequent adverse reaction with LuciPem (Pemigatinib), occurring in approximately 47% of patients (Grade 3 in approximately 3–5%), manifesting as loose, watery stools occurring more than 3 times above baseline per day during the 14-day treatment period. Diarrhea with pemigatinib is generally mild to moderate in severity, transient, and manageable with antidiarrheal therapy, representing a higher frequency but typically lower severity than the hyperphosphatemia and stomatitis that predominate with other FGFR inhibitors. Management: initiate loperamide (Imodium) 4 mg at first loose stool followed by 2 mg after each loose stool to a maximum of 16 mg/day for Grade 1–2 diarrhea; maintain adequate oral hydration (2–3 liters of clear fluids daily); adopt a low-fiber, low-fat BRAT-adjacent diet (bananas, rice, applesauce, boiled potatoes) during acute episodes; optimize electrolyte replacement (oral rehydration salts or potassium supplementation as needed). For Grade 3 diarrhea (≥7 stools above baseline per day, limiting self-care activities, or requiring IV hydration): withhold LuciPem until resolution to ≤Grade 1, then resume at a reduced dose level. For dehydrating Grade 3+ diarrhea failing oral management: hospitalization with IV fluid and electrolyte replacement may be required. |
| Retinal Pigment Epithelial Detachment (RPED) | Retinal pigment epithelial detachment (RPED), also referred to as central serous retinopathy (CSR) in the FGFR inhibitor context, is a recognized ocular adverse reaction of FGFR inhibitors including pemigatinib, caused by accumulation of subretinal fluid beneath the retinal pigment epithelium (RPE) due to FGFR inhibition of RPE cell tight junction integrity and ion transporter function. RPED occurred in approximately 5% of pemigatinib-treated patients in clinical studies, with most cases being asymptomatic or mildly symptomatic (mild blurred vision, metamorphopsia, or visual field changes) at diagnosis and resolving or stabilizing with dose modification. Ophthalmologic assessment (dilated fundus examination and optical coherence tomography, OCT) is required at baseline before initiating LuciPem, monthly during the first 3 months of treatment, and every 3 months thereafter; patients should be instructed to report any new visual symptoms (blurred vision, visual field defects, flashing lights, scotomas) between scheduled assessments. For asymptomatic Grade 1 RPED: continue LuciPem at the same dose with monthly ophthalmologic monitoring. For symptomatic Grade 2 RPED: withhold LuciPem, perform urgent ophthalmologic evaluation (OCT within 1 week), and resume at a reduced dose upon improvement to ≤Grade 1. For Grade 4 RPED (best corrected visual acuity worse than 20/200 in the affected eye): permanently discontinue LuciPem. Dry eye syndrome, occurring in approximately 26% of pemigatinib-treated patients, is a distinct and more common but less serious ocular adverse reaction managed with preservative-free artificial tear eye drops (applied at least 4 times daily), lubricating ophthalmic gels at bedtime, and avoidance of contact lens wear during LuciPem therapy. |
| Alopecia and Cutaneous Toxicity | Alopecia (hair loss) occurs in approximately 43% of pemigatinib-treated patients the highest alopecia frequency among approved FGFR inhibitors and is a class effect of FGFR inhibition on hair follicle keratinocyte FGFR signaling governing the anagen-catagen hair cycle transition, affecting scalp, eyebrows, eyelashes, and body hair in varying degrees. Alopecia does not require LuciPem dose modification; management includes supportive counseling on expected timing (typically onset by Cycle 2–4), scalp cooling if available and appropriate, use of gentle, sulfate-free shampoos and conditioners, soft scalp massage to maintain follicular circulation, and discussion of wig or hair covering options with the treating oncology team. Dry skin (xerosis) occurs in a substantial proportion of patients and is managed with fragrance-free emollient moisturizers applied immediately after bathing while skin is still slightly damp, non-soap cleansing bars, and avoidance of hot water bathing. Palmar-plantar erythrodysesthesia (PPE), occurring in approximately 13% of patients, is managed with urea-containing (10–20%) emollient creams applied twice daily, avoidance of friction and pressure on palms and soles, padded footwear, and dose modification for Grade 3+ PPE limiting self-care activities. |
| Stomatitis and Oral Toxicity | Stomatitis (oral mucositis, mouth sores) occurs in approximately 28% of pemigatinib-treated patients (Grade 3 in approximately 4–6%), manifesting as painful oral mucosal ulceration on the buccal mucosa, tongue, gingiva, and palate that can impair oral intake and nutritional status if not proactively managed. Prevention and management: conduct dental evaluation and address pre-existing oral pathology before initiating LuciPem; use a non-alcohol-based antimicrobial mouthwash (chlorhexidine 0.12%) twice daily throughout the 14-day treatment period; apply topical corticosteroid mouthwash (dexamethasone 0.5 mg/5 mL) or Magic Mouthwash formulations for symptomatic Grade 1–2 stomatitis; avoid mouthwashes containing alcohol, hydrogen peroxide, iodine, or thyme derivatives; maintain adequate oral hydration with cool, non-acidic fluids; for Grade 3 stomatitis (severe pain, inability to eat), withhold LuciPem until improvement to ≤Grade 1, then resume at a reduced dose. Dry mouth (xerostomia) occurring in approximately 24% of patients is managed with frequent sips of water, sugar-free candies or chewing gum to stimulate saliva flow, and salivary substitutes. |
| Drug Interactions CYP3A4 Inhibitors/Inducers | Pemigatinib is primarily metabolized by CYP3A4, making CYP3A4 modulator co-administration the most clinically significant drug interaction category for LuciPem. Strong CYP3A4 inhibitors (azole antifungals itraconazole, voriconazole, posaconazole, ketoconazole, fluconazole; clarithromycin; ritonavir; cobicistat; grapefruit and Seville orange products) may substantially increase pemigatinib systemic plasma exposure by 2-fold or more reduce the LuciPem dose by approximately 50% (from 13.5 mg to 9 mg once daily, or from 9 mg to 4.5 mg) when co-administration is unavoidable and cannot be substituted; monitor closely for increased adverse reactions. Strong CYP3A4 inducers (rifampin, carbamazepine, phenytoin, phenobarbital, enzalutamide, apalutamide, St. John’s Wort, lumacaftor) may reduce pemigatinib plasma concentrations by 80% or more, substantially reducing therapeutic FGFR inhibitory exposure avoid co-administration and substitute non-inducing alternatives where clinically feasible. Pemigatinib is a moderate CYP3A4 inhibitor and may increase plasma concentrations of sensitive CYP3A4 substrates with narrow therapeutic indices (e.g., cyclosporine, tacrolimus, midazolam, certain anticoagulants) monitor for substrate-related toxicities and adjust co-medication doses as clinically indicated. Disclose all medications, herbal products, and supplements to the treating oncologist before initiating LuciPem. |
| Hepatotoxicity and Liver Function Monitoring | Hepatotoxicity elevations of ALT, AST, alkaline phosphatase (ALP), and total bilirubin has been reported in patients receiving LuciPem (Pemigatinib). Pemigatinib’s high FGFR4 selectivity (IC50 approximately 30 nM vs <1.2 nM for FGFR1-3) relative to pan-FGFR1-4 inhibitors is associated with a more favorable hepatic safety profile by minimizing FGFR4-mediated bile acid homeostasis disruption and hepatocellular injury; however, hepatic monitoring remains essential in cholangiocarcinoma patients who carry elevated baseline hepatic risk from biliary obstruction, portal hypertension, and hepatic parenchymal tumor involvement. Monitor hepatic function (ALT, AST, total bilirubin, ALP, GGT) at baseline and at the start of each 21-day LuciPem treatment cycle; more frequent monitoring (every 2 weeks during Cycle 1) is warranted in patients with pre-existing hepatic dysfunction, concurrent biliary stent or surgical bypass, or co-administration of hepatotoxic medications. For Grade 3+ AST/ALT elevation: withhold LuciPem until resolution to ≤Grade 1, then resume at a reduced dose level. For signs of drug-induced liver injury meeting Hy’s Law criteria (ALT or AST ≥3× ULN with total bilirubin ≥2× ULN in the absence of cholestasis or an alternative explanation): permanently discontinue LuciPem and refer for hepatology consultation. |
| Pregnancy and Contraception | Pemigatinib (LuciPem) can cause fetal harm when administered to a pregnant person. FGFR signaling plays critical roles in embryonic limb, skeletal, craniofacial, and organ development; FGFR inhibition during pregnancy carries teratogenic risk supported by preclinical reproductive toxicology data across multiple FGFR inhibitor classes. Verify pregnancy status by serum or urine pregnancy test before initiating LuciPem in patients of reproductive potential. Advise patients of reproductive potential to use effective contraception during LuciPem treatment and for a clinically appropriate interval after the last dose; consult the prescribing oncologist for contraceptive recommendations given pemigatinib’s potential interactions with hormonal contraceptive metabolism. Male patients with female partners of reproductive potential should use effective barrier contraception during LuciPem treatment and after the last dose. Whether pemigatinib or its metabolites are present in human breast milk is unknown; given the potential for serious adverse reactions in nursing infants, advise patients not to breastfeed during LuciPem treatment and for an appropriate interval after the last dose. Consult the treating oncologist and obstetrician before initiating LuciPem in any patient of reproductive potential or who is breastfeeding. |
Who Should Use LuciPem 4.5 MG (Pemigatinib)?
LuciPem 4.5 MG (Pemigatinib) is indicated for adults with previously treated, unresectable, locally advanced or metastatic cholangiocarcinoma harboring FGFR2 gene fusions or other rearrangements, as confirmed by an approved companion diagnostic test. FGFR2 gene fusions occur in approximately 10–16% of intrahepatic cholangiocarcinoma cases the most common targetable oncogenic driver in iCCA and are highly enriched in younger patients, those without alcohol-related liver disease risk factors, and those with well-differentiated iCCA histology. The FIGHT-302 Phase 3 data additionally supports pemigatinib’s role in the first-line treatment of FGFR2-altered cholangiocarcinoma, where it demonstrated superior PFS (9.1 vs 5.4 months; HR 0.56) and ORR (34.9% vs 12.5%) compared to gemcitabine plus cisplatin making pemigatinib the most clinically validated FGFR inhibitor across both first-line and second-line settings in FGFR2 fusion-positive biliary tract cancer.
Adults with previously treated FGFR2 fusion-positive cholangiocarcinoma who have received at least one prior systemic therapy most commonly gemcitabine plus cisplatin as the standard first-line regimen represent the validated LuciPem target population established in the FIGHT-202 pivotal trial. In FIGHT-202, pemigatinib delivered a confirmed ORR of 35.5% the highest confirmed ORR among reversible FGFR inhibitors in a Phase 2 pivotal trial in the same indication with a median OS of 17.5 months, compared to historical second-line chemotherapy response rates of 5–10% and median OS of 7–10 months in unselected biliary tract cancer.
Adults with treatment-naive FGFR2 fusion-positive cholangiocarcinoma being evaluated for first-line targeted therapy represent an emerging primary treatment population for pemigatinib, supported by Phase 3 FIGHT-302 data demonstrating superior PFS and ORR versus gemcitabine/cisplatin the largest randomized first-line cholangiocarcinoma dataset available for any FGFR inhibitor. Adults with FGFR2 fusion-positive cholangiocarcinoma who have pre-existing hepatic dysfunction or biliary compromise represent a specific population for whom pemigatinib’s high FGFR4 selectivity (minimizing hepatic FGFR4-mediated bile acid dysregulation) and absence of a fasting requirement provide particular clinical advantages compared to FGFR inhibitors requiring strict fasting administration.
Patients who are NOT appropriate for LuciPem include: those whose cholangiocarcinoma does not harbor a confirmed FGFR2 gene fusion or rearrangement; those with uncontrolled Grade 3+ hyperphosphatemia at baseline refractory to dietary and pharmacologic management; those requiring mandatory co-administration of strong CYP3A4 inducers that cannot be substituted; pregnant patients; and those with severe hepatic impairment (Child-Pugh C). Oncology centers and procurement programs sourcing LuciPem for their patient population can explore the complete bile duct cancer medicines portfolio and the full Lucius Pharmaceuticals medicines collection at Mediaid Pharmacy before requesting a consolidated supply quotation.
Global Supplier: Mediaid Pharmacy Worldwide Shipping for LuciPem 4.5 MG (Pemigatinib)
Mediaid Pharmacy is a Dhaka-based specialty oncology medicines supplier with worldwide shipping capability, serving patients, hepatobiliary oncology centers, gastrointestinal cancer programs, hospitals, NGO treatment programs, and international healthcare providers across all regions. LuciPem 4.5 MG (Pemigatinib), manufactured by Lucius Pharmaceuticals (Lao) Co., Ltd. in Laos, is supplied as 4.5 mg oral tablets in 14-tablet bottles or boxes with each 21-day treatment cycle at the standard 13.5 mg dose requiring 42 tablets (3 × 14-tablet bottles), at the 9 mg first reduction requiring 28 tablets (2 × 14-tablet bottles), and at the 4.5 mg second reduction requiring 14 tablets (1 × 14-tablet bottle) with pricing quotations, stock availability confirmation, full product documentation, certificate of analysis, and end-to-end international delivery tracking for every order.
Individual patients with FGFR2 fusion-positive cholangiocarcinoma, hepatobiliary oncologists and gastrointestinal cancer specialists managing FGFR2-altered iCCA caseloads, hospital formulary and pharmacy departments managing pemigatinib access programs, NGO oncology program procurement coordinators, and international distributors can contact Mediaid Pharmacy through WhatsApp, phone, or WeChat for all inquiries regarding LuciPem 4.5 MG stock availability, current pricing, and international delivery timelines to specific destination countries. Procurement teams co-sourcing LuciPem with other oncology medicines or the full range of Lucius Pharmaceuticals medicines can browse both portfolios at Mediaid Pharmacy before requesting a combined quotation.
Why Choose LuciPem 4.5 MG (Pemigatinib) from Mediaid Pharmacy?
LuciPem 4.5 MG (Pemigatinib) gives hepatobiliary oncologists, gastrointestinal cancer specialists, and FGFR2 fusion-positive cholangiocarcinoma patients access to the most potent, selective, and extensively clinically validated reversible FGFR1-3 inhibitor for bile duct cancer an agent whose subnanomolar FGFR1-3 potency, greater than 70-fold FGFR4 selectivity, flexible food-independent administration, and robust dual-line Phase 2 and Phase 3 clinical validation establish it as the most comprehensively documented reversible FGFR inhibitor in biliary tract cancer manufactured by Lucius Pharmaceuticals (Lao) Co., Ltd. in Laos and available globally through Mediaid Pharmacy. The four clinical attributes that most distinguish LuciPem (Pemigatinib) from all other FGFR-targeted treatment options in FGFR2 fusion-positive biliary tract cancer are: its exceptional FGFR1-3 potency and FGFR4 selectivity, its Phase 2 (FIGHT-202) and Phase 3 (FIGHT-302) dual-trial validated clinical efficacy, its food-independent oral tablet administration, and its structured 14/7-day intermittent dosing cycle enabling systematic hyperphosphatemia management.
Exceptional FGFR1-3 potency and FGFR4 selectivity represent the defining pharmacological attributes of pemigatinib (LuciPem). IC50 values of 0.4 nM (FGFR1), 0.5 nM (FGFR2), and 1.2 nM (FGFR3) establish pemigatinib as the most potent approved reversible FGFR1-3 inhibitor, enabling near-complete FGFR kinase saturation at achievable clinical plasma concentrations; the corresponding IC50 of approximately 30 nM against FGFR4 more than 70-fold less potent preserves hepatic FGF19-FGFR4 bile acid homeostasis, minimizes FGFR4-mediated hepatotoxicity risk, and is particularly advantageous in cholangiocarcinoma patients who already carry elevated hepatic vulnerability from biliary obstruction and tumor hepatic involvement.
Dual Phase 2 and Phase 3 clinical validation FIGHT-202 ORR 35.5% (95% CI: 26.5–45.4%), DCR 82.2%, median OS 17.5 months in previously treated FGFR2 fusion+ cholangiocarcinoma; and FIGHT-302 median PFS 9.1 vs 5.4 months (HR 0.56, 95% CI: 0.41–0.77), ORR 34.9% vs 12.5% versus gemcitabine/cisplatin in first-line FGFR2-altered cholangiocarcinoma makes pemigatinib the only FGFR inhibitor with a Phase 3 randomized controlled trial dataset in biliary tract cancer, and the most extensively clinically validated FGFR inhibitor in cholangiocarcinoma across both treatment lines.
Food-independent oral tablet administration at 13.5 mg once daily (3 × LuciPem 4.5 mg tablets) for 14 days of each 21-day cycle eliminates the fasting compliance requirement that limits patient adherence and introduces therapeutic drug exposure variability with other FGFR inhibitors, simplifying daily treatment logistics for cholangiocarcinoma patients who often have impaired appetite, GI symptoms, and variable meal timing from biliary disease. Structured 14-day on/7-day off 21-day cycle directly addresses the primary class-effect limitation of FGFR inhibitors hyperphosphatemia by building pharmacodynamic phosphate normalization intervals into the treatment schedule, enabling sustained multi-cycle treatment with systematic phosphate management.
Lucius Pharmaceuticals (Lao) Co., Ltd. manufactures LuciPem in Laos at the same clinically validated 4.5 mg oral tablet strength as the Pemazyre originator formulation, and LuciPem is available through Mediaid Pharmacy with full product documentation, specialist supply coordination, and worldwide shipping. To source additional Lucius Pharmaceuticals oncology medicines or review the complete range of bile duct cancer treatment medicines at Mediaid Pharmacy, visit the Lucius Pharmaceuticals oncology medicines collection and contact the Mediaid Pharmacy team for a personalized quotation.
Frequently Asked Questions About LuciPem 4.5 MG (Pemigatinib)
What is LuciPem 4.5 MG (Pemigatinib) used for?
LuciPem 4.5 MG (Pemigatinib) is a highly selective, potent, reversible ATP-competitive pan-FGFR1-3 inhibitor tablet indicated for the treatment of adults with previously treated, unresectable, locally advanced or metastatic cholangiocarcinoma harboring FGFR2 gene fusions or other rearrangements, as confirmed by an approved companion diagnostic test. Pemigatinib blocks the ATP-binding sites of FGFR1, FGFR2, and FGFR3 kinase domains with IC50 values of 0.4 nM, 0.5 nM, and 1.2 nM respectively, suppressing constitutive FGFR2 fusion-driven RAS-MAPK and PI3K-AKT-mTOR oncogenic signaling in cholangiocarcinoma cells. In the pivotal Phase 2 FIGHT-202 trial (N=107), pemigatinib achieved a confirmed ORR of 35.5% (95% CI: 26.5–45.4%), a DCR of 82.2%, and a median OS of 17.5 months in previously treated FGFR2 fusion/rearrangement-positive cholangiocarcinoma. In the Phase 3 FIGHT-302 trial, pemigatinib significantly improved PFS to 9.1 months versus 5.4 months with gemcitabine/cisplatin (HR 0.56) in first-line FGFR2-altered cholangiocarcinoma. The recommended dose is 13.5 mg (3 × LuciPem 4.5 mg tablets) orally once daily for 14 consecutive days of a 21-day cycle. LuciPem is manufactured by Lucius Pharmaceuticals (Lao) Co., Ltd. in Laos and is available through Mediaid Pharmacy with worldwide shipping to patients, oncology centers, hospitals, and healthcare providers globally.
What is the generic name of LuciPem?
The generic name of LuciPem is Pemigatinib (International Nonproprietary Name, INN). LuciPem is the brand name registered by Lucius Pharmaceuticals (Lao) Co., Ltd. for the Pemigatinib 4.5 mg tablet manufactured in Laos, supplied as 14 tablets per bottle or box. The originator reference brand is Pemazyre (Pemigatinib tablets, Incyte Corporation), approved by the U.S. FDA on April 17, 2020, as the first selective FGFR inhibitor for previously treated FGFR2 fusion/rearrangement-positive cholangiocarcinoma. LuciPem contains Pemigatinib INN at the same clinically validated 4.5 mg oral tablet strength as the Pemazyre originator formulation. For the complete range of Lucius Pharmaceuticals medicines available at Mediaid Pharmacy, explore the Lucius Pharmaceuticals product collection.
What is the recommended dose of LuciPem 4.5 MG (Pemigatinib)?
The recommended dose of LuciPem (Pemigatinib) is 13.5 mg orally once daily taken as 3 × LuciPem 4.5 mg tablets simultaneously for 14 consecutive days of a 21-day treatment cycle, followed by a mandatory 7-day off period, at approximately the same time each day, with or without food. LuciPem is one of the only FGFR inhibitors that does not require fasting administration, as pemigatinib bioavailability is not significantly altered by food. At the standard 13.5 mg dose (3 tablets per day for 14 consecutive days), each 21-day treatment cycle requires 42 tablets (3 × 14-tablet bottles). Dose reductions: 9 mg once daily (2 × LuciPem 4.5 mg tablets) for first reduction; 4.5 mg once daily (1 × LuciPem 4.5 mg tablet) for second reduction; permanently discontinue if 4.5 mg is not tolerated. Always confirm the complete Pemigatinib dosing and management schedule with the treating oncologist before initiating LuciPem. For the full range of bile duct cancer medicines at Mediaid Pharmacy, explore the complete biliary tract cancer medicines collection.
What are the side effects of LuciPem 4.5 MG (Pemigatinib)?
The most common adverse reactions with Pemigatinib (LuciPem) from the FIGHT-202 trial include: hyperphosphatemia (approximately 67–70%; the most frequent, caused by FGFR1 inhibition of FGF23-mediated renal phosphate excretion; managed with low-phosphate diet, phosphate binders, and the 7-day off period), diarrhea (approximately 47%), alopecia (approximately 43%), fatigue (approximately 37%), constipation and decreased appetite (approximately 35%), nausea (approximately 34%), stomatitis (approximately 28%), dry eye (approximately 26%), dry mouth (approximately 24%), nail toxicity (approximately 16%), and palmar-plantar erythrodysesthesia (PPE; approximately 13%). The two most clinically significant safety concerns requiring active proactive monitoring are: (1) Hyperphosphatemia (Grade 3 in approximately 30%) managed with the 7-day cycle off period, low-phosphate diet, and phosphate binder optimization; (2) Retinal Pigment Epithelial Detachment (RPED) requiring ophthalmologic assessment (OCT) at baseline, monthly for 3 months, then every 3 months. For the full range of oncology medicines available at Mediaid Pharmacy, explore the complete oncology medicines collection.
What is FGFR2 gene fusion and why is it required for LuciPem (Pemigatinib) eligibility?
FGFR2 (fibroblast growth factor receptor 2) gene fusions are somatic chromosomal rearrangements that fuse the FGFR2 kinase domain-encoding sequence to a partner gene (most commonly BICC1; over 100 distinct partners identified), producing a constitutively active FGFR2 fusion oncoprotein that drives continuous, ligand-independent FGFR2 kinase activity and downstream RAS-MAPK and PI3K-AKT-mTOR oncogenic signaling in cholangiocarcinoma cells. FGFR2 fusions occur in approximately 10–16% of intrahepatic cholangiocarcinoma cases and are the most common targetable oncogenic alteration in this cancer type. FGFR2 gene fusion testing by an approved companion diagnostic on archival or fresh tumor tissue is mandatory before initiating LuciPem. Pemigatinib is not indicated for FGFR2 amplification or non-rearrangement point mutations without a confirmed fusion; only FGFR2 gene fusions and rearrangements qualify a patient for LuciPem therapy. For FGFR2 fusion-positive cholangiocarcinoma treatment options, explore bile duct cancer medicines available at Mediaid Pharmacy.
What drugs interact with LuciPem 4.5 MG (Pemigatinib)?
Pemigatinib (LuciPem) is primarily metabolized by CYP3A4, making CYP3A4 modulators the most important drug interaction category. Strong CYP3A4 inhibitors (itraconazole, voriconazole, posaconazole, clarithromycin, ritonavir, grapefruit products) may substantially increase pemigatinib plasma exposure by 2-fold or more reduce the LuciPem dose by approximately 50% when co-administration is unavoidable and monitor for increased adverse reactions. Strong CYP3A4 inducers (rifampin, carbamazepine, phenytoin, enzalutamide, St. John’s Wort) may reduce pemigatinib plasma concentrations by 80% or more avoid co-administration. Pemigatinib is a moderate CYP3A4 inhibitor and may increase concentrations of sensitive CYP3A4 substrates with narrow therapeutic indices. Unlike other FGFR inhibitors, LuciPem (Pemigatinib) does not have a significant food interaction and may be taken with or without food. Disclose all medications, supplements, and herbal products to the treating oncologist before initiating LuciPem. For additional Lucius Pharmaceuticals oncology products, visit the Lucius Pharmaceuticals medicines collection.
Can I order LuciPem 4.5 MG (Pemigatinib) online with worldwide shipping?
Yes. Mediaid Pharmacy supplies LuciPem 4.5 MG (Pemigatinib) by Lucius Pharmaceuticals (Lao) Co., Ltd. to patients, hepatobiliary oncology centers, gastrointestinal cancer programs, hospitals, NGO treatment programs, and healthcare providers globally. Contact Mediaid Pharmacy via WhatsApp, phone, or WeChat at +8801773428128, or email info@mediaidpharmacy.com for pricing, current stock availability, and international delivery details for your country.
Order LuciPem 4.5 MG (Pemigatinib) with Worldwide Shipping
Phone / WhatsApp / WeChat: +8801773428128 | Email: info@mediaidpharmacy.com




Reviews
There are no reviews yet.