
Description
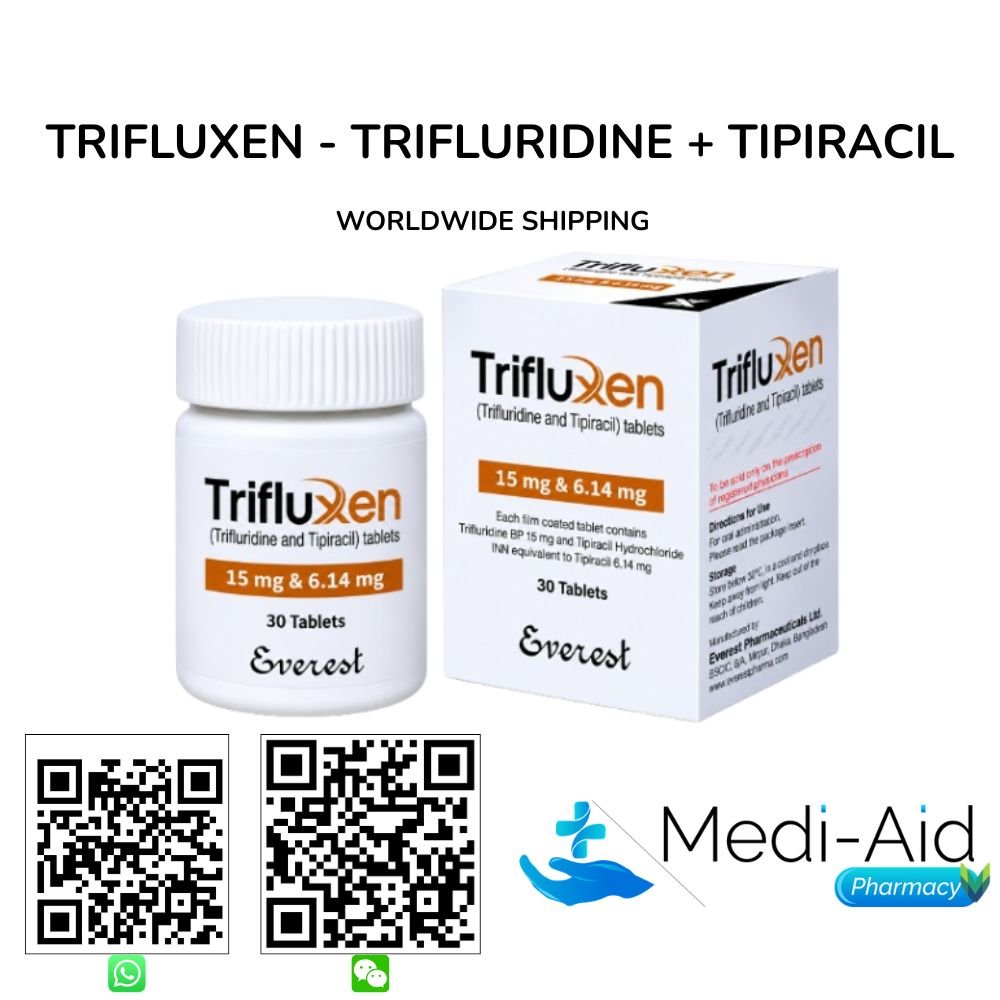
Trifluxen 15 MG/6.14 MG (Trifluridine + Tipiracil) is an oral, fixed-ratio cytotoxic combination of trifluridine (a thymidine-based nucleoside analog antineoplastic) and tipiracil (a thymidine phosphorylase [TP] inhibitor), co-formulated in a 1:0.5 molar ratio (15 mg trifluridine per 6.14 mg tipiracil per tablet) where trifluridine exerts its anti-tumor activity by being phosphorylated intracellularly to its active triphosphate form (F3dTTP), which is incorporated directly into tumor cell DNA in place of thymidine, causing DNA strand misincorporation, DNA function disruption, cell cycle arrest at the S-phase, and irreversible inhibition of thymidylate synthase (TS), thereby triggering cancer cell apoptosis; and where tipiracil prevents the rapid degradation of trifluridine by thymidine phosphorylase the enzyme responsible for trifluridine catabolism by competitively inhibiting TP, thereby maintaining therapeutically active plasma concentrations of trifluridine that would be unachievable with trifluridine administered alone due to its rapid first-pass and systemic enzymatic breakdown, supplied as a film-coated tablet in a strength of 15 mg trifluridine / 6.14 mg tipiracil, 30 tablets per pot, and manufactured by Everest Pharmaceuticals Ltd., Bangladesh.
Trifluridine/tipiracil (also designated TAS-102), the active dual-component pharmaceutical combination of Trifluxen, is indicated for adult patients with metastatic colorectal cancer (mCRC) previously treated with fluoropyrimidine-, oxaliplatin-, and irinotecan-based chemotherapy, an anti-VEGF biological therapy, and anti-EGFR therapy (if RAS wild-type) establishing trifluridine/tipiracil as the second FDA-approved oral agent for refractory mCRC (after regorafenib) and the first nucleoside-based oral cytotoxic to demonstrate a randomized survival benefit in heavily pretreated colorectal cancer and for adult patients with metastatic gastric or gastroesophageal junction (GEJ) adenocarcinoma previously treated with at least two prior regimens including, as applicable, fluoropyrimidine, platinum, anti-HER2 therapy (if HER2-positive), and taxane or irinotecan.
The recommended dose of Trifluxen (Trifluridine/Tipiracil) is 35 mg/m² (based on the trifluridine component, calculated per body surface area [BSA] and rounded to the nearest 5-mg increment) orally twice daily with food on days 1–5 and days 8–12 of each 28-day cycle, with a maximum single dose of 80 mg (based on trifluridine); dose reductions for adverse reactions are made to 25 mg/m² (first reduction) and then 20 mg/m² (second reduction), with permanent discontinuation if the patient cannot tolerate 20 mg/m²; for patients with severe renal impairment (creatinine clearance [CLcr] 15–29 mL/min), the starting dose is reduced to 20 mg/m².
The pivotal Phase III RECOURSE trial (NCT01607957; n=800) evaluated trifluridine/tipiracil 35 mg/m² twice daily versus placebo in patients with refractory mCRC, achieving a statistically significant improvement in overall survival (OS) of 7.1 months versus 5.3 months (HR 0.68; 95% CI, 0.58–0.81; p<0.0001), a median progression-free survival (PFS) of 2.0 months versus 1.7 months (HR 0.48; 95% CI, 0.41–0.57; p<0.0001), and a disease control rate (DCR) of 44.0% versus 16.3% (p<0.0001), representing the first randomized survival benefit demonstrated by a nucleoside-based oral cytotoxic in the refractory mCRC setting. The Phase III SUNLIGHT trial (NCT04737187; n=492) subsequently confirmed a statistically significant OS improvement of 10.8 months versus 7.5 months (HR 0.61; 95% CI, 0.49–0.77; p<0.001) for trifluridine/tipiracil plus bevacizumab versus trifluridine/tipiracil alone, with a PFS of 5.6 versus 2.4 months (HR 0.44; p<0.001) establishing the trifluridine/tipiracil + bevacizumab combination as the new standard of care for refractory mCRC and providing the first Phase III OS benefit demonstrated against an active comparator in the refractory mCRC setting.
Important: The most clinically significant adverse reactions of trifluridine/tipiracil are severe myelosuppression including neutropenia, anemia, and thrombocytopenia which are the primary dose-limiting toxicities and the foundation of the safety monitoring framework. Grade 3 or higher neutropenia occurred in approximately 38% of patients in RECOURSE; febrile neutropenia occurred in approximately 4%; Grade 3 or higher anemia occurred in approximately 18%. Obtain complete blood counts (CBC with differential) before initiating each treatment cycle and as clinically indicated; withhold trifluridine/tipiracil for Grade 4 neutropenia, Grade 3 neutropenia with infection or fever, or Grade 3 thrombocytopenia; do not initiate a new cycle until the absolute neutrophil count (ANC) is ≥1,500/mm³, platelet count is ≥75,000/mm³, and hemoglobin is ≥9.0 g/dL; granulocyte-colony stimulating factor (G-CSF) may be used to manage neutropenia according to institutional and guideline protocols.
Based on its mechanism of action and nonclinical data, trifluridine/tipiracil can cause embryo-fetal harm do not use in pregnancy; females of reproductive potential must use effective contraception during treatment and for 6 months after the last dose; males with female partners of reproductive potential must use condoms during treatment and for 3 months after the last dose. Do not substitute Trifluxen for other oral anti-cancer agents (regorafenib, capecitabine, fluorouracil) without confirmed indication-specific prescribing and clinical benefit-risk assessment by the treating oncologist.
Searching for Trifluxen 15 MG/6.14 MG Trifluridine + Tipiracil? Mediaid Pharmacy lists this product across its oncology medicines, colorectal cancer medicines, gastric cancer medicines, and Everest Pharmaceuticals medicines portfolios and ships it worldwide.
Basic Product Information of Trifluxen 15 MG/6.14 MG (Trifluridine + Tipiracil)
| Brand Name | Trifluxen 15 MG/6.14 MG (Trifluridine + Tipiracil) manufactured by Everest Pharmaceuticals Ltd., Bangladesh; Trifluxen is the proprietary brand name owned by Everest Pharmaceuticals Ltd. for its trifluridine/tipiracil film-coated tablet formulation; the original innovator molecule trifluridine/tipiracil is marketed globally as Lonsurf by Taiho Pharmaceutical Co., Ltd. (Japan) and Taiho Oncology, Inc. (USA); Trifluxen is the branded generic formulation of trifluridine/tipiracil manufactured by Everest Pharmaceuticals Ltd. in Bangladesh for the domestic and international oncology market and is supplied by Mediaid Pharmacy with worldwide shipping |
| Product Name | Trifluxen (trifluridine BP 15 mg + tipiracil INN 6.14 mg film-coated tablet, 30 tablets per pot, by Everest Pharmaceuticals Ltd., Bangladesh) |
| Generic Name | Trifluridine + Tipiracil (INN; trifluridine/tipiracil fixed-ratio combination tablet, also designated TAS-102; trifluridine [FTD] is a thymidine-based nucleoside analog that is transported into tumor cells, phosphorylated by thymidine kinase to its active monophosphate form [F3dTMP] and further to its active triphosphate form [F3dTTP], which is incorporated into tumor cell DNA in place of thymidine, causing DNA strand misincorporation, persistent DNA strand breaks, inhibition of thymidylate synthase [TS], and ultimately S-phase arrest and cancer cell apoptosis; because trifluridine’s cytotoxic mechanism is DNA incorporation rather than TS inhibition alone, trifluridine retains activity in fluoropyrimidine-resistant tumors where resistance is mediated through TS amplification or upregulation this mechanistic distinction from 5-fluorouracil [5-FU] and capecitabine is the basis for trifluridine/tipiracil’s clinical activity in fluoropyrimidine-refractory mCRC; tipiracil [TPI] is a thymidine phosphorylase [TP] inhibitor that suppresses the TP-mediated catabolism of trifluridine to its inactive metabolite trifluorothymine [FTY], increasing trifluridine systemic bioavailability approximately 37-fold compared to trifluridine administered alone; the fixed 1:0.5 molar ratio of trifluridine to tipiracil in each Trifluxen tablet (15 mg:6.14 mg) is specifically optimized to maintain therapeutically effective plasma trifluridine concentrations throughout the twice-daily dosing schedule; the original trifluridine/tipiracil combination was developed by Taiho Pharmaceutical Co., Ltd., Japan; FDA initial approval for mCRC: September 22, 2015; FDA approval for metastatic gastric/GEJ adenocarcinoma: February 22, 2019; FDA approval for trifluridine/tipiracil + bevacizumab combination in mCRC: January 2024) |
| Drug Class | Oral Cytotoxic Combination (Nucleoside Metabolic Inhibitor + Thymidine Phosphorylase Inhibitor); Thymidine-Based Nucleoside Analog Antineoplastic (Trifluridine Component); Thymidine Phosphorylase Inhibitor / Pharmacokinetic Booster (Tipiracil Component); DNA-Incorporating Cytotoxic Agent; Thymidylate Synthase (TS) Inhibitor (Secondary Mechanism); Oral Later-Line Cytotoxic for Refractory mCRC; Oral Later-Line Cytotoxic for Refractory Metastatic Gastric / GEJ Cancer; Fluoropyrimidine-Resistant Colorectal Cancer Cytotoxic; Body Surface Area–Based Oral Anti-Cancer Combination Tablet |
| Formulation | Film-coated tablet for oral administration take 35 mg/m² (based on the trifluridine component, calculated per BSA and rounded to the nearest 5-mg increment, up to a maximum single dose of 80 mg) orally twice daily with food (within 1 hour after completion of morning and evening meals) on days 1–5 and days 8–12 of each 28-day cycle; swallow tablets whole do not crush, split, or chew; if a dose is missed, do not take a missed dose at all skip the missed dose entirely and resume the next scheduled dose at the next planned dosing time; in the event of vomiting after a dose, do not take an additional dose on the same day resume the next dose at the scheduled time; trifluridine/tipiracil is not a significant inhibitor or inducer of major CYP450 enzymes (CYP1A2, 2C8, 2C9, 2C19, 2D6, 3A4/5) and is not a clinically significant substrate of these pathways drug-drug interactions via CYP450 mechanisms are not a primary clinical concern for trifluridine/tipiracil; avoid coadministration with other myelosuppressive agents (concurrent myelosuppressive chemotherapy, radiation, or bone marrow-suppressive immunosuppressants) due to additive hematologic toxicity risk; trifluridine/tipiracil does not require dose adjustment for mild or moderate renal impairment (CLcr ≥30 mL/min); for severe renal impairment (CLcr 15–29 mL/min), reduce starting dose to 20 mg/m²; trifluridine/tipiracil has not been studied in patients with end-stage renal disease (CLcr <15 mL/min) on dialysis; no dose adjustment is required for mild hepatic impairment (total bilirubin ≤ULN and AST >ULN, or total bilirubin 1–1.5× ULN); trifluridine/tipiracil has not been studied in patients with moderate or severe hepatic impairment and is not recommended in these populations; store Trifluxen tablets at room temperature, 25°C (77°F), excursions permitted to 15°C–30°C (59°F–86°F); store in original sealed pot; keep away from moisture and direct sunlight; keep out of reach of children; handle as a cytotoxic agent in accordance with applicable institutional safety guidelines |
| Available Strengths | 15 mg trifluridine / 6.14 mg tipiracil per film-coated tablet Trifluxen is available in this 15 mg/6.14 mg strength; the companion strength (20 mg/8.19 mg) is also available in the branded innovator product (Lonsurf); the actual prescribed dose per administration is BSA-based (35 mg/m² of trifluridine rounded to the nearest 5-mg increment) and uses a combination of 15 mg and 20 mg tablets to achieve the target dose; the 15 mg/6.14 mg tablet size is used for patients requiring BSA-based dose calculations in the lower range, or as part of multi-tablet dose combinations; dose reductions for toxicity are permitted at two levels: first dose reduction to 25 mg/m² of trifluridine; second dose reduction to 20 mg/m² of trifluridine; permanently discontinue trifluridine/tipiracil if the patient cannot tolerate the 20 mg/m² dose level; no dose adjustment is required based on age or sex; trifluridine/tipiracil has not been studied in pediatric patients |
| Available Pack Size | 30 tablets per pot the number of Trifluxen 15 mg/6.14 mg tablets required per treatment cycle varies by patient BSA and by which strength tablet is used; at the recommended 35 mg/m² twice daily dose on days 1–5 and 8–12 (20 dosing occasions per 28-day cycle), a patient requiring 15 mg tablets per dose would consume 60 tablets per 28-day cycle (3 × 15 mg = 45 mg per dose, twice daily) depending on their BSA-adjusted target dose; institutional oncology departments, outpatient oncology clinics, and hospital pharmacies typically procure Trifluxen on a per-patient per-cycle basis calculated from the BSA-based dose and the number of 15 mg/6.14 mg tablets needed per dosing occasion across the 20 dosing days per cycle; for patients in the RECOURSE trial, median treatment duration was approximately 2.0–2.1 months (range: <1 month to 23+ months) with continued dosing in patients achieving disease control until progression or unacceptable toxicity |
| Dosing Schedule | Metastatic Colorectal Cancer (mCRC) after prior fluoropyrimidine-, oxaliplatin-, and irinotecan-based chemotherapy; anti-VEGF biological therapy; and anti-EGFR therapy (if RAS wild-type): Trifluridine/tipiracil 35 mg/m² (trifluridine component, BSA-based, rounded to the nearest 5-mg increment, maximum 80 mg per dose) orally twice daily with food on days 1–5 and 8–12 of each 28-day cycle; continue until disease progression or unacceptable toxicity; no biomarker companion diagnostic is required trifluridine/tipiracil efficacy in mCRC is independent of RAS, BRAF, MSI, or HER2 mutation status; trifluridine/tipiracil is also approved in combination with bevacizumab (5 mg/kg IV every 2 weeks, on the same day as trifluridine/tipiracil on days 1 and 15 of the cycle) in this setting based on the SUNLIGHT Phase III trial.
Metastatic Gastric or Gastroesophageal Junction (GEJ) Adenocarcinoma after prior fluoropyrimidine, platinum, anti-HER2 (if HER2-positive), and taxane or irinotecan: Trifluridine/tipiracil 35 mg/m² (maximum 80 mg per dose) orally twice daily with food on days 1–5 and 8–12 of each 28-day cycle; continue until disease progression or unacceptable toxicity; at least 2 prior regimens for metastatic disease are required; no biomarker companion diagnostic is required. Dose Reduction Schedule for Adverse Reactions: First dose reduction: 25 mg/m² (rounded to nearest 5-mg increment) twice daily on days 1–5 and 8–12 of each 28-day cycle; Second dose reduction: 20 mg/m² twice daily on the same schedule; Permanently discontinue trifluridine/tipiracil if the patient cannot tolerate the 20 mg/m² dose level. Mandatory Pre-Treatment Assessment: Measure BSA for dose calculation; obtain baseline CBC with differential (ANC, platelet count, hemoglobin); assess renal function (serum creatinine/CLcr); assess hepatic function (ALT, AST, total bilirubin); conduct pregnancy test in females of reproductive potential; confirm prior treatment history meeting the required pre-treatment criteria for each indication. On-Treatment CBC Monitoring: Obtain CBC with differential before initiating each new treatment cycle; obtain CBC during the cycle as clinically indicated (especially on day 8 of each cycle, to anticipate nadir timing); do not begin a new cycle until ANC ≥1,500/mm³, platelet count ≥75,000/mm³, and hemoglobin ≥9.0 g/dL; withhold trifluridine/tipiracil for Grade 4 neutropenia or Grade 3 neutropenia with infection or fever; consider G-CSF support per institutional protocols for recurrent Grade 3–4 neutropenia. |
| Primary Indications | METASTATIC COLORECTAL CANCER (mCRC) REFRACTORY SETTING (AFTER PRIOR STANDARD THERAPIES):
Trifluridine/Tipiracil Monotherapy Refractory mCRC (RECOURSE; Phase III; NCT01607957; n=800; 2:1 randomization; trifluridine/tipiracil 35 mg/m² twice daily days 1–5 and 8–12 vs. placebo + BSC; primary endpoint OS): Statistically significant OS improvement: median OS 7.1 months versus 5.3 months (HR 0.68; 95% CI, 0.58–0.81; p<0.0001); median PFS 2.0 versus 1.7 months (HR 0.48; 95% CI, 0.41–0.57; p<0.0001); DCR 44.0% versus 16.3% (p<0.0001); ORR 1.6% versus 0.4%; FDA accelerated approval September 22, 2015. The RECOURSE population consisted of 800 patients across North America, Japan, Europe, and Australia who had received at least two prior chemotherapy regimens for mCRC 93% had disease refractory to fluoropyrimidine-based therapy, confirming trifluridine’s clinical activity in a population with established fluoropyrimidine resistance. The RECOURSE data established trifluridine/tipiracil as the second FDA-approved oral agent for refractory mCRC, providing a chemotherapy-class treatment option with a distinct nucleoside analog mechanism for a heavily pretreated patient population that has exhausted all prior targeted and cytotoxic options. Trifluridine/Tipiracil + Bevacizumab Combination Refractory mCRC (SUNLIGHT; Phase III; NCT04737187; n=492; 1:1 randomization; trifluridine/tipiracil + bevacizumab vs. trifluridine/tipiracil alone; primary endpoint OS): Statistically significant OS improvement: median OS 10.8 months versus 7.5 months (HR 0.61; 95% CI, 0.49–0.77; p<0.001); median PFS 5.6 versus 2.4 months (HR 0.44; 95% CI, 0.36–0.54; p<0.001); DCR 64.0% versus 42.5%; OS benefit observed across all clinically relevant subgroups including prior bevacizumab (72% of patients in both arms); FDA approval for trifluridine/tipiracil + bevacizumab combination: January 2024. SUNLIGHT is the first Phase III trial in the refractory mCRC setting to demonstrate an OS benefit versus an active comparator (versus trifluridine/tipiracil monotherapy, rather than placebo + BSC), establishing trifluridine/tipiracil + bevacizumab as the new standard-of-care third-line regimen for refractory mCRC. METASTATIC GASTRIC OR GASTROESOPHAGEAL JUNCTION (GEJ) ADENOCARCINOMA AFTER ≥2 PRIOR REGIMENS: Trifluridine/Tipiracil Monotherapy Metastatic Gastric / GEJ Adenocarcinoma (TAGS; Phase III; NCT02500043; n=507; 2:1 randomization; trifluridine/tipiracil vs. placebo + BSC; primary endpoint OS): Statistically significant OS improvement: median OS 5.7 months versus 3.6 months (HR 0.69; 95% CI, 0.56–0.85; p=0.00029); median PFS 2.0 versus 1.8 months (HR 0.57; p<0.001); FDA approval for gastric/GEJ adenocarcinoma: February 22, 2019. The TAGS population consisted of 507 patients who had received at least two prior regimens for metastatic gastric or GEJ cancer representing one of the first oral agents to demonstrate a randomized survival benefit in heavily pretreated metastatic gastric cancer, a patient population with extremely limited treatment options at the third-line and beyond. |
| Manufacturer | Everest Pharmaceuticals Ltd. Bangladesh |
| Country of Origin | Bangladesh (Everest Pharmaceuticals Ltd., Dhaka, Bangladesh) |
| Storage | Store at room temperature, 25°C (77°F); excursions permitted to 15°C–30°C (59°F–86°F); store in original sealed pot; keep away from moisture and direct sunlight; keep out of reach of children; handle as a cytotoxic anti-cancer agent in accordance with applicable institutional handling and disposal guidelines; standard ambient-temperature shipping is acceptable for Trifluxen (Trifluridine + Tipiracil) film-coated tablets cold-chain shipping is not required; Mediaid Pharmacy ships Trifluxen internationally using validated ambient-temperature packaging methods appropriate for destination country transit times and regional climate conditions |
Global Supplier: Mediaid Pharmacy Worldwide Shipping for Trifluxen 15 MG/6.14 MG (Trifluridine + Tipiracil)
Mediaid Pharmacy is a Dhaka-based supplier of specialty oral cytotoxic oncology therapies, nucleoside analog anti-cancer agents, colorectal cancer medicines, gastric cancer medicines, and later-line oral oncology agents with worldwide shipping to patients, oncology departments, outpatient infusion units, colorectal cancer and gastric cancer treatment programs, hospital pharmacies, oncology day units, patient access programs, and international distributors across all regions. Trifluxen 15 MG/6.14 MG (Trifluridine + Tipiracil), manufactured by Everest Pharmaceuticals Ltd., Bangladesh, is supplied as film-coated tablets (15 mg trifluridine / 6.14 mg tipiracil per tablet, 30 tablets per pot), with pricing quotations, stock confirmation, full product documentation, and end-to-end international delivery tracking for every order.
Trifluxen (Trifluridine/Tipiracil) is an orally administered, ambient-temperature-stable tablet formulation international shipping does not require cold-chain handling, enabling reliable worldwide supply to patients in diverse geographies. Refractory mCRC treatment programs procuring trifluridine/tipiracil as later-line oral cytotoxic therapy; gastric cancer programs sourcing trifluridine/tipiracil for previously treated metastatic gastric or GEJ adenocarcinoma; hospital formulary procurement departments sourcing Trifluxen as part of targeted and cytotoxic oncology medicines portfolios; and individual patients and families sourcing trifluridine tipiracil for refractory colorectal cancer treatment can contact the Mediaid Pharmacy team through WhatsApp, phone, or email for Trifluxen 15 MG/6.14 MG stock availability, current pricing, shipping options, and international delivery timelines.
Why Choose Trifluxen 15 MG/6.14 MG (Trifluridine + Tipiracil) from Mediaid Pharmacy?
Trifluxen (Trifluridine + Tipiracil) from Everest Pharmaceuticals Ltd. delivers a clinically validated oral cytotoxic mechanism the dual nucleoside analog/thymidine phosphorylase inhibitor combination that enables oral DNA-incorporating cytotoxic therapy with proven Phase III survival benefits in both refractory mCRC and refractory metastatic gastric cancer supplied as a convenient film-coated tablet (15 mg/6.14 mg, 30 tablets per pot) with a structured BSA-based twice-daily dosing regimen on days 1–5 and 8–12 of each 28-day cycle, enabling outpatient oral cytotoxic administration without IV infusion requirements, cold-chain logistics, or institutional infusion suite access for the oral component. Trifluridine/tipiracil is pharmacologically and clinically distinguished across the later-line oncology landscape by four evidence-based attributes.
First, trifluridine’s DNA incorporation mechanism not TS inhibition alone provides cytotoxic activity that is mechanistically distinct from fluoropyrimidines, enabling anti-tumor efficacy in fluoropyrimidine-refractory colorectal cancer. Fluoropyrimidine resistance in mCRC is frequently mediated by thymidylate synthase (TS) amplification, upregulation of TS protein expression following 5-FU exposure, or reduced thymidine kinase activity mechanisms that render 5-FU and capecitabine ineffective but do not block trifluridine’s primary cytotoxic mechanism of DNA strand incorporation; because trifluridine’s triphosphate form (F3dTTP) is incorporated directly into DNA causing persistent strand breaks and miscoding events that neither TS amplification nor TS overexpression can reverse trifluridine retains cytotoxic potency in tumors that have become clinically refractory to all fluoropyrimidine-based regimens; this mechanistic differentiation is clinically validated by the RECOURSE trial’s enrollment of a population in which 93% had fluoropyrimidine-refractory disease and in whom trifluridine/tipiracil still achieved a statistically significant OS benefit (HR 0.68; p<0.0001), confirming that fluoropyrimidine refractoriness does not predict trifluridine/tipiracil resistance.
Second, the tipiracil pharmacokinetic booster component is a pharmacologically essential co-ingredient not a passive excipient whose TP inhibition is what makes oral trifluridine therapy clinically feasible. Without tipiracil, orally administered trifluridine undergoes rapid degradation by thymidine phosphorylase (TP) in the intestinal wall and liver during first-pass metabolism, reducing plasma trifluridine bioavailability to sub-therapeutic levels; the co-administration of tipiracil in the fixed 1:0.5 molar ratio suppresses this rapid TP-mediated catabolism, increasing trifluridine systemic AUC approximately 37-fold relative to trifluridine monotherapy at the same dose; this 37-fold bioavailability amplification is what transforms trifluridine from an orally inactive compound into a clinically effective oral DNA-incorporating cytotoxic agent; the fixed-ratio tablet formulation of Trifluxen (15 mg trifluridine / 6.14 mg tipiracil) ensures that every dose delivers the precisely calibrated trifluridine-to-tipiracil molar ratio required for optimal trifluridine bioavailability, regardless of patient weight or absorption variability.
Third, the SUNLIGHT Phase III trial established trifluridine/tipiracil + bevacizumab as the new standard of care for refractory mCRC the first Phase III trial in this setting to demonstrate an OS benefit versus an active control transforming the clinical significance of trifluridine/tipiracil-based therapy. The SUNLIGHT study (n=492) demonstrated median OS of 10.8 versus 7.5 months (HR 0.61; p<0.001) for the trifluridine/tipiracil + bevacizumab combination versus trifluridine/tipiracil alone, with PFS improvement of 5.6 versus 2.4 months (HR 0.44; p<0.001) and DCR improvement of 64.0% versus 42.5%; crucially, all subgroups benefited, including patients who had already received prior bevacizumab (72% of participants in both arms); the SUNLIGHT combination represents the first later-line mCRC regimen to demonstrate efficacy as a continuation of antiangiogenic therapy after prior bevacizumab exposure; this positions trifluridine/tipiracil (Trifluxen) as the oral backbone of the new standard-of-care third-line mCRC regimen a clinical upgrade from monotherapy to a proven combination with a bevacizumab partner that is widely accessible globally.
Fourth, trifluridine/tipiracil’s minimal drug interaction profile and oral, twice-daily structured dosing provide practical treatment administration advantages critical for patients in diverse healthcare and geographic settings. Unlike targeted kinase inhibitors with complex CYP450-based interaction profiles (e.g., regorafenib’s CYP3A4/UGT1A1 interactions, requiring avoidance of rifampin, ketoconazole, and warfarin co-use precautions), trifluridine/tipiracil does not interact with or inhibit CYP1A2, 2C8, 2C9, 2C19, 2D6, or 3A4/5 at clinically relevant concentrations simplifying comedication management in patients with the complex polypharmacy typical of heavily pretreated oncology populations; fixed twice-daily BSA-based dosing on 10 of every 28 days provides structured treatment windows with built-in recovery periods that allow hematologic recovery between dosing intervals (days 6–7 and days 13–28 of each cycle), reducing cumulative myelosuppression risk relative to continuous daily cytotoxic dosing schedules; room-temperature storage and ambient-temperature shipping enable reliable international supply, supporting access for patients globally.
To source Trifluxen 15 MG/6.14 MG (Trifluridine + Tipiracil), colorectal cancer oral cytotoxic medicines, gastric cancer medicines, and the complete Everest Pharmaceuticals oncology portfolio, visit the Mediaid Pharmacy colorectal cancer medicines portfolio, the gastric cancer medicines collection, the oncology medicines collection, and the Everest Pharmaceuticals medicines range, and contact the team for a personalized quotation and international shipping confirmation.
Frequently Asked Questions About Trifluxen 15 MG/6.14 MG (Trifluridine + Tipiracil)
What is Trifluxen 15 MG/6.14 MG (Trifluridine + Tipiracil) used for?
Trifluxen 15 MG/6.14 MG (Trifluridine + Tipiracil) is an oral cytotoxic combination agent with approved oncology indications in two distinct solid tumor types defined by specific prior treatment histories. (1) Metastatic Colorectal Cancer (mCRC) Refractory Setting: Trifluridine/tipiracil 35 mg/m² twice daily on days 1–5 and 8–12 of each 28-day cycle is indicated for adult patients with mCRC previously treated with fluoropyrimidine-, oxaliplatin-, and irinotecan-based chemotherapy; anti-VEGF biological therapy; and anti-EGFR therapy (if RAS wild-type); in the RECOURSE Phase III trial (n=800), trifluridine/tipiracil achieved a statistically significant OS improvement of 7.1 versus 5.3 months (HR 0.68; p<0.0001) and a DCR of 44.0% versus 16.3% versus placebo + BSC; trifluridine/tipiracil efficacy in mCRC is independent of RAS, BRAF, and MSI status no companion diagnostic is required; trifluridine/tipiracil is also approved in combination with bevacizumab in this setting, as demonstrated by the SUNLIGHT Phase III trial (OS 10.8 vs. 7.5 months; HR 0.61; p<0.001), establishing the combination as the new standard-of-care third-line mCRC regimen. (2) Metastatic Gastric or Gastroesophageal Junction (GEJ) Adenocarcinoma After ≥2 Prior Regimens: Trifluridine/tipiracil 35 mg/m² twice daily on the same schedule is indicated for adult patients with metastatic gastric or GEJ adenocarcinoma previously treated with at least two prior regimens; in the TAGS Phase III trial (n=507), trifluridine/tipiracil improved median OS from 3.6 months to 5.7 months (HR 0.69; p=0.00029) versus placebo + BSC. Trifluxen 15 MG/6.14 MG (Trifluridine + Tipiracil) is available through Mediaid Pharmacy with worldwide shipping to patients and refractory colorectal cancer treatment programs globally.
What is the generic name of Trifluxen?
The generic names of Trifluxen are trifluridine (BP; also known as FTD or α,α,α-trifluorothymidine) and tipiracil (INN; also known as TPI or tipiracil hydrochloride). Trifluridine is a thymidine-based nucleoside analog antineoplastic that is incorporated into tumor cell DNA as the active triphosphate form (F3dTTP), causing DNA strand misincorporation, DNA function disruption, cell cycle arrest at the S-phase, and thymidylate synthase inhibition triggering cancer cell apoptosis; trifluridine’s DNA incorporation mechanism confers cytotoxic activity that is mechanistically distinct from 5-fluorouracil (5-FU) and capecitabine (which inhibit TS primarily through the 5-FU metabolite FdUMP), enabling trifluridine’s clinical activity in fluoropyrimidine-refractory tumors. Tipiracil is a thymidine phosphorylase (TP) inhibitor that prevents the rapid enzymatic degradation of trifluridine to its inactive metabolite trifluorothymine (FTY), maintaining plasma trifluridine at therapeutically active concentrations approximately 37-fold higher than those achievable with trifluridine administered alone. The fixed-ratio combination trifluridine/tipiracil (also designated TAS-102) was originally developed by Taiho Pharmaceutical Co., Ltd., Japan, and is marketed globally as Lonsurf; Trifluxen is the branded generic formulation manufactured by Everest Pharmaceuticals Ltd. in Bangladesh. Trifluxen is mechanistically distinct from anti-VEGF biologics (bevacizumab, ramucirumab), EGFR inhibitors (cetuximab, panitumumab), multikinase inhibitors (regorafenib), KRAS inhibitors (sotorasib), and immune checkpoint inhibitors (pembrolizumab, nivolumab) all of which target different oncogenic pathways rather than tumor cell DNA directly. Mediaid Pharmacy distributes Trifluxen 15 MG/6.14 MG Trifluridine Tipiracil globally with worldwide shipping to patients, oncology programs, and hospital pharmacies.
What are the side effects of Trifluxen (Trifluridine + Tipiracil)?
The most clinically significant adverse reactions of Trifluxen (Trifluridine + Tipiracil) are severe myelosuppression including neutropenia, anemia, and thrombocytopenia which are the primary dose-limiting toxicities and the foundation of the safety monitoring and dose modification framework for trifluridine/tipiracil therapy. Neutropenia: The most critical and frequent Grade 3–4 toxicity Grade 3 or higher neutropenia occurred in approximately 38% of patients in RECOURSE; febrile neutropenia occurred in approximately 3.8%; monitor CBC with differential before each treatment cycle and as clinically indicated; withhold trifluridine/tipiracil for Grade 4 neutropenia (ANC <500/mm³) or Grade 3 neutropenia with concurrent infection or fever; do not initiate a new cycle until ANC ≥1,500/mm³; G-CSF may be used per institutional protocols for recurrent Grade 3–4 neutropenia. Anemia: Grade 3 or higher anemia occurred in approximately 18% of RECOURSE patients; monitor hemoglobin before each cycle; hold trifluridine/tipiracil until hemoglobin ≥9.0 g/dL; transfusion support may be required for severe anemia. Thrombocytopenia: Grade 3 or higher thrombocytopenia in approximately 5%; withhold trifluridine/tipiracil for Grade 3 thrombocytopenia (platelet count <50,000/mm³); do not initiate a new cycle until platelet count ≥75,000/mm³. Most Common (≥20%) Adverse Reactions (RECOURSE): Nausea (48%), neutropenia (38%), anemia (32%), asthenia/fatigue (35%), decreased appetite (39%), vomiting (28%), diarrhea (32%), pyrexia (21%), thrombocytopenia (21%), constipation (14%). Additional Notable Adverse Reactions: Alopecia (less common than with IV chemotherapy), peripheral neuropathy (uncommon, less prominent than with oxaliplatin), and elevated alkaline phosphatase. Trifluridine/tipiracil does not carry a Boxed Warning and is not associated with significant hepatotoxicity, QTc prolongation, hand-foot skin reaction (HFSR), or hypertension distinguishing its tolerability profile from that of regorafenib (which carries Boxed Warning hepatotoxicity risk and characteristic HFSR). All patients initiating Trifluxen (Trifluridine + Tipiracil) should have baseline CBC with differential, renal and hepatic function, and ECOG performance status documented, with treatment initiated under the supervision of a qualified oncologist experienced in managing oral cytotoxic therapy toxicities.
How effective is Trifluxen (Trifluridine + Tipiracil) for refractory colorectal cancer?
Trifluridine/tipiracil demonstrated statistically significant survival benefit in refractory metastatic colorectal cancer (mCRC) in the global Phase III RECOURSE trial, and further demonstrated a substantial additional survival benefit in combination with bevacizumab in the Phase III SUNLIGHT trial establishing trifluridine/tipiracil-based regimens as the standard-of-care later-line oral cytotoxic backbone for refractory mCRC. RECOURSE Phase III (NCT01607957; n=800; trifluridine/tipiracil vs. placebo + BSC; primary endpoint OS): Statistically significant OS improvement: 7.1 months versus 5.3 months (HR 0.68; 95% CI, 0.58–0.81; p<0.0001); median PFS 2.0 versus 1.7 months (HR 0.48; p<0.0001); DCR 44.0% versus 16.3% the RECOURSE population was heavily pretreated (93% with fluoropyrimidine-refractory disease; median of 3 prior treatment lines) and enrolled patients across North America, Japan, Europe, and Australia, confirming trifluridine/tipiracil’s global clinical activity in refractory mCRC; the OS benefit was consistent across all major subgroups including KRAS wild-type and mutant patients, BRAF-mutant patients, and patients who had received prior regorafenib. SUNLIGHT Phase III (NCT04737187; n=492; trifluridine/tipiracil + bevacizumab vs. trifluridine/tipiracil alone; primary endpoint OS): Statistically significant OS improvement: 10.8 months versus 7.5 months (HR 0.61; 95% CI, 0.49–0.77; p<0.001); median PFS 5.6 versus 2.4 months (HR 0.44; p<0.001); DCR 64.0% versus 42.5%; OS benefit confirmed across all subgroups including patients with prior bevacizumab exposure (72% of both arms); SUNLIGHT is the first Phase III refractory mCRC trial to demonstrate OS superiority versus an active control arm (versus trifluridine/tipiracil monotherapy), establishing the absolute OS benefit of adding bevacizumab at 3.3 additional months of median survival a clinically meaningful benefit in a refractory mCRC population with no alternative approved options. Biomarker Independence: Trifluridine/tipiracil demonstrated OS benefit in both RECOURSE and SUNLIGHT regardless of RAS (KRAS/NRAS), BRAF, MSI, or HER2 status no negative predictive biomarker has been validated for trifluridine/tipiracil in mCRC. Trifluxen 15 MG/6.14 MG (Trifluridine + Tipiracil) is available through Mediaid Pharmacy; visit the colorectal cancer medicines collection and oncology medicines collection for the complete later-line colorectal cancer portfolio.
What is the difference between Trifluxen (Trifluridine + Tipiracil) and Stivarga (Regorafenib) for refractory mCRC?
Trifluxen (Trifluridine + Tipiracil) and Stivarga (Regorafenib) are the two FDA-approved oral agents for refractory mCRC, but they differ fundamentally in pharmacological class, mechanism of action, clinical trial design, tolerability profile, and combination approvals making them complementary options with distinct patient selection and sequencing considerations. Mechanism Cytotoxic vs. Kinase Inhibitor: Trifluridine/tipiracil is an oral cytotoxic (nucleoside analog + TP inhibitor) its anti-tumor activity is mediated by DNA strand incorporation of trifluridine, causing irreversible DNA damage in actively dividing tumor cells regardless of tumor mutation profile; regorafenib is an oral multikinase inhibitor its activity is mediated by simultaneous blockade of VEGFR1/2/3, TIE2, PDGFR, KIT, RET, and RAF, targeting tumor angiogenesis and oncogenic signaling; these are fundamentally different pharmacological approaches to anti-tumor activity. Clinical Trial Comparators: Both RECOURSE (trifluridine/tipiracil) and CORRECT (regorafenib) used placebo + BSC as the comparator neither drug has been directly compared head-to-head in a randomized Phase III trial in the refractory mCRC setting; indirect comparison suggests broadly similar OS benefits (HR 0.68 for trifluridine/tipiracil vs. HR 0.77 for regorafenib in their respective placebo-controlled trials). Combination Approval: Trifluridine/tipiracil has an FDA-approved combination with bevacizumab (SUNLIGHT; OS 10.8 vs. 7.5 months; HR 0.61) this combination is now the standard-of-care third-line mCRC regimen; regorafenib does not have an approved combination partner for mCRC. Tolerability Key Differences: Trifluridine/tipiracil’s primary toxicities are myelosuppression (neutropenia Grade 3+ ~38%, anemia ~18%), with minimal risk of hepatotoxicity, hand-foot skin reaction (HFSR), or hypertension; regorafenib’s primary toxicities include hepatotoxicity (Boxed Warning), hand-foot skin reaction (Grade 3 ~17%), and hypertension with rare but serious hemorrhagic risk; patients with baseline hepatic compromise, risk of HFSR, or hypertension may tolerate trifluridine/tipiracil better than regorafenib; patients with significant baseline cytopenias, impaired bone marrow reserve, or infection risk may be more challenging candidates for trifluridine/tipiracil. Sequencing: Both agents can be used sequentially in either order in refractory mCRC; clinical guidelines and patient-specific tolerability factors guide sequencing decisions. For trifluridine/tipiracil availability, visit the Mediaid Pharmacy colorectal cancer medicines range and Everest Pharmaceuticals medicines collection.
Is Trifluxen (Trifluridine + Tipiracil) safe during pregnancy or while breastfeeding?
Trifluxen (Trifluridine + Tipiracil) can cause embryo-fetal harm and must not be used during pregnancy. Based on its mechanism of action trifluridine incorporates directly into DNA during active cell replication, which is an essential process for embryonic and fetal development trifluridine/tipiracil is expected to cause embryo-fetal lethality, teratogenicity, and fetal growth impairment at clinically relevant exposures; nonclinical studies confirmed that trifluridine/tipiracil caused embryo-fetal lethality in rats and teratogenicity in rabbits at exposures below the recommended clinical dose; fetal malformations in nonclinical studies included cardiovascular, skeletal, and other developmental anomalies consistent with the mechanism of DNA-incorporating cytotoxic agents. Contraception requirement: Females of reproductive potential must use effective non-hormonal or hormonal contraception during trifluridine/tipiracil treatment and for 6 months after the last dose; males with female partners of reproductive potential must use condoms during treatment and for 3 months after the last dose, as trifluridine/tipiracil genotoxicity represents a risk of mutagenic DNA damage to sperm during the active treatment period; verify pregnancy status with a serum or urine pregnancy test before initiating Trifluxen in all females of reproductive potential. Breastfeeding: No data are available on the presence of trifluridine, tipiracil, or their metabolites in human breast milk, their effects on breastfed infants, or effects on milk production; because of the potential for serious adverse reactions in a breastfed infant from a DNA-incorporating cytotoxic agent, breastfeeding is not recommended during trifluridine/tipiracil treatment and for 1 day (24 hours) after the last dose. Fertility: Based on the genotoxic mechanism of trifluridine, potential adverse effects on male and female fertility cannot be excluded; discuss fertility preservation options with the treating oncologist before initiating trifluridine/tipiracil therapy in patients of reproductive potential. All aspects of reproductive planning and contraceptive requirements should be discussed with the treating oncologist before initiating Trifluxen therapy.
Can I order Trifluxen 15 MG/6.14 MG (Trifluridine + Tipiracil) online with worldwide shipping?
Yes. Mediaid Pharmacy supplies Trifluxen 15 MG/6.14 MG (Trifluridine + Tipiracil), film-coated tablets, 30 tablets per pot, manufactured by Everest Pharmaceuticals Ltd., Bangladesh, to patients, colorectal cancer and gastric cancer oncology departments, oral cytotoxic cancer treatment programs, hospital pharmacies, oncology outpatient clinics, patient access programs, and healthcare providers globally. Trifluxen (Trifluridine + Tipiracil) is an oral tablet formulation with room-temperature stability international shipping is conducted using validated ambient-temperature packaging methods without cold-chain handling requirements, enabling reliable, cost-effective worldwide delivery across diverse geographies and climate conditions. Contact Mediaid Pharmacy via WhatsApp, phone, or email at +8801773428128, or email info@mediaidpharmacy.com for pricing, current stock availability, international shipping options, and delivery details for your country. Prescription documentation and applicable regulatory import/export requirements must be met for trifluridine/tipiracil dispensing in accordance with country-specific regulations governing oral anti-cancer agents; as a cytotoxic agent, Trifluxen must be handled and dispensed in accordance with applicable institutional and national cytotoxic handling guidelines. For the complete portfolio of Everest Pharmaceuticals oncology medicines available with worldwide shipping, visit the Mediaid Pharmacy Everest Pharmaceuticals medicines page.
Order Trifluxen 15 MG/6.14 MG (Trifluridine + Tipiracil) with Worldwide Shipping
Phone / WhatsApp: +8801773428128 | Email: info@mediaidpharmacy.com



Reviews
There are no reviews yet.