
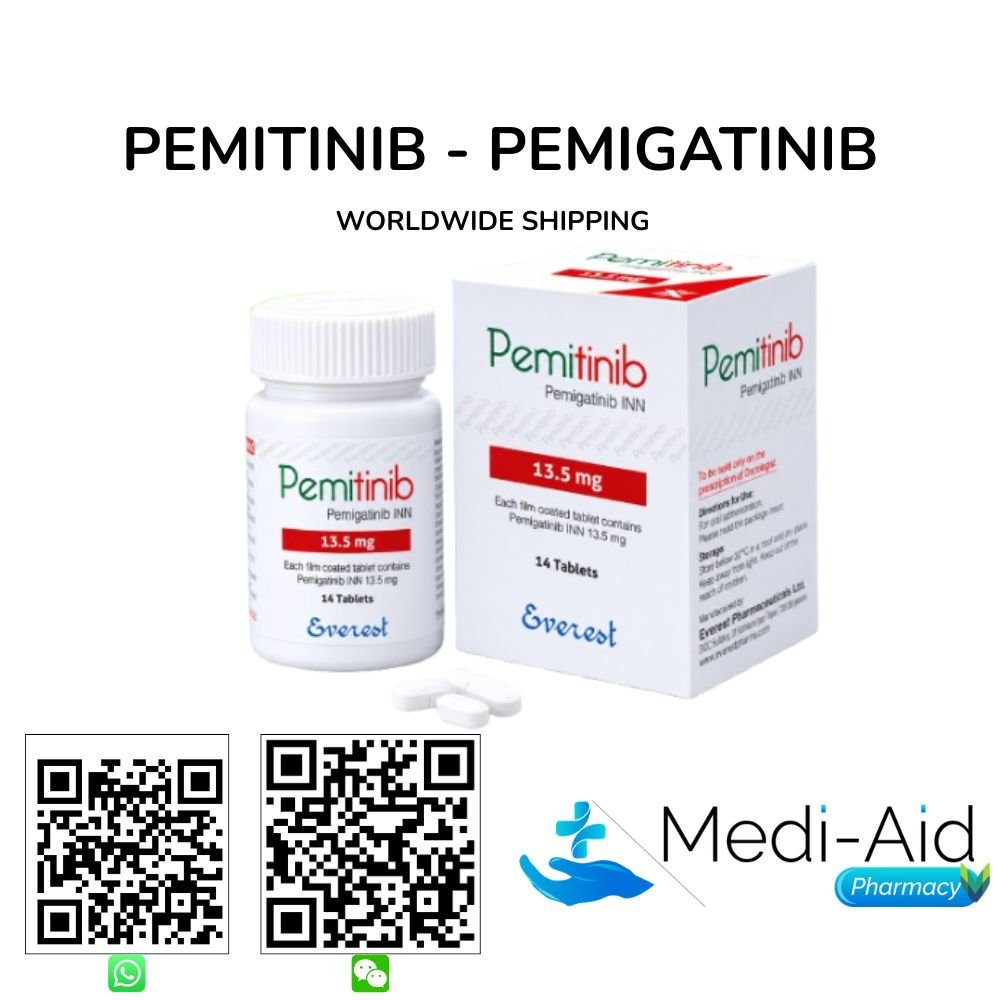
Description
Pemitinib 13.5 MG (Pemigatinib) is an orally administered first-in-class selective fibroblast growth factor receptor (FGFR) inhibitor and targeted oncology agent a potent, small-molecule kinase inhibitor of FGFR1, FGFR2, and FGFR3 that suppresses constitutively activated FGFR-driven oncogenic signalling in tumours harbouring FGFR2 gene fusions or rearrangements and in haematological malignancies harbouring FGFR1 rearrangements, blocking downstream RAS-MAPK, PI3K-AKT, and STAT3 pathway activation that drives aberrant cancer cell proliferation, survival, and tumour angiogenesis in FGFR-altered malignancies supplied as film-coated tablets in 13.5 mg strength in a 14-tablet pot and manufactured by Everest Pharmaceuticals Ltd. in Bangladesh.
Its active pharmaceutical ingredient, pemigatinib INN, is indicated as monotherapy for two biomarker-selected oncological indications: previously treated unresectable locally advanced or metastatic cholangiocarcinoma (bile duct cancer) with an FGFR2 fusion or other rearrangement, and relapsed or refractory myeloid/lymphoid neoplasms (MLNs) with FGFR1 rearrangement. Pemitinib 13.5 MG film-coated tablets are administered following the standard pemigatinib 13.5 mg once-daily dosing schedule for cholangiocarcinoma, 13.5 mg orally once daily for 14 consecutive days followed by 7 days off therapy in 21-day cycles; for MLNs, 13.5 mg orally once daily continuously with each 14-tablet pot supplying exactly one complete 14-day active treatment phase per cholangiocarcinoma cycle.
The FDA accelerated approval of pemigatinib for previously treated FGFR2-rearranged cholangiocarcinoma (April 17, 2020) was supported by FIGHT-202, a multicentre, open-label, single-arm Phase 2 study enrolling 107 adults with locally advanced or metastatic cholangiocarcinoma with documented FGFR2 gene fusion or rearrangement; in the pivotal efficacy analysis by independent review, pemigatinib monotherapy achieved an overall response rate (ORR) of 35.5% (38/107) including 3 complete responses and 35 partial responses a disease control rate of 82%, and a median duration of response of 9.1 months, with a median progression-free survival of 6.9 months and an updated median overall survival of 17.5 months.
For relapsed or refractory MLNs with FGFR1 rearrangement, the Phase 2 FIGHT-203 study (N=28) demonstrated a complete response rate of 78% (95% CI: 52%–94%) in patients with chronic-phase marrow disease and a complete cytogenetic response rate of 79% (95% CI: 59%–92%) across the overall population, with a median duration of complete response that was not reached outcomes that supported the FDA approval of pemigatinib for this rare and aggressive haematological malignancy on August 26, 2022.
Important: Pemigatinib carries well-characterised class-related risks of retinal pigment epithelial detachment (RPED) occurring in 11% of patients receiving the 13.5 mg starting dose with a median onset of 56 days and hyperphosphatemia (laboratory incidence 94%), requiring mandatory baseline and periodic ophthalmological assessment and serum phosphate monitoring before and throughout all Pemitinib treatment cycles. Searching for Pemitinib 13.5 MG Pemigatinib? Mediaid Pharmacy lists this product across its oncology medicines, bile duct cancer medicines, and Everest Pharmaceuticals portfolios and ships it worldwide.
Basic Product Information of Pemitinib 13.5 MG (Pemigatinib)
| Brand Name | Pemitinib 13.5 MG (Pemigatinib) |
| Product Name | Pemitinib |
| Generic Name | Pemigatinib INN |
| Drug Class | Targeted Oncology Agent; Selective Fibroblast Growth Factor Receptor (FGFR) Inhibitor (FGFR1 / FGFR2 / FGFR3 Inhibitor); First-in-Class FGFR-Targeted Kinase Inhibitor for Cholangiocarcinoma; Anti-Angiogenic and Anti-Proliferative Agent; Receptor Tyrosine Kinase Inhibitor (RTKI); Antineoplastic Agent |
| Formulation | Film-Coated Tablet (Oral) |
| Available Strengths | 13.5 mg per film-coated tablet |
| Available Pack Size | 14 Tablets per pot (one complete 14-day active treatment phase per 21-day cholangiocarcinoma cycle) |
| Dosing Schedule | Cholangiocarcinoma (FGFR2 fusion or rearrangement): Pemigatinib 13.5 mg orally once daily for 14 consecutive days, followed by 7 days off therapy, in repeating 21-day cycles (intermittent schedule). Administer with or without food. Continue until disease progression or unacceptable toxicity.
Myeloid/Lymphoid Neoplasms with FGFR1 Rearrangement (R/R MLNs): Pemigatinib 13.5 mg orally once daily continuously (without the 7-day rest period), until disease progression, unacceptable toxicity, or until the patient proceeds to allogeneic haematopoietic stem cell transplantation (allo-HSCT). Consult the treating oncologist or haematologist for dose modification guidance in the event of adverse reactions, drug interactions, or disease status changes. |
| Primary Indications | (1) Previously Treated FGFR2-Rearranged Cholangiocarcinoma (Bile Duct Cancer): Monotherapy in adults with previously treated, unresectable, locally advanced or metastatic cholangiocarcinoma with a fibroblast growth factor receptor 2 (FGFR2) fusion or other rearrangement as detected by an FDA-approved test. FDA accelerated approval granted April 17, 2020; pemigatinib is the first and only targeted FGFR inhibitor approved for cholangiocarcinoma. Patient selection requires FGFR2 rearrangement confirmed by FoundationOne CDx or equivalent approved companion diagnostic.
(2) Relapsed or Refractory Myeloid/Lymphoid Neoplasms (MLNs) with FGFR1 Rearrangement: Monotherapy in adults with relapsed or refractory MLNs harbouring an FGFR1 rearrangement who are not candidates for, or have relapsed after, allogeneic HSCT or disease-modifying therapy. FDA approval granted August 26, 2022, based on FIGHT-203; pemigatinib is the first and only targeted treatment approved for FGFR1-rearranged MLNs. |
| Manufacturer | Everest Pharmaceuticals Ltd., Bangladesh |
| Country of Origin | Bangladesh |
| Originator Reference Brand | Pemazyre® (pemigatinib tablets 4.5 mg, 9 mg, and 13.5 mg, developed and marketed by Incyte Corporation the first and only FDA-approved FGFR kinase inhibitor for cholangiocarcinoma; received accelerated approval on April 17, 2020 for previously treated FGFR2-rearranged cholangiocarcinoma based on FIGHT-202; received full approval on August 26, 2022 for R/R MLNs with FGFR1 rearrangement based on FIGHT-203; granted priority review, breakthrough therapy designation, and orphan drug designation for the cholangiocarcinoma indication; companion diagnostic approved alongside: FoundationOne CDx by Foundation Medicine). Both Pemitinib and Pemazyre® contain pemigatinib INN as the active pharmaceutical ingredient at 13.5 mg per tablet in the same selective FGFR1/FGFR2/FGFR3 inhibitor drug class. Pemitinib is manufactured by Everest Pharmaceuticals Ltd. in Bangladesh and is supplied through Mediaid Pharmacy for international procurement. |
| Global Supplier | Mediaid Pharmacy, Worldwide Shipping Available |
| Storage Conditions | Store at room temperature (15°C to 30°C). Keep in the original packaging and protect from moisture and light. Keep out of the reach of children. |
How Pemitinib (Pemigatinib) Works: Selective FGFR1/2/3 Kinase Inhibition and Oncogenic FGFR Signalling Suppression in Cholangiocarcinoma and Myeloid/Lymphoid Neoplasms
Pemigatinib INN is an orally administered targeted oncology agent whose mechanism of action is mechanistically distinct from cytotoxic chemotherapy, antimetabolites, and all non-targeted antineoplastic drug classes: pemigatinib is a potent, selective small-molecule inhibitor of fibroblast growth factor receptor (FGFR) isoforms 1, 2, and 3 receptor tyrosine kinases (RTKs) that normally transduce fibroblast growth factor (FGF) ligand signals through the cell membrane, regulating embryonic development, tissue homeostasis, wound healing, angiogenesis, and cellular proliferation and differentiation in healthy adult tissues.
The FGFR family (FGFR1–FGFR4) functions through ligand-induced receptor dimerisation and autophosphorylation of cytoplasmic tyrosine residues, activating downstream intracellular signalling cascades principally the RAS-RAF-MEK-ERK (MAPK) mitogenic pathway, the PI3K-AKT-mTOR survival pathway, the STAT3 transcriptional pathway, and the PLC-γ pathway that collectively drive cancer cell proliferation, survival, resistance to apoptosis, tumour angiogenesis, and invasiveness when aberrantly activated.
In cholangiocarcinoma, FGFR2 gene fusions and rearrangements occurring in approximately 10–16% of intrahepatic cholangiocarcinoma cases and arising almost exclusively in this biliary tract cancer subtype create constitutively dimerised, ligand-independent, permanently activated FGFR2 fusion kinase proteins whose unregulated tyrosine kinase activity sustains oncogenic MAPK and PI3K-AKT signalling continuously, driving the malignant phenotype of FGFR2-rearranged cholangiocarcinoma cells independent of normal FGF ligand availability.
In myeloid and lymphoid neoplasms, chromosomal translocations involving the FGFR1 gene at 8p11 create FGFR1 fusion proteins with constitutively activated FGFR1 kinase domains that drive clonal expansion of malignant haematopoietic progenitor cells producing a clinically heterogeneous group of rare and aggressive blood cancers that may present as myeloproliferative neoplasms (MPNs), acute myeloid leukaemia (AML), T-cell lymphoblastic lymphoma, or mixed phenotype presentations, collectively designated myeloid/lymphoid neoplasms with FGFR1 rearrangement.
Pemigatinib inhibits constitutively activated mutant FGFR1, FGFR2, and FGFR3 by competing with ATP at the kinase active site, blocking receptor autophosphorylation and preventing downstream activation of RAS-MAPK and PI3K-AKT oncogenic signalling cascades. Pemigatinib does not substantially inhibit FGFR4 at therapeutic concentrations a pharmacological selectivity important for limiting hepatotoxicity associated with FGFR4 inhibition in normal liver tissue. Preclinical studies confirmed that pemigatinib inhibits tumour growth in mouse xenograft models of human tumours with FGFR1, FGFR2, or FGFR3 alterations leading to constitutive FGFR activation, providing direct mechanistic validation of the target engagement underlying clinical benefit.
The intermittent dosing schedule used in the cholangiocarcinoma indication 14 days on treatment followed by 7 days off, per 21-day cycle is pharmacodynamically rationalised by the role of FGFR2/3 signalling in regulating fibroblast growth factor 23 (FGF23)-mediated renal phosphate reabsorption: continuous FGFR inhibition suppresses FGF23-FGFR1c-Klotho signalling in renal tubular epithelial cells, reducing tubular phosphate excretion and driving hyperphosphatemia; the 7-day treatment holiday allows partial recovery of phosphate homeostasis and substantially reduces cumulative hyperphosphatemia severity without compromising anti-tumour efficacy. For FGFR1-rearranged MLNs, a continuous dosing schedule is used, reflecting the different disease biology of haematological FGFR1 fusion-driven malignancies and the need for sustained FGFR1 kinase suppression to prevent leukaemic blast proliferation during treatment interruptions.
The pharmacokinetic profile of pemigatinib is characterised by good oral bioavailability with a time to peak plasma concentration (Tmax) of approximately 1–2 hours following oral administration; pemigatinib may be taken with or without food, as food does not substantially alter its pharmacokinetic exposure. Pemigatinib undergoes primarily hepatic metabolism via the CYP3A4 enzyme, making it susceptible to clinically significant pharmacokinetic drug interactions with strong CYP3A4 inhibitors which increase pemigatinib area-under-the-curve (AUC) approximately 4.5-fold and strong CYP3A4 inducers which decrease pemigatinib AUC by approximately 57%, substantially reducing therapeutic exposure and potentially compromising anti-tumour efficacy.
Pemigatinib is predominantly eliminated via faeces, with minor urinary excretion; renal impairment does not require dose adjustment. No pharmacokinetic dose adjustment is required for mild or moderate hepatic impairment; data in severe hepatic impairment are limited and Pemitinib should be used with caution in Child-Pugh C patients under specialist guidance. Pemigatinib dose-reduction steps from 13.5 mg to 9 mg, and from 9 mg to 4.5 mg, are available for management of adverse reactions and drug interactions; Pemazyre® is approved in all three strengths (4.5 mg, 9 mg, and 13.5 mg), and the three-tier dose reduction scheme is reflected in the prescribing information. For the complete range of targeted oncology and bile duct cancer medicines available at Mediaid Pharmacy, visit the oncology medicines collection.
Pemitinib 13.5 MG (Pemigatinib): Indications, Dosing, and Key Safety Information
| Approved Indications | (1) Previously Treated FGFR2-Rearranged Cholangiocarcinoma: Monotherapy in adults with previously treated, unresectable locally advanced or metastatic cholangiocarcinoma with an FGFR2 fusion or other rearrangement detected by an FDA-approved companion diagnostic (FoundationOne CDx). FDA accelerated approval granted April 17, 2020. Pemigatinib is the first and only approved targeted FGFR inhibitor for cholangiocarcinoma and the first targeted treatment in this indication.
(2) R/R Myeloid/Lymphoid Neoplasms with FGFR1 Rearrangement: Monotherapy in adults with relapsed or refractory MLNs harbouring FGFR1 rearrangement who are not eligible for or have relapsed after allo-HSCT or disease-modifying therapy. FDA approval granted August 26, 2022, based on FIGHT-203. Pemigatinib is the first and only approved targeted therapy for FGFR1-rearranged MLNs. |
| Recommended Dose Cholangiocarcinoma | 13.5 mg orally once daily (one Pemitinib 13.5 MG film-coated tablet) for 14 consecutive days, followed by 7 days off therapy in 21-day repeating cycles. Administer at approximately the same time each day, with or without food. Swallow tablets whole do not crush, split, or chew. Continue until disease progression or unacceptable toxicity. Confirm FGFR2 fusion or rearrangement by an FDA-approved companion diagnostic test before initiating Pemitinib. Evaluate response per RECIST 1.1 at regular intervals during treatment. One 14-tablet pot of Pemitinib covers exactly one full 14-day active treatment phase per cycle. |
| Recommended Dose R/R MLNs (FGFR1) | 13.5 mg orally once daily (one Pemitinib 13.5 MG film-coated tablet) continuously without a treatment holiday until disease progression, unacceptable toxicity, or until the patient is able to proceed to allogeneic haematopoietic stem cell transplantation (allo-HSCT). At the continuous dose of 13.5 mg/day, one 14-tablet pot of Pemitinib provides a 14-day supply; two pots are required per 28-day supply cycle. Confirm FGFR1 rearrangement status before initiating Pemitinib for this indication. FGFR1 rearrangement testing does not currently require an FDA-approved companion diagnostic molecular confirmation by any validated laboratory method is acceptable per the prescribing information. |
| Dose Modifications | Pemigatinib dose reductions follow a three-level scheme: First reduction: from 13.5 mg to 9 mg once daily. Second reduction: from 9 mg to 4.5 mg once daily. Discontinue permanently if the patient cannot tolerate the 4.5 mg dose. Dose interruption or reduction indications include: Grade ≥2 RPED (retinal pigment epithelial detachment); Grade ≥2 hyperphosphatemia not manageable with dietary restriction and phosphate-lowering agents; Grade ≥3 non-haematological toxicity; or co-administration with a strong CYP3A4 inhibitor that cannot be substituted (reduce from 13.5 mg to 9 mg, or from 9 mg to 4.5 mg, as indicated). Resume Pemitinib at the reduced dose level after resolution of the adverse reaction to Grade ≤1 or baseline. All dose modifications require the direction of the treating oncologist or haematologist. |
| Special Populations | Hepatic Impairment: No dose adjustment is required for mild (Child-Pugh A) or moderate (Child-Pugh B) hepatic impairment. Data in severe hepatic impairment (Child-Pugh C) are limited; use Pemitinib with caution and under specialist guidance in this population. Renal Impairment: No dose adjustment is required for mild, moderate, or severe renal impairment; pemigatinib is not substantially renally excreted. Elderly Patients: No dose adjustment is required based on age alone; standard 13.5 mg once daily dosing applies for fit elderly patients. Monitor for ocular toxicity and hyperphosphatemia with particular vigilance in older patients. Paediatric Patients: Safety and efficacy of pemigatinib have not been established in patients under 18 years of age; Pemitinib is not approved for paediatric use. |
| ⚠ KEY WARNING Ocular Toxicity (RPED) | Pemigatinib (Pemitinib) can cause retinal pigment epithelial detachment (RPED) a serious ocular adverse effect requiring mandatory ophthalmological monitoring before and throughout all treatment cycles. Among 635 patients receiving a starting dose of 13.5 mg pemigatinib, 11% developed confirmed RPED, with Grade 3/4 events occurring in 1.3% of patients; the median time to RPED onset was 56 days from treatment initiation, meaning the greatest risk period falls within the first two to three cycles of Pemitinib therapy. RPED is a structural separation of the retinal pigment epithelium from the photoreceptor layer that may cause visual disturbances including blurred vision, visual field changes, or floaters, and may progress to permanent visual impairment if not managed promptly.
Monitoring requirements: Obtain a baseline comprehensive ophthalmological examination including dilated fundoscopy and optical coherence tomography (OCT) of the macula before initiating Pemitinib. Repeat ophthalmological assessment at every other cycle for the first 6 months of therapy, then every 3 months thereafter, and at any time the patient reports new or worsening visual symptoms. Patients should be advised to report changes in vision, including blurring or perception of flashing lights, immediately during Pemitinib treatment. Management: Interrupt Pemitinib for Grade 2 or higher RPED. Resume at the next lower dose level after RPED resolves to Grade ≤1. Permanently discontinue Pemitinib for Grade 3 or 4 RPED, or for any RPED that does not resolve to Grade ≤1 within the management period. Refer all patients with confirmed RPED to a retinal specialist. |
| ⚠ KEY WARNING Hyperphosphatemia | Hyperphosphatemia is an expected, on-mechanism pharmacodynamic effect of pemigatinib FGFR inhibition, occurring in up to 94% of patients as a laboratory abnormality and clinically in 60% of patients in FIGHT-202. Pemigatinib inhibits FGFR1c signalling in renal tubular epithelial cells, suppressing FGF23-mediated phosphate excretion and causing phosphate retention. While most cases are Grade 1–2 and manageable, severe hyperphosphatemia (Grade 3: serum phosphate >5.5 to ≤7.0×ULN) and Grade 4 (>7.0×ULN) can occur and require dose interruption or reduction.
Monitoring: Obtain baseline serum phosphate before initiating Pemitinib. Monitor serum phosphate at least monthly during therapy and more frequently if clinically indicated. During the 7-day treatment-free period in the cholangiocarcinoma cycle, serum phosphate typically begins to normalise monitor accordingly. Management: Initiate dietary phosphate restriction (reducing intake of phosphate-rich foods including dairy, processed meats, nuts, and cola beverages) early in treatment. For persistent or Grade ≥2 hyperphosphatemia not controlled by diet, initiate oral phosphate-lowering agents (calcium carbonate, sevelamer, or lanthanum carbonate per local practice guidelines). For Grade ≥3 hyperphosphatemia unresponsive to dietary restriction and phosphate binders, interrupt Pemitinib until resolution and resume at the next lower dose level. |
| Additional Warnings & Precautions | Biomarker Testing Requirement: Pemitinib must be used only in patients with confirmed FGFR2 fusion or rearrangement (cholangiocarcinoma) or confirmed FGFR1 rearrangement (MLNs) identified by a validated diagnostic test. Do not initiate Pemitinib before biomarker testing results confirm the relevant FGFR alteration. FoundationOne CDx is the FDA-approved companion diagnostic for FGFR2-rearranged cholangiocarcinoma.
Dry Eye and Corneal Toxicity: Dry eye (xerophthalmia) and other ocular surface reactions are common with pemigatinib (incidence in FIGHT-202: dry eye approximately 32–34%); instruct patients to use preservative-free artificial tear lubricants from treatment initiation and to avoid contact lens wear during Pemitinib therapy. Embryo-Foetal Toxicity: Based on its mechanism of action and findings from animal studies, pemigatinib is expected to cause embryo-foetal harm. Advise females of reproductive potential to use effective contraception during Pemitinib therapy and for at least 1 week after the last dose. Verify pregnancy status before initiating Pemitinib. Drug Interactions CYP3A4: Pemigatinib is primarily metabolised by CYP3A4. Strong CYP3A4 inhibitors (itraconazole, voriconazole, clarithromycin, ritonavir) increase pemigatinib AUC approximately 4.5-fold reduce Pemitinib dose to the next lower level if co-administration with a strong CYP3A4 inhibitor cannot be avoided. Strong CYP3A4 inducers (rifampicin, carbamazepine, phenytoin, enzalutamide, St John’s Wort) decrease pemigatinib AUC by approximately 57% avoid concurrent use. Review the full drug interaction profile before initiating Pemitinib in patients receiving CYP3A4-modulating agents. |
| Common Adverse Reactions | The most common adverse reactions (incidence ≥20%) in the cholangiocarcinoma FIGHT-202 trial include: hyperphosphatemia (60%), alopecia (49%), diarrhoea (47%), nail toxicity (43%), fatigue (42%), nausea (40%), dysgeusia (40%), constipation (35%), stomatitis (35%), dry mouth (34%), decreased appetite, vomiting, arthralgia, abdominal pain, dry eye, hypophosphatemia, back pain, and dry skin. The most frequently reported laboratory abnormalities include: increased phosphate (94%), decreased phosphate (68%), increased alanine aminotransferase / ALT (43%), increased aspartate aminotransferase / AST (43%), increased alkaline phosphatase (41%), and increased creatinine (41%). Nail toxicity including onycholysis (separation of the nail plate), brittle nails, and periungual inflammation is a class-related FGFR inhibitor toxicity managed with emollient creams and, in severe cases, dose modification. Alopecia with pemigatinib is typically diffuse and non-scarring; its onset is usually within the first cycle of therapy. Stomatitis management includes preventive oral hygiene, bland mouth rinses, and topical analgesics for symptomatic ulceration. |
| Drug Interactions | Pemigatinib is a CYP3A4 substrate; its plasma exposure is substantially affected by CYP3A4 inhibitors and inducers. Strong CYP3A4 inhibitors (itraconazole, voriconazole, posaconazole, ketoconazole, clarithromycin, ritonavir, grapefruit/grapefruit juice): increase pemigatinib AUC approximately 4.5-fold reduce Pemitinib dose by one level (13.5 mg → 9 mg, or 9 mg → 4.5 mg) if co-administration is unavoidable. Moderate CYP3A4 inhibitors (fluconazole, erythromycin, diltiazem, verapamil): reduce Pemitinib dose by one level if co-administration cannot be avoided. Strong or moderate CYP3A4 inducers (rifampicin, carbamazepine, phenytoin, phenobarbital, enzalutamide, St John’s Wort): decrease pemigatinib exposure avoid concurrent use; if unavoidable, close clinical monitoring for loss of Pemitinib efficacy is required. Pemigatinib does not have clinically significant direct inhibitory effects on CYP enzyme isoforms at therapeutic concentrations. Disclose all concomitant antifungals, anticonvulsants, antiretrovirals, and herbal supplements to the treating oncologist before initiating Pemitinib. |
| Pregnancy & Lactation | Based on its mechanism of action and animal reproductive toxicology data, pemigatinib is expected to cause embryo-foetal harm when administered during pregnancy. FGF-FGFR signalling plays a critical role in foetal organogenesis and limb development; inhibition of FGFR activity during pregnancy is anticipated to disrupt normal foetal development. Pemitinib should not be used during pregnancy; if pregnancy occurs during Pemitinib treatment, the patient should be informed of the potential risk to the foetus and the treating oncologist should be consulted immediately for a risk-benefit assessment. Females of reproductive potential must use effective non-hormonal contraception during Pemitinib therapy and for at least 1 week after the last dose note that pemigatinib’s CYP3A4-inducing potential may reduce the efficacy of hormonal contraceptives; barrier methods or non-hormonal IUD contraception should be used. Male patients with female partners of reproductive potential should use effective contraception during treatment and for at least 1 week after the final dose. Whether pemigatinib or its metabolites are excreted into human breast milk is unknown; breastfeeding is not recommended during Pemitinib treatment and for at least 1 week after the last dose. Discuss pregnancy intentions and contraceptive planning with the treating oncologist before and throughout Pemitinib therapy. |
Who Should Use Pemitinib 13.5 MG (Pemigatinib)?
Pemitinib (Pemigatinib) is indicated for two biomarker-defined oncological settings that share the prerequisite of confirmed FGFR pathway alteration either FGFR2 fusion or rearrangement in cholangiocarcinoma, or FGFR1 rearrangement in haematological malignancies and for both of which pemigatinib is the first and only approved targeted therapy, representing genuine unmet-need treatment advances in diseases where prior lines of therapy have failed and where the underlying oncogenic driver is a directly targetable FGFR kinase activation.
First, adults with previously treated, unresectable locally advanced or metastatic cholangiocarcinoma harbouring an FGFR2 fusion or rearrangement represent the primary Pemitinib-indicated patient population: cholangiocarcinoma a rare and aggressive malignancy of the bile duct epithelium carries one of the worst prognoses of all gastrointestinal cancers, with median survival of 12–15 months even with first-line gemcitabine-cisplatin chemotherapy, and virtually no effective standard-of-care options in the second-line setting prior to the approval of FGFR-targeted therapies. FGFR2 fusions and rearrangements define a molecular subgroup in approximately 10–16% of intrahepatic cholangiocarcinoma patients, enriched in younger patients with preserved hepatic function, and represent the most actionable single molecular alteration in this disease: the FIGHT-202 study established an ORR of 35.5% (including 3 complete responses in 107 patients), a disease control rate of 82%, and a median duration of response of 9.1 months the first clinically meaningful targeted efficacy demonstration in FGFR2-rearranged cholangiocarcinoma and the evidence base for pemigatinib’s accelerated FDA approval as the first and only FGFR inhibitor approved for any cholangiocarcinoma indication.
Second, adults with relapsed or refractory myeloid/lymphoid neoplasms (MLNs) harbouring FGFR1 rearrangement represent the haematological indication for Pemitinib: FGFR1-rearranged MLNs affect fewer than 1 in 100,000 individuals in the United States a rare and heterogeneous group of aggressive blood cancers including MPN, AML, B- or T-cell lymphoblastic lymphoma, and mixed phenotype presentations, all driven by constitutively activated FGFR1 fusion kinase proteins arising from 8p11 chromosomal translocations for whom prior standard treatments (chemotherapy and allo-HSCT-bridging strategies) offered limited and non-durable responses. The FIGHT-203 study demonstrated a CR rate of 78% in chronic-phase marrow disease and a complete cytogenetic response rate of 79% across the overall population (N=28), with a median duration of complete response that was not reached outcomes establishing pemigatinib as the first targeted kinase inhibitor approved for this molecular subgroup.
Pemitinib is not appropriate for cholangiocarcinoma without confirmed FGFR2 fusion or rearrangement; for MLNs without confirmed FGFR1 rearrangement; for patients with active severe ocular disease or pre-existing retinal disorders precluding required RPED monitoring; or for patients unable to tolerate mandatory ophthalmological surveillance. Hepatobiliary oncology centres, biliary tract cancer MDT teams, haematology units managing FGFR1-rearranged MLNs, hospital formulary and procurement teams, and oncology patient access programmes can browse the Mediaid Pharmacy bile duct cancer medicines portfolio, the full oncology medicines collection, and the Everest Pharmaceuticals medicines range for the complete selection available with international delivery.
Global Supplier: Mediaid Pharmacy Worldwide Shipping for Pemitinib 13.5 MG (Pemigatinib)
Mediaid Pharmacy is a Dhaka-based supplier of specialty targeted oncology, biliary tract cancer, and rare disease medicines with worldwide shipping to patients, hepatobiliary oncology departments, biliary tract cancer MDT programmes, FGFR-mutated cholangiocarcinoma specialist centres, haematology units managing FGFR1-rearranged MLNs, hospital pharmacies, and international distributors across all regions. Pemitinib (Pemigatinib), manufactured by Everest Pharmaceuticals Ltd. in Bangladesh, is supplied as 13.5 mg film-coated tablets in a 14-tablet pot with pricing quotations, stock confirmation, full product documentation, and end-to-end international delivery tracking for every order.
The 14-tablet pot format is clinically precise for the cholangiocarcinoma indication: at the standard pemigatinib 13.5 mg once-daily intermittent schedule, each 14-tablet pot covers exactly one complete 14-day active treatment phase of the 21-day cycle one pot per cycle for CCA patients; for patients on the continuous MLN dosing schedule at 13.5 mg/day, one 14-tablet pot covers 14 days of continuous therapy, and two pots cover one 28-day supply period, allowing oncology pharmacy teams and international procurement specialists to calculate supply requirements accurately across both indication-specific dosing schedules.
Hepatobiliary and gastrointestinal oncology centres managing patients with FGFR2-rearranged cholangiocarcinoma; haematology units treating patients with FGFR1-rearranged relapsed or refractory MLNs; hospital oncology formulary and procurement teams; oncology patient access and compassionate-use programmes; and individual patients and families accessing pemigatinib in regions where Pemazyre® is unavailable or cost-prohibitive can contact the Mediaid Pharmacy team through WhatsApp, phone, or WeChat for all enquiries regarding Pemitinib Pemigatinib stock availability, current pricing, and international delivery timelines.
Procurement teams co-sourcing Pemitinib with other targeted oncology or bile duct cancer medicines can browse the complete Mediaid Pharmacy oncology medicines collection and the Everest Pharmaceuticals medicines portfolio before requesting a consolidated quotation.
Why Choose Pemitinib 13.5 MG (Pemigatinib) from Mediaid Pharmacy?
Pemitinib (Pemigatinib) provides hepatobiliary oncologists, gastrointestinal cancer specialists, and haematologists with a first-in-class, Phase 2-validated, molecularly targeted FGFR kinase inhibitor whose selective FGFR1/FGFR2/FGFR3 inhibitor mechanism is pharmacologically distinct from every other drug class used in cholangiocarcinoma and MLN treatment including cytotoxic gemcitabine-cisplatin doublets, FOLFOX (oxaliplatin-based chemotherapy), IDH1/IDH2 inhibitors (ivosidenib, enasidenib), BRAF-MEK inhibitors, NTRK inhibitors (larotrectinib), VEGFR inhibitors (sorafenib, ramucirumab), and BCL-2 inhibitors conferring a mechanism-based precision oncology rationale specifically in patients whose tumours carry the driving FGFR2 or FGFR1 rearrangement that makes their malignancy uniquely sensitive to FGFR pathway blockade.
The clinical evidence base establishing pemigatinib’s therapeutic value is directly linked to molecular biomarker selection: the FIGHT-202 study demonstrated that restricting pemigatinib treatment to the FGFR2 fusion or rearrangement-positive subgroup (Cohort A; N=107) representing the approximately 10–16% of intrahepatic cholangiocarcinoma patients with this alteration delivers a 35.5% objective response rate (ORR) with a disease control rate of 82% and a median progression-free survival of 6.9 months, in a disease setting where second-line chemotherapy achieves ORRs of 5–8% and DCRs of approximately 40–50% representing a clinically transformative improvement in treatment outcomes for this molecularly selected subgroup.
The median overall survival of 17.5 months in the updated FIGHT-202 analysis is particularly noteworthy in second-line cholangiocarcinoma, a setting historically characterised by median OS of 6–9 months with best supportive care or salvage chemotherapy. For FGFR1-rearranged MLNs, the FIGHT-203 CR rate of 78% in chronic-phase marrow disease with a median duration of complete response that had not been reached at the time of analysis is exceptional in the context of a rare haematological malignancy for which no prior approved targeted therapy existed and where conventional chemotherapy rarely achieves sustained complete remissions.
The oral once-daily administration of pemigatinib one Pemitinib 13.5 MG tablet taken once daily offers critical practical advantages for cholangiocarcinoma patients: the intermittent 14-days-on / 7-days-off cycle eliminates the need for intravenous infusion infrastructure, reduces the frequency of clinic visits, and avoids hospitalisation associated with intravenous chemotherapy, while the 7-day treatment-free interval provides a scheduled pharmacokinetic recovery period that substantially reduces cumulative hyperphosphatemia and improves tolerability over extended treatment durations.
Pemitinib is manufactured by Everest Pharmaceuticals Ltd. in Bangladesh and is available through Mediaid Pharmacy as 13.5 mg film-coated tablets in a 14-tablet pot with full product documentation, specialist supply coordination, and worldwide shipping from Dhaka. To source additional Everest Pharmaceuticals oncology and targeted therapy medicines, visit the Mediaid Pharmacy Everest Pharmaceuticals medicines section and the oncology medicines portfolio, and contact the team for a personalised quotation.
Frequently Asked Questions About Pemitinib 13.5 MG (Pemigatinib)
What is Pemitinib 13.5 MG (Pemigatinib) used for?
Pemitinib 13.5 MG (Pemigatinib) is a selective fibroblast growth factor receptor (FGFR) inhibitor and targeted oncology agent indicated for two biomarker-selected indications: (1) as monotherapy for previously treated, unresectable locally advanced or metastatic cholangiocarcinoma (bile duct cancer) with an FGFR2 gene fusion or other rearrangement, detected by an FDA-approved companion diagnostic test pemigatinib is the first and only targeted treatment approved for this indication; and (2) as monotherapy for relapsed or refractory myeloid/lymphoid neoplasms (MLNs) with FGFR1 rearrangement in adults who are not eligible for or have relapsed after allogeneic HSCT or disease-modifying therapy pemigatinib is also the first and only approved targeted therapy for this rare haematological indication. Pemigatinib works by selectively inhibiting FGFR1, FGFR2, and FGFR3 kinase activity, blocking constitutive oncogenic signalling driven by FGFR2 fusions in cholangiocarcinoma and FGFR1 rearrangements in MLNs. The originator brand is Pemazyre® (Incyte Corporation). Pemitinib, manufactured by Everest Pharmaceuticals Ltd. in Bangladesh, is available through Mediaid Pharmacy with worldwide shipping.
What is the generic name of Pemitinib?
The generic name of Pemitinib is pemigatinib INN. Pemitinib is the brand name registered by Everest Pharmaceuticals Ltd. for pemigatinib manufactured in Bangladesh. Pemitinib is formulated as film-coated tablets in 13.5 mg strength, supplied in a 14-tablet pot designed to cover exactly one 14-day active treatment phase per 21-day cholangiocarcinoma cycle at the standard pemigatinib dose of 13.5 mg once daily. The originator reference brand is Pemazyre® (pemigatinib tablets 4.5 mg, 9 mg, and 13.5 mg, by Incyte Corporation), which received its first accelerated FDA approval on April 17, 2020 for previously treated FGFR2-rearranged cholangiocarcinoma the first approved targeted therapy for any cholangiocarcinoma indication. Mediaid Pharmacy distributes Pemitinib globally with worldwide shipping to patients, oncology clinics, hospital pharmacies, and biliary tract cancer treatment programmes.
What is the difference between Pemitinib (Pemigatinib) and Pemazyre® (Pemigatinib)?
Pemitinib and Pemazyre® both contain pemigatinib INN as the active pharmaceutical ingredient at 13.5 mg per film-coated tablet and share the same selective FGFR1/FGFR2/FGFR3 kinase inhibitor mechanism of action for the treatment of FGFR2-rearranged cholangiocarcinoma and FGFR1-rearranged MLNs. Pemazyre® is the originator brand developed and marketed by Incyte Corporation, which received FDA accelerated approval on April 17, 2020 for FGFR2-rearranged cholangiocarcinoma making pemigatinib the first targeted therapy approved for any cholangiocarcinoma indication and the first FGFR inhibitor approved for bile duct cancer and subsequently received approval for FGFR1-rearranged MLNs on August 26, 2022; Pemazyre® is also available in 4.5 mg and 9 mg tablet strengths for dose reduction purposes. Pemitinib is manufactured by Everest Pharmaceuticals Ltd. in Bangladesh and is available through Mediaid Pharmacy for international procurement by oncology centres, hospital pharmacies, and patients in regions where Pemazyre® may be unavailable or cost-prohibitive. For the full range of bile duct cancer and biliary tract oncology medicines at Mediaid Pharmacy, visit the bile duct cancer medicines collection.
How is Pemitinib 13.5 MG (Pemigatinib) administered?
For cholangiocarcinoma, Pemitinib is administered orally at 13.5 mg once daily one film-coated tablet per day for 14 consecutive days, followed by a 7-day treatment break, in repeating 21-day cycles. For FGFR1-rearranged MLNs, Pemitinib is administered continuously at 13.5 mg once daily without a treatment holiday. Take Pemitinib tablets with or without food at the same time each day to maintain consistent plasma pemigatinib concentrations. Swallow the tablet whole do not crush, split, or chew. If a dose is missed, take it as soon as possible on the same day; if the missed dose is not recalled until the following day, skip the missed dose and resume the normal schedule. Do not take two doses on the same day. Start ophthalmological monitoring and serum phosphate assessment before the first dose of Pemitinib and maintain them at regular intervals throughout all treatment cycles. All dose adjustments, including reductions for RPED, hyperphosphatemia, or CYP3A4 drug interactions, must be directed by the treating oncologist or haematologist.
What are the side effects of Pemitinib 13.5 MG (Pemigatinib)?
The two most clinically significant adverse effects of pemigatinib (Pemitinib) are retinal pigment epithelial detachment (RPED) and hyperphosphatemia. RPED occurred in 11% of patients receiving pemigatinib 13.5 mg, with Grade 3/4 events in 1.3% and a median onset of 56 days from treatment start, requiring mandatory baseline and periodic ophthalmological monitoring with prompt dose interruption and referral to a retinal specialist at confirmed Grade ≥2 RPED. Hyperphosphatemia occurred as a laboratory finding in 94% of patients (clinical incidence 60%) due to the FGFR-mediated suppression of renal phosphate excretion, managed through dietary phosphate restriction and oral phosphate-lowering agents. Additional common adverse reactions in FIGHT-202 include: alopecia (49%), diarrhoea (47%), nail toxicity (43%), fatigue (42%), nausea (40%), dysgeusia (40%), constipation (35%), stomatitis (35%), dry mouth (34%), dry eye, decreased appetite, arthralgia, vomiting, abdominal pain, and hypophosphatemia. Alopecia and nail toxicity are among the most common dose-modification drivers for quality-of-life reasons; both are class-related FGFR inhibitor toxicities. Establish baseline ophthalmological and metabolic laboratory assessments and maintain structured monitoring throughout every Pemitinib treatment cycle.
How effective is Pemigatinib (Pemitinib) for FGFR2-rearranged cholangiocarcinoma and FGFR1-rearranged myeloid/lymphoid neoplasms?
Pemigatinib has demonstrated clinically meaningful, biomarker-selected efficacy in two Phase 2 studies supporting its two FDA-approved indications. In FGFR2 fusion or rearrangement-positive cholangiocarcinoma, the Phase 2 FIGHT-202 study (N=107 patients in the FGFR2 fusion/rearrangement cohort) achieved an ORR of 35.5% (38/107) by independent review comprising 3 complete responses and 35 partial responses with a disease control rate of 82%, median duration of response of 9.1 months, median PFS of 6.9 months, and an updated median overall survival of 17.5 months in a second-line setting where no approved targeted therapy previously existed and salvage chemotherapy achieves ORRs of 5–8%. In FGFR1-rearranged MLNs, the Phase 2 FIGHT-203 study (N=28) demonstrated a complete response rate of 78% (95% CI: 52%–94%) in chronic-phase marrow disease and a complete cytogenetic response rate of 79% (95% CI: 59%–92%) in the overall population, with a median duration of complete response that was not reached at analysis marking the first demonstration of deep, durable molecular remissions with a targeted agent in this rare haematological malignancy. These results supported FDA accelerated approval on April 17, 2020 and August 26, 2022 respectively. Pemitinib delivers the same active ingredient pemigatinib INN in 13.5 mg film-coated tablets, sourced through Mediaid Pharmacy with worldwide shipping. Visit the oncology medicines collection for the full targeted therapy range.
Is Pemitinib 13.5 MG (Pemigatinib) safe during pregnancy or while breastfeeding?
Based on pemigatinib’s mechanism of action selective inhibition of FGFR1, FGFR2, and FGFR3 signalling pathways that are critical for normal embryonic organogenesis and foetal limb and organ development pemigatinib is expected to cause embryo-foetal harm when administered during pregnancy. Adequate and well-controlled human pregnancy studies are not available. Pemitinib should not be used during pregnancy. Females of reproductive potential must use effective contraception during Pemitinib therapy and for at least 1 week after the last dose; hormonal contraceptives may be less effective due to pemigatinib’s CYP3A4-related effects, and barrier or non-hormonal IUD methods should be used. Male patients with female partners of reproductive potential should use effective contraception during treatment and for at least 1 week after the final dose. Verify pregnancy status before initiating Pemitinib in all females of reproductive potential. Whether pemigatinib is excreted into human breast milk is not known; breastfeeding is not recommended during Pemitinib treatment or for at least 1 week after the last dose. Discuss reproductive intentions, contraceptive planning, and breastfeeding with the treating oncologist before initiating and throughout Pemitinib therapy.
Can I order Pemitinib 13.5 MG (Pemigatinib) online with worldwide shipping?
Yes. Mediaid Pharmacy supplies Pemitinib 13.5 MG (Pemigatinib) 14 film-coated tablets per pot to patients, hepatobiliary oncology departments, biliary tract cancer and cholangiocarcinoma specialist centres, haematology units managing FGFR1-rearranged MLNs, hospital pharmacies, and healthcare providers globally. Contact Mediaid Pharmacy via WhatsApp, phone, or WeChat at +8801773428128, or email info@mediaidpharmacy.com for pricing, current stock availability, and international delivery details for your country.
Order Pemitinib 13.5 MG (Pemigatinib) with Worldwide Shipping
Phone / WhatsApp / WeChat: +8801773428128 | Email: info@mediaidpharmacy.com




Reviews
There are no reviews yet.